Cephalic phase of digestion and why IBS can start before you eat
Digestion begins in the brain, before food reaches the stomach. If sight, smell and expectation never register, the stomach starts the meal underprepared, and IBS symptoms can begin earlier than the plate itself.
What happens when you eat fast in front of a screen?
This pattern is more common than people realize. The meal starts with a laptop open, one eye on a notification, a few fast bites and almost no look at the food. There is little smell, little anticipation and almost no pause for the digestive system to register that food is about to arrive.
In that moment, digestion becomes mechanical. Food enters the mouth while the nervous system is still shifting toward a parasympathetic, meal-ready mode. You may still chew, swallow and finish the plate, yet the body begins the meal underprepared. For a person with IBS, that missing setup can shape the whole experience after the meal.
You can eat a well-balanced meal while your nervous system is still inside the screen.
In that setting, symptoms often begin with the way the meal starts and then travel with the food itself. This is why, in the clinics where I work as a scientific collaborator, the opening minutes of a meal get close attention. Many people assume the problem starts only after food reaches the intestine. The daily scene often tells a different story, because the reflexes that prepare gastric function may already be weak before the first bite.
Distraction also changes how much people eat. A 2026 meta-analysis of 50 studies found that eating while distracted increased the amount eaten at the next meal, and that passive distractions such as watching TV also increased intake during the meal itself.6
What happens in the cephalic phase of digestion?
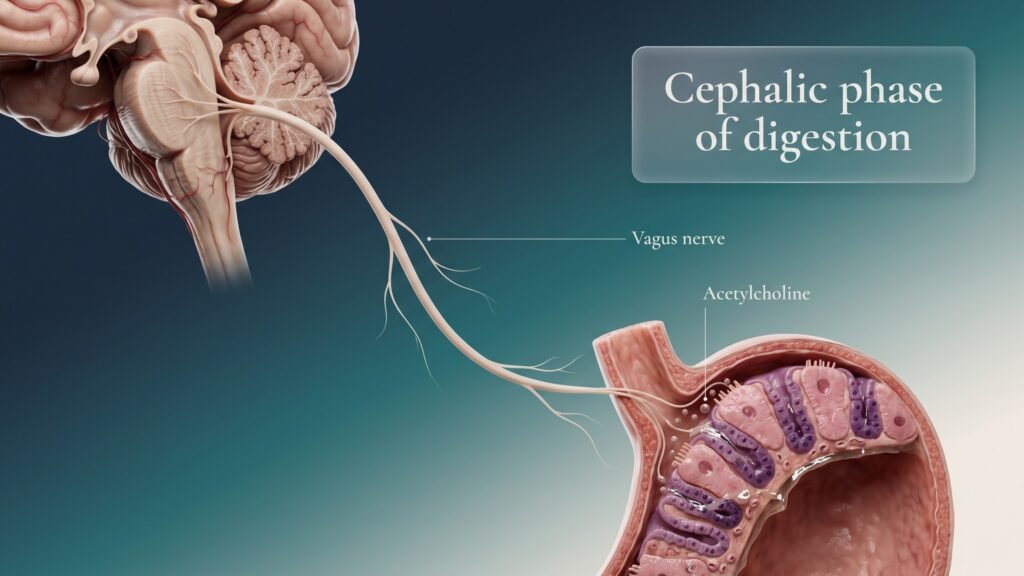
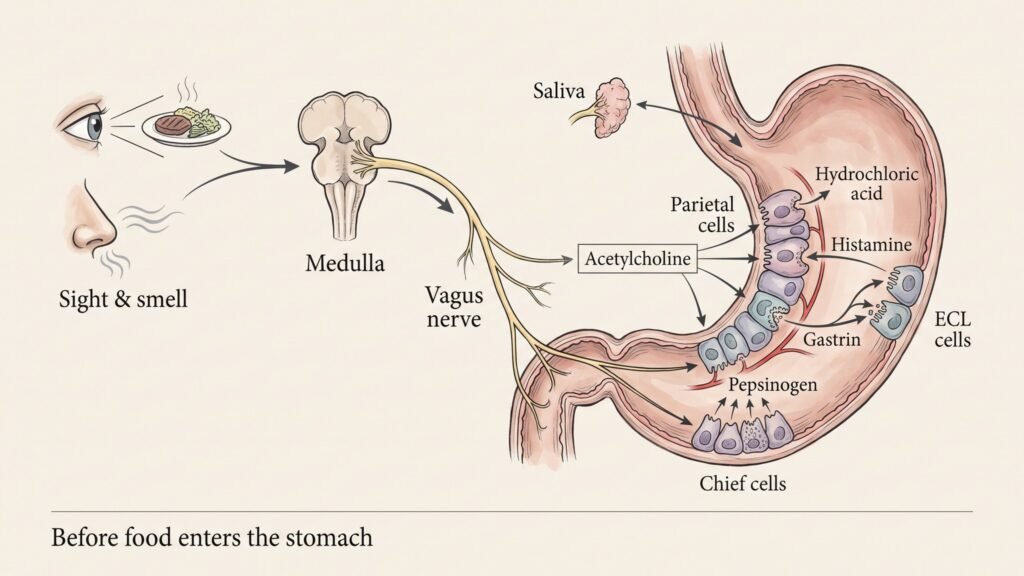
The cephalic phase of digestion begins when the brain detects food through sight, smell, taste, memory or expectation, before food enters the stomach. In practical terms, the nervous system starts preparing the stomach for work before the meal arrives.1, 7
- Cephalic phase
- The first phase of digestion, driven by the brain. Sensory and mental cues about food trigger nerve and hormone signals that prepare the mouth, stomach, pancreas and intestine before food arrives. The gastric and intestinal phases follow.
That preparation is largely vagal and parasympathetic. The medulla and the vagus nerve activate a reflex that increases saliva, stimulates gastric secretion and primes gastric motility. Acetylcholine reaches gastric tissues directly. G cells release gastrin. Histamine then helps stimulate parietal cells, while chief cells prepare pepsinogen and the stomach moves toward digestive readiness.2
How strong is the cephalic response?
The effect is large. In healthy people, modified sham feeding (chewing and tasting food without swallowing it) raised acid output to about 62% of the maximum the stomach can produce. After a truncal vagotomy, which cuts the vagus nerve, this acid response disappeared completely.8 Overall, cephalic signals are estimated to contribute more than half of the motor and secretory response after a meal.2
Thought matters most. In a classic study, discussing appetizing food raised acid secretion to about two thirds of the sham feeding response, while discussing current events or sports did not raise it at all. Sight and smell alone, without taste, reached 23% to 46% of the sham feeding response.3
By the time food enters the stomach, saliva, hydrochloric acid, pepsinogen and gastric motility should already be on the rise. The cephalic response is the body saying that the meal is here and it should get ready.
What happens when the cephalic phase is skipped?
When the cephalic response is weak, gastric preparation starts late and with less coordination. Food reaches the stomach while acid secretion, gastric juice and early motility rise less well. In effect, this may resemble hypochlorhydria (low stomach acid), even in a person who has never taken an acid-suppressing drug. This idea follows from the physiology above, but it has not been measured directly in people who eat while distracted.
The stomach works as a secretory and defensive organ. Its acid helps unfold proteins, activate pepsinogen, limit microbial survival and organize the next phase of digestion. When the first signal is blunted, people often feel the downstream effects as heaviness, belching, bloating, slow digestion or a meal that seems to sit there. The reason the stomach needs its acid in the first place is explained in why stomach acid matters more than an alkaline diet.
- The habit
The meal begins with distraction, speed and little sensory contact.
- A weak reflex
The vagus nerve receives a weaker anticipatory signal, so the cephalic response stays shallow.
- Lower secretory readiness
Saliva, gastrin, histamine-linked signaling and gastric secretion rise less well.
- Functional hypochlorhydria
The stomach behaves as if acid defense has been turned down, even without medication.
- The symptom pattern
Bloating, belching, pressure and bowel changes appear after meals that seemed harmless on paper.
A proposed sequence built from the physiology of the cephalic phase, not a proven chain in every person.
Why does the cephalic phase matter in IBS?
IBS is rarely only a colon story. The same autonomic tone that shapes sensation also shapes gastric function, small bowel motility and the quality of the meal response. If the early digestive response is weak, the person reaches the gastric phase with less readiness, then reaches the intestine with weaker digestion upstream. That is one way symptoms can begin before the colon enters the picture.
The bowel itself also has a cephalic phase. A 2026 review of the gastrocolonic response, the rise in colonic activity that starts within minutes of eating, describes cephalic, gastric and intestinal phases, with nerves as the main mediators in all three. The response was abnormal or weaker in chronic constipation and diabetes.11 How a meal triggers the bowel so quickly is covered in why bloating after eating can start within minutes.
This is also where the overlap with SIBO becomes more interesting. A weaker gastric barrier may leave more microbes alive as food enters the stomach, while impaired vagal tone and altered motility may make the small intestine a friendlier place for bacteria to persist. The same gut-brain logic appears in oregano oil for SIBO, in how to test for SIBO and in the histamine link between migraine and IBS.
What does George's case show about low stomach acid?
George's case is useful because it shows the same downstream pattern from a different starting point. In his story, chronic PPI use was the main pressure. Once the gastric barrier has been weakened for years, people can move toward bloating, indigestion and IBS-like instability through a chain that starts much earlier than the colon.
That is why the cephalic phase can be described as the body's internal primer. If it is repeatedly absent, people may drift toward a physiology that resembles the end result of acid suppression, even if they have never taken a drug. George's case makes the comparison tangible and shows why looking for the root cause matters more than chasing one symptom at a time. The full story is in George's omeprazole case.
George and the familiar IBS pattern
A summary of the case study, in four steps.
- The person
Long-standing upper gut discomfort, bloating and a symptom pattern that kept returning to the same bottleneck.
- The history
Chronic PPI use weakened acid defense and set the stage for a broader digestive problem.
- The findings
Low stomach acid, altered upper gut ecology and a picture downstream that looked very much like IBS.
- The outcome
Once the sequence was understood and treated as a connected system, the case moved toward recovery and lasting symptom control.
In the practice records shown with George's case study, more than 70% of people with this pattern improved. These are records of the practice, not data from a published trial.
If this pattern sounds close to your own story, especially if meals trigger bloating before the food itself seems suspicious, that is a good reason to look at the sequence directly. Long-term PPI use can also lower vitamin B12, as explained in how long-term PPI use can lead to vitamin B12 deficiency.
How can you reactivate the cephalic phase?
A simple routine may improve the first minutes of digestion. The goal is to create a stronger opening signal, stimulate the cephalic response, increase vagal readiness and let gastric secretion start on time.

Look and smell before the first bite
Visual and smell cues help activate the medulla and vagus nerve reflex before food enters the stomach. Spend 20 to 30 seconds looking at the meal and breathing in its smell before you start.
Slow down the first three bites
Slow chewing extends stimulation in the mouth, supports saliva and sustains the early reflex that feeds gastric secretion. Make the first three bites slow on purpose, and chew until the texture is fully broken down before swallowing.

Start without a screen
Less competing mental load helps the parasympathetic nervous system lead at the start of the meal. Begin the meal without a phone or laptop in front of you, even if the rest of the meal later becomes less controlled.
The same habits connect with other eating patterns that affect the gut, covered in eating behaviors that ruin your gut microbiome.
Frequently asked questions
It is the first digestive response to a meal. The brain detects food through sight, smell, taste or expectation and activates vagal and hormonal signals before food enters the stomach.1
It is brief and overlaps with the opening moments of a meal. It covers the anticipation and the first moments before and around swallowing, then hands the sequence over to the gastric and intestinal phases.
The nervous system starts the process through the medulla, the vagus nerve and acetylcholine. Gastrin and histamine-linked signaling then amplify gastric secretion and prepare parietal and chief cells for the meal.2
Thinking about food, along with its sight, smell and taste, sends signals through the vagus nerve. In healthy people, discussing appetizing food was as strong a trigger as two thirds of sham feeding.3
The cephalic phase starts in the brain before eating, the gastric phase begins when food stretches the stomach, and the intestinal phase begins when food reaches the small intestine.11
References
15 studies
- Power ML, Schulkin J. Anticipatory physiological regulation in feeding biology: cephalic phase responses. Appetite. 2008.
- Katschinski M. Nutritional implications of cephalic phase gastrointestinal responses. Appetite. 2000.
- Feldman M, Richardson CT. Role of thought, sight, smell, and taste of food in the cephalic phase of gastric acid secretion in humans. Gastroenterology. 1986.
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG clinical guideline: small intestinal bacterial overgrowth. Am J Gastroenterol. 2020.
- Lo WK, Chan WW. Proton pump inhibitor use and the risk of small intestinal bacterial overgrowth: a meta-analysis. Clin Gastroenterol Hepatol. 2013.
- Gough T, Mann T, Ahmadyar K, et al. Eating while distracted: a systematic review and meta-analysis of the effect of distraction on concurrent and later energy intake in adults. Am J Clin Nutr. 2026.
- Smeets PA, Erkner A, de Graaf C. Cephalic phase responses and appetite. Nutr Rev. 2010.
- Konturek SJ, Kwiecien N, Obtulowicz W, et al. Cephalic phase of gastric secretion in healthy subjects and duodenal ulcer patients: role of vagal innervation. Gut. 1979.
- Khurmatullina AR, Andreev DN, Kucheryavyy YA, et al. The duration of proton pump inhibitor therapy and the risk of small intestinal bacterial overgrowth: a systematic review and meta-analysis. J Clin Med. 2025.
- Kashyap P, Moayyedi P, Quigley EMM, et al. Critical appraisal of the SIBO hypothesis and breath testing: a clinical practice update endorsed by ESNM and ANMS. Neurogastroenterol Motil. 2024.
- Shibata C, Tsujinaka S, Miura T, et al. Role of neural and humoral mediators in the gastrocolonic response. J Smooth Muscle Res. 2026.
- Salvioli B, Pellegatta G, Malacarne M, et al. Autonomic nervous system dysregulation in irritable bowel syndrome. Neurogastroenterol Motil. 2015.
- Sadowski A, Dunlap C, Lacombe A, Hanes D. Alterations in heart rate variability associated with irritable bowel syndrome or inflammatory bowel disease: a systematic review and meta-analysis. Clin Transl Gastroenterol. 2020.
- Pittayanon R, Lau JT, Yuan Y, et al. Gut microbiota in patients with irritable bowel syndrome, a systematic review. Gastroenterology. 2019.
- Rajilić-Stojanović M, Biagi E, Heilig HG, et al. Global and deep molecular analysis of microbiota signatures in fecal samples from patients with irritable bowel syndrome. Gastroenterology. 2011.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, July 30). Cephalic phase of digestion and why IBS can start before you eat. Gut Pathways. https://gutpathways.com/articles/cephalic-phase-of-digestion/