Does oregano oil work for SIBO?
Oregano oil for SIBO is popular because it is antimicrobial. The more useful question is where it belongs in a treatment plan that also deals with motility, stomach acid and the risk of relapse.

Does oregano oil work for SIBO?
Oregano oil for SIBO can be useful as one antimicrobial part of a broader plan. Its main compounds, carvacrol and thymol, damage microbial membranes in laboratory models.1 In a small human study, multi-ingredient herbal therapies did at least as well as rifaximin in people with a positive breath test.2
One detail, however, shapes the whole conclusion. The products contained several ingredients, so the result belongs to the combination, with oil of oregano as one component.
That distinction matters in practice. A targeted agent may lower the microbial load and ease bloating, gas or abdominal discomfort. Meanwhile, the wider system still needs attention: the migrating motor complex, stomach acid, bile flow, gut anatomy and the gut community pushed aside by repeated antibiotic courses.
Pressure
Low stomach acid, weak motility, altered anatomy or a medication lets microbes build up in the small bowel.

Reduction
A herbal antimicrobial may reduce susceptible organisms during a supervised treatment phase.
Recovery
Motility, nutrition, acid defense and a resilient microbial community then need to recover.
Among 104 patients with a follow-up breath test, the test normalized in 17 of 37 people on one of two multi-herb regimens (46%) and in 23 of 67 on rifaximin (34%). The difference was not statistically significant, and the study was retrospective, not a trial of oregano oil alone.2
What is SIBO, what causes it and how do PPIs contribute?
Small intestinal bacterial overgrowth is an abnormal increase or disruption of microbes in the small intestine, where microbial density is normally far lower than in the colon. Current studies often use more than 10³ colony-forming units per milliliter in a duodenal aspirate as the cut-off, although definitions and sampling still vary.5, 6
Once excess microbes ferment carbohydrates too early, SIBO symptoms such as bloating, abdominal distension, pain, diarrhea or constipation can appear.
A classic pathogen is not required, either. Friendly gut bacteria in the wrong place or at the wrong concentration can also be involved. Lactobacillus, Streptococcus and Enterococcus may belong to a healthy oral or intestinal ecosystem, yet add to overgrowth when clearance through the small bowel fails.
Location, load and community behavior therefore matter as much as a microbe's reputation. This is why identifying the bacteria behind SIBO takes more than labeling every species good or bad.
The drivers of overgrowth
The small intestine protects itself through stomach acid, bile, pancreatic secretions, the ileocecal valve and fasting waves called the migrating motor complex. Overgrowth develops when one or more of these defenses weakens. Managing SIBO therefore starts with finding the driver, before any natural-remedy plan is assembled.
The PPI link also clarifies the role of a herbal antimicrobial. It is one possible step inside a wider effort to restore the defense that failed.
| Condition, operation or medicine | How it can promote overgrowth |
|---|---|
| Autoimmune thyroiditis with hypothyroidism | Low thyroid function can slow intestinal transit and weaken clearance between meals. The risk relates to hypothyroidism and dysmotility more than to the antibody label itself. More in hypothyroidism and SIBO. |
| Diabetes and autonomic neuropathy | Neuropathy can impair gastric emptying and small-intestinal motility, so microbes stay and multiply. |
| Systemic sclerosis | Smooth-muscle and nerve dysfunction can cause severe intestinal stasis, a well-established setting for overgrowth. |
| Cholecystectomy | Continuous bile delivery, no longer tied to meals, may change how bile limits microbes. Observational studies report an association, and most people never develop overgrowth after surgery. See SIBO after gallbladder removal. |
| Gastric or intestinal surgery | Blind loops, bypassed segments, adhesions, fistulae and loss of the ileocecal valve can create stagnant areas or let colonic microbes move upward. |
| Celiac disease and Crohn's disease | Mucosal injury, inflammation, strictures and altered motility can overlap with overgrowth and blur the symptoms. |
| Chronic pancreatitis or exocrine pancreatic insufficiency | Fewer digestive enzymes change nutrient availability and local defenses in the small bowel. |
| Cirrhosis | Altered bile acids, motility and immune defense raise the chance of bacterial translocation and overgrowth. |
| Gastroparesis, pseudo-obstruction and small-bowel diverticula | Each can cause stasis, which leaves more time for fermentation and microbial growth. |
| Proton pump inhibitors | Long-term acid suppression weakens the gastric barrier. Meta-analysis data link PPI use with more SIBO, although confounding and different test methods limit certainty about cause.3 |
| Opioids and anticholinergic medicines | Both can slow intestinal transit, so a medication review belongs in a credible plan. |
The PPI to SIBO pathway
Proton pump inhibitors reduce stomach acid. That can be appropriate and sometimes necessary. However, long-term suppression also lets more oral and food-borne bacteria survive the stomach. Low acid can then sit beside an altered upper-gut flora, weaker digestion and vitamin B12 deficiency.
The final picture may look like IBS, especially when bloating, bowel changes and indigestion are treated as separate diagnoses.
Across 29 studies, SIBO was found in about 37% of PPI users against 20% of controls (odds ratio 2.14), and each extra month of PPI use was linked with a higher prevalence. Study heterogeneity was high and test methods differed, so this is an association rather than proof that every PPI causes overgrowth.3
How does oregano oil work against SIBO bacteria?
Oregano oil works mainly by damaging microbial membranes and disturbing ion balance, energy production and cell integrity. Carvacrol and thymol are fat-soluble phenols that enter the membrane, make it leaky and let cell contents escape.1
These effects explain why oregano oil inhibits both Gram-positive and Gram-negative bacteria in the lab. The open clinical questions are different, though: which dose reaches the human small intestine, which microbes are exposed and how a complex overgrowth community responds.
| Bacterium | Median MIC (mg/mL) | Range across preparations |
|---|---|---|
| Staphylococcus aureus | 0.5 | 0.25 to 4 |
| Methicillin-resistant S. aureus | 0.75 | 0.25 to 1 |
| Methicillin-resistant S. epidermidis | 0.75 | 0.25 to 2 |
| Enterococcus faecalis | 1 | 0.5 to 4 |
| Enterococcus faecium | 0.5 | 0.25 to 8 |
| Streptococcus agalactiae | 0.25 | 0.25 to 0.5 |
| Escherichia coli | 1 | 0.5 to 8 |
| Salmonella Typhimurium | 1 | 0.25 to 8 |
Four oregano essential oil preparations inhibited eight Gram-positive and Gram-negative bacteria, but potency varied a lot with chemical composition and organism. The work supports a broad laboratory mechanism, not a clinical dose.1
What does the human evidence for oregano oil in SIBO show?
Human evidence for oregano oil in SIBO is promising and still indirect. The study cited most often compared rifaximin with two commercial herbal therapies that contained oregano alongside berberine-containing plants and other compounds. Oregano was therefore part of a combination.2
Breath test normalization was numerically higher with herbal therapy. Still, the difference stayed within chance, and treatment followed clinical practice without randomization.2
The fair description, then, is a herbal antimicrobial with laboratory activity and a place in some clinician-guided protocols. Calling it proven, or equal to an antibiotic, would need more than one retrospective, multi-ingredient comparison.
Neem, berberine, allicin and oregano oil may all appear in herbal therapies. Methane-dominant, hydrogen-dominant and hydrogen-sulfide patterns each call for their own strategy.
What supports oregano oil
What remains unproven
- No high-quality randomized trial shows that oregano oil alone treats SIBO.
- There is no standard formulation, active-compound content, dose or duration.
- A normal follow-up breath test does not show that normal physiology and gut health have recovered.
Why does oregano oil often fall short on its own?
Relying on oregano oil alone often fails because overgrowth usually reflects a broken control system. If slow transit, a damaged migrating motor complex, low stomach acid, altered anatomy or an untreated disease remains, the same pressure returns once treatment stops. No antimicrobial can repair a blind loop or restart fasting motility.
It can also affect beneficial gut bacteria. So the answer to a common question is yes: oregano oil may suppress some friendly organisms as well as unwanted ones.
When the gut's balance returns, those communities may recover, because the new conditions favor them. That recovery is possible, but it depends on diet, motility, medication exposure and the starting microbiome. For this reason, probiotic and prebiotic choices belong to an individual plan, guided by tolerance and clinical context.
If oregano oil reduces SIBO symptoms, the condition is cured.
Symptom relief can reflect less fermentation without showing that motility, nutrient status or the underlying disease has recovered. A lasting result needs a plan for both the microbial load and the reason it built up.
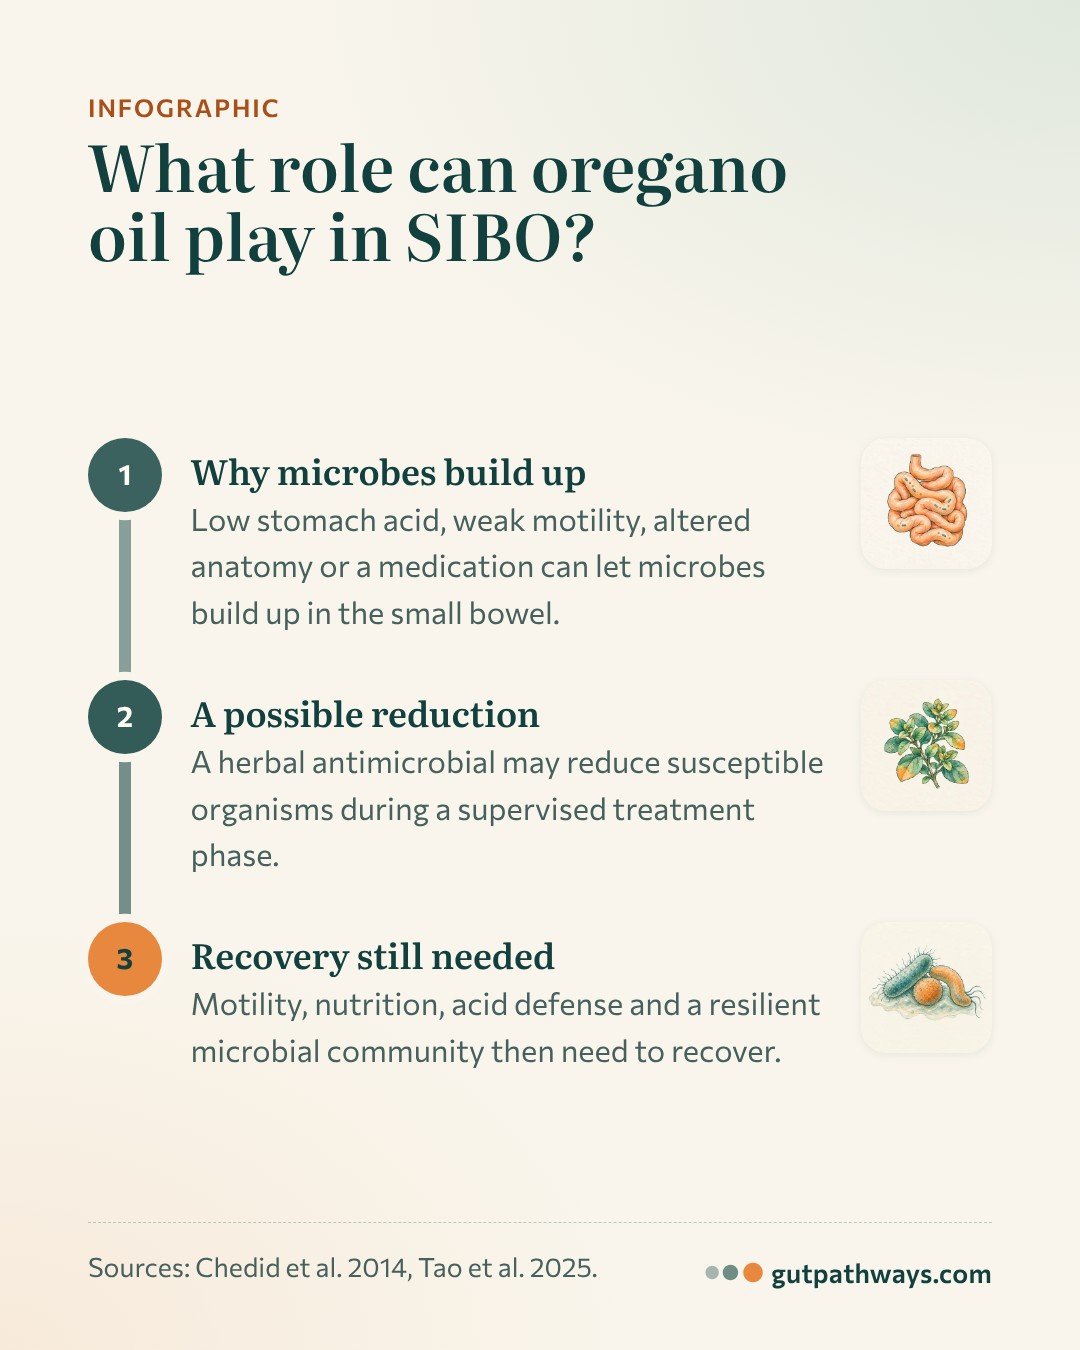
Infographic
Why microbes build up
Low stomach acid, weak motility, altered anatomy or a medication can let microbes build up in the small bowel.
A possible reduction
A herbal antimicrobial may reduce susceptible organisms during a supervised treatment phase.
Recovery still needed
Motility, nutrition, acid defense and a resilient microbial community then need to recover.
Sources: Chedid et al. 2014, Tao et al. 2025.
gutpathways.com
 Save this infographicImage 4:5, with sources, from gutpathways.com
How do you diagnose SIBO and confirm treatment worked?
Before starting any herbal antimicrobial, the diagnosis deserves a real look. SIBO is usually investigated with a glucose or lactulose breath test that measures hydrogen and methane for up to three hours. It is convenient and non-invasive, but it is an indirect fermentation test that tracks gas, not a bacterial count.
As a result, a negative test still leaves overgrowth possible, and a positive test says nothing about which organisms are involved. The result has to be read beside symptoms, risk factors, preparation quality and the clinical response.
Breath test accuracy against jejunal aspirate culture (%)
Losurdo 2020, meta-analysis of 14 studies. Some subgroups rest on few studies.
Across 14 studies, pooled sensitivity and specificity were 42.0% and 70.6% for lactulose, and 54.5% and 83.2% for glucose. Accuracy changed with the cut-off and with patient selection, and the glucose test worked best after gastrointestinal surgery.4
Every important limitation of the SIBO breath test
Breath testing measures exhaled gases produced after a sugar substrate. It gives no bacterial count, no species, no susceptibility testing and no view of the gut lining.
Methane comes from archaea and can arise in the small or large intestine, so the preferred term is intestinal methanogen overgrowth (IMO), separate from classic SIBO.
Many commercial tests measure only hydrogen and methane, so a two-gas test can miss hydrogen sulfide, an important metabolic pattern.
Some microbial communities make little hydrogen. Others use hydrogen to make methane or hydrogen sulfide, which flattens the hydrogen curve.
Lactulose reaches the colon. Fast transit from mouth to colon can create an early hydrogen rise that looks like overgrowth.
Glucose is absorbed in the upper small intestine, so it may never reach overgrowth further down.
High baseline values and persistently flat profiles are difficult to interpret and may reflect preparation, oral fermentation or communities that make little gas.
Accuracy changes with the population. Tests may perform better after gastrointestinal surgery than in people with no obvious predisposing condition.4
Duodenal or jejunal aspiration has its own limits: oral contamination, one sampling site, non-standard culture cut-offs and organisms that routine culture misses.
Substrate choice, substrate dose, gas cut-offs, sampling intervals and total test time vary between laboratories and guidelines.
Antibiotics, probiotics, laxatives, prokinetics, the preparation diet, fasting, smoking, exercise and recent sleep can all change results.
The same person can produce a different curve on another day.
Poor breath collection, delayed analysis, leaking bags and differences between devices add error before and during analysis.
When a negative test meets persistent symptoms
A negative breath test still leaves questions open. In the clinics where I work as a scientific collaborator, PCR or 16S analysis of a carefully collected duodenal aspirate often finds a high microbial signal or a disrupted community in people with IBS and related disorders despite a negative gas result.
This observation is biologically plausible, yet it needs careful reading. Molecular tests detect microbial DNA, including organisms that routine culture misses. The strongest reading pairs the DNA signal with culture data, symptoms and validated cut-offs.
Duodenal aspirates from 140 people showed higher bacterial counts and a distinct 16S profile in culture-defined SIBO, with more Proteobacteria. In the 20 people who also had a lactulose breath test, only 4 of 7 with SIBO tested positive at 90 minutes, against 2 of 13 without SIBO.6
Testing after treatment earns its place when it answers a clinical question. A repeat breath test can help when the first result was clearly positive and the answer would change management. Duodenal aspiration with culture and molecular analysis can add detail in selected complex cases.
By contrast, stool 16S rRNA testing describes the colon, a different neighborhood from the small intestine. Fecal elastase, vitamin B12, folate, zinc and vitamin D can reveal consequences or competing diagnoses. Clearance itself, however, needs a small-intestinal answer.
A 2024 update endorsed by the European and American motility societies concluded that breath tests are not reliable enough to carry a diagnosis on their own. Unvalidated breath testing has also led to widespread antibiotic use, so a result is best read together with symptoms and history.7
When long-term PPI use led to SIBO: a clinical case
This case follows a person whose long-term PPI use was followed by persistent bloating, indigestion and bowel changes. The main clue was the sequence itself. Long-term acid suppression weakened the first acid barrier, the upper gut ecosystem changed, and the resulting overgrowth was treated again and again as separate symptoms.
The pattern behind PPI-related SIBO
One connected chain, read from the first cause to the last symptom.
- The pattern
Long-term acid suppression came with bloating, indigestion and IBS-like bowel changes that persisted as apparently separate complaints.
- The overlooked trigger
The medication history showed sustained PPI use and the consequences of a weakened gastric acid barrier.
- The connected findings
The case linked bacterial overgrowth with dysbiosis, weaker digestion and nutrient gaps in one connected picture.
- The result
In the wider series of more than 98 similar cases from the practice, described in IBSyncrasy, people were 30 to 55 years old. Overall success was above 70%, and recovery usually took two to six months.
These are observational results from the practice archive behind the book. They describe what happened in that group, and individual responses always vary.
Symptoms in the practice series, before and after care (%)
Observational case series from the practice archive behind IBSyncrasy, more than 98 cases.
What keeps SIBO from returning after treatment?
The best relapse plan treats the reason overgrowth developed, protects fasting motility and avoids repeated antimicrobial courses without a new assessment. That can mean reviewing the need and dose of a PPI with the prescribing doctor, treating hypothyroidism or diabetes, addressing constipation, testing pancreatic function, managing adhesions or supporting nutrition.
In other words, SIBO is managed as a system, with the gut ecology kept intact.
In this case, the maintenance routine included finishing food by 7 pm, a 16:8 eating window and avoiding large amounts of water with meals. These were individual choices meant to protect fasting gaps and digestive concentration, matched to this person's profile. A long fasting window needs medical judgment, especially in pregnancy, low body weight, frailty, risk of low blood sugar or a history of eating disorder.
Oregano oil for SIBO may help reduce microbial pressure inside a plan that also includes diagnosis, root-cause work and follow-up. The goal is the right microbial load in the right place, supported by the physiology that keeps it there. For the wider picture, see how to treat gut dysbiosis in the right order.
Frequently asked questions
No single herb reliably clears every form of SIBO. Oregano oil, berberine-containing herbs, neem and allicin appear in herbal protocols, but the evidence is limited and products often combine several ingredients.2 Methane, hydrogen and hydrogen sulfide patterns also involve different microbial ecosystems, which is why methane-dominant overgrowth is often handled differently. The safer question is which treatment fits the test pattern, symptoms, underlying driver and medical history.
In the best-known study, the herbal protocols ran for 4 weeks, followed by a repeat breath test.2 There is no standard duration for oregano oil on its own, and longer courses are not proven to work better. A clinician usually sets a defined, short phase and then reassesses.
There is no standard, evidence-based dose of oregano oil for SIBO. Products vary widely in carvacrol content, formulation and release, so copying a drop count from someone else is unsafe. A clinician may use oregano for a short active phase and decide whether a probiotic belongs during or after it. If both are used, separating their timing is sensible, and the best schedule remains an individual decision.
The human data for herbs in SIBO come from combination products. In the main study, the herbal regimens paired oregano with berberine-containing plants and other compounds, and normalized breath tests about as often as rifaximin.2 Herbal products can interact with medicines, so a combination is best set up with your doctor or pharmacist.
Yes, oregano oil can suppress some friendly gut bacteria as well as unwanted ones, because its antimicrobial effect is not very selective.1 When the gut's balance returns, beneficial communities may recover because motility, diet and the chemical environment favor them again. Recovery is not guaranteed, which is why long or repeated use without a clear plan can work against gut health.
People online describe more bloating, gas, fatigue or bowel changes in the first days of a herbal protocol and call it die-off. Research has not defined this reaction for SIBO, and the same symptoms can mean the product irritates the gut or does not suit you. Worsening symptoms during any protocol are a reason to check in with the clinician who set it up.
People with a sensitive stomach, reflux or gastritis may burp it back up or get burning, nausea, diarrhea or abdominal discomfort. Avoid medicinal oregano oil during pregnancy, because safety data are lacking. Extra caution applies with an allergy to mint-family plants, a bleeding disorder, anticoagulant or antiplatelet medicines, upcoming surgery or glucose-lowering medicines. Concentrated essential oil should never be swallowed undiluted, and a chronic condition or regular medication is a reason to ask your doctor and pharmacist first.
Less bloating and gas, steadier bowel habits and more tolerance of foods that used to cause trouble are the signs people usually notice. A repeat breath test can add information when the first one was clearly positive, but its accuracy is limited.4 Lasting improvement depends on the driver, so stable symptoms after treatment stops matter more than a single test result.
Do not stop a prescribed PPI abruptly. Ask the prescriber to review the reason, the lowest effective dose and the alternatives, because some conditions need ongoing acid suppression. If SIBO symptoms return, constipation, motility, thyroid and glucose control, anatomy, pancreatic function, diet and test quality all deserve another look before oregano oil or an antibiotic is repeated.
References
7 studies
- Tao L, Liang Y, Xia Z, et al. Antibacterial activities of oregano essential oils and their active components. Front Pharmacol. 2025.
- Chedid V, Dhalla S, Clarke JO, et al. Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Glob Adv Health Med. 2014.
- Khurmatullina AR, Andreev DN, Kucheryavyy YA, et al. The duration of proton pump inhibitor therapy and the risk of small intestinal bacterial overgrowth: a systematic review and meta-analysis. J Clin Med. 2025.
- Losurdo G, Leandro G, Ierardi E, et al. Breath tests for the non-invasive diagnosis of small intestinal bacterial overgrowth: a systematic review with meta-analysis. J Neurogastroenterol Motil. 2020.
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. Am J Gastroenterol. 2020.
- Leite G, Morales W, Weitsman S, et al. The duodenal microbiome is altered in small intestinal bacterial overgrowth. PLoS One. 2020.
- Kashyap P, Moayyedi P, Quigley EMM, et al. Critical appraisal of the SIBO hypothesis and breath testing: a clinical practice update endorsed by ESNM and ANMS. Neurogastroenterol Motil. 2024.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, July 28). Does oregano oil work for SIBO?. Gut Pathways. https://gutpathways.com/articles/oregano-for-sibo/