Irritable bowel syndrome and anemia
IBS does not usually cause anemia outright, but it makes low iron more likely. Less food during flares, foods and medicines that block absorption, and iron tablets the gut does not tolerate all add up.

Are IBS and anemia related?
Yes. People with IBS tend to have lower baseline iron than people without IBS, and that raises the risk of iron deficiency anemia. A systematic review of 26 studies found lower vitamin B2, vitamin D, calcium and iron in people with IBS, and exclusion diets went together with lower intake of several micronutrients, iron among them.1
Even so, anemia itself is not a typical IBS feature. In practice, IBS works as a risk amplifier for low iron rather than a direct cause of anemia. If iron deficiency anemia does appear, it is a red flag that calls for a search for other causes, such as bleeding or malabsorption.7, 2
In 730 people with suspected IBS who had a colonoscopy at three centers, anemia raised the odds that an organic disease was found instead of IBS by about 2.8 times.2
IBS subtypes behave differently, and knowing your pattern reduces guesswork. If you are not sure where you fit, start with the IBS types before changing diet or supplements.
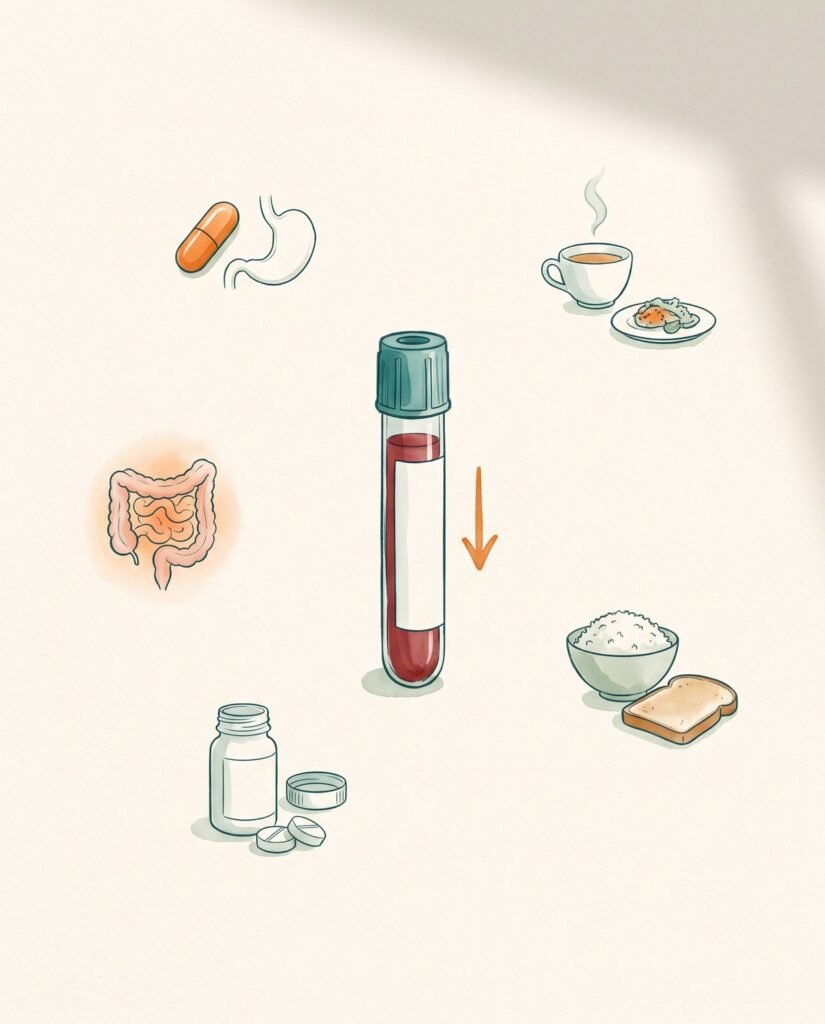
Tea or coffee with meals
Their polyphenols can cut the iron absorbed from a meal by 50% to 90%.3
A low-iron comfort diet
A strict low FODMAP phase, or cutting out legumes and meat, lowers iron intake.9
Calcium at the same meal
Calcium from milk, cheese or supplements lowers the absorption of both plant and meat iron.4
Inflammation of the small intestine
Inflammation where iron is absorbed, as in celiac disease or IBD, lowers uptake and needs its own work-up.7
Sources: McColl 2009, Lam 2017, Hurrell 1999, Eswaran 2020, Hallberg 1991, AGA 2024.
 Save this infographicImage 4:5, with sources, from gutpathways.com
Symptoms of anemia and when people with IBS need a work-up
Symptoms of anemia include easy fatigue, shortness of breath on exertion, palpitations, lightheadedness, craving ice and pale skin. Blood tests usually show low ferritin, and sometimes small red cells with low hemoglobin. Fatigue in IBS is easy to blame on the gut, which is one more reason to check ferritin rather than guess.
Can irritable bowel syndrome cause iron deficiency?
It does not cause it directly, but it makes iron deficiency more likely in several ways. Intake drops during flares, and tea, coffee, calcium and proton pump inhibitors can lower the absorption of plant iron. In addition, a strict low FODMAP phase can trim micronutrients if nobody supervises it.9
Guidance is clear that iron deficiency anemia should be investigated for gastrointestinal causes rather than put down to IBS alone.7 For the same reason, ferritin and iron studies come first, and stool tests or endoscopy may follow if there are alarm features such as rectal bleeding, black stool or weight loss.
IBS-related low iron and anemia from other causes
In other words, IBS acts as an amplifier. Food avoidance during flares lowers iron intake, while medicines and drinks block plant iron. Separately, other conditions can cause blood loss that drains iron stores. Telling these apart is what the work-up is for.
Why people with IBS may run low on iron
Four everyday factors explain most of the gap. Each one is fixable once you can see it.

Dietary restriction
A strict low FODMAP phase, or cutting back on legumes and red meat, lowers iron intake. In one trial, fewer people on a four-week low FODMAP diet met the recommended iron intake than before.9


Enhancers and timing
Pairing iron-rich food with vitamin C and keeping coffee, tea and calcium away from that meal improves uptake.7
Day-to-day choices matter. In a trial in people with IBS-D, four weeks of a low FODMAP diet lowered the intake of several micronutrients compared with a standard IBS diet. Most of those differences disappeared once calories were taken into account, but fewer people met the recommended iron intake.9 A restrictive phase is safe when it is guided and then widened again.
Iron absorption basics
Iron from plants, called non-heme iron, depends heavily on what else is in the meal. Vitamin C raises its uptake, while tea and coffee polyphenols, phytates and calcium lower it. In one study, polyphenol-rich drinks cut iron absorption from a bread meal by 50% to 90%, with black tea among the strongest.3
Calcium is a special case, because it lowers the absorption of both heme and non-heme iron. In a study of 126 people, 165 mg of calcium from milk, cheese or calcium chloride reduced iron absorption by 50% to 60%.4 In practice, that means pairing iron-rich food with vitamin C and keeping tea, coffee and calcium away from that meal.
Low FODMAP diet pitfalls
During the strict low FODMAP phase, people often drop legumes and some grains that carry plant iron. If meat is also limited because of symptoms, total iron intake can fall quickly. Low FODMAP iron sources and an early, planned reintroduction keep the diet from turning into a deficiency. The longer-term diet question is covered in post-infectious IBS diet.
PPIs, tea and calcium
Proton pump inhibitors lower stomach acid, and with it the absorption of non-heme iron. They may also slow the response to iron supplements.8 In a large case-control study, two or more years of PPI use went with about 2.5 times higher odds of iron deficiency, and the link weakened after stopping.5 For long-term PPI cases in IBS, see George's case.
When oral iron supplements trigger digestive problems in IBS
Oral iron commonly causes abdominal pain, bloating, dark stool and diarrhea or constipation. That answers a common question, does iron cause diarrhea, with a yes for some people. Beyond symptoms, unabsorbed iron that reaches the colon may shift the gut microbiome, as reviews of oral iron and the gut note.10
Oral iron and Enterobacteriaceae
In a 12-week randomized trial in women of reproductive age, most of whom were not iron deficient, ferrous bisglycinate increased the relative abundance of Enterobacteriaceae, a family that includes several gut pathogens.6 In people with IBS, who are already sensitive to microbial changes, a shift like this may mean more gas, urgency or loose stool.
Diarrhea, bloating and stool changes with iron tablets
Many people with IBS report that standard oral iron worsens diarrhea, bloating or pain. Taking the lowest effective dose, or taking it every other day, can improve tolerance, and guidance allows every-other-day dosing with similar absorption.7 Even so, symptoms can persist.
Timing after antibiotics matters too. In mice, iron supplementation after an antibiotic course pushed the recovering microbiota toward a different, less favorable composition.11 In practice, this pattern shows up often in post-infectious IBS or after recent antibiotics. More on that in IBS after antibiotics.
A gut-first approach to iron repletion in IBS
Because IBS is a microbiome-sensitive condition, the approach in the practice where I work as a scientific collaborator is gut-first. Oral iron is avoided whenever possible, medically supervised intravenous (IV) iron is preferred when repletion is needed, and liposomal oral iron is kept for rare cases where IV iron is not possible.
Mainstream guidance takes a broader view. The American Gastroenterological Association says that no oral formulation has a clear advantage, that oral iron should be taken at most once a day, and that IV iron should be used when oral iron is not tolerated, does not raise ferritin, or is unlikely to be absorbed.7 People with IBS who react badly to tablets often fall into the first group.
Why IV iron spares the gut
IV iron replaces stores quickly without leaving free iron in the gut, so it does not feed iron-loving bacteria or aggravate IBS symptoms through that route. It also avoids interactions with tea, coffee and calcium, and PPIs do not limit it. In practice, symptoms tend to stay steadier with supervised IV iron than with repeated oral trials.
How and when liposomal iron may be used
Liposomal iron is kept for rare situations where a short, closely monitored oral course cannot be avoided. Even then, it is taken away from tea, coffee and calcium, paired with vitamin C, and stopped if pain, diarrhea or bloating escalate. If intolerance appears, the next step is IV iron rather than forcing the gut to adapt.
Diet and daily habits that raise iron while managing IBS
Choose heme iron sources you tolerate, and pair plant iron with vitamin C. Widen a low FODMAP diet to include iron-containing foods as soon as symptoms allow. If SIBO or another condition is suspected, address it, because overlapping problems can lower iron or vitamin B12. The reason the exact bacteria matter is explained in how to test for SIBO.
Heme and non-heme iron and vitamin C pairing
Heme iron from meat is absorbed more efficiently and is less affected by blockers. Non-heme iron from legumes, fortified grains, nuts and leafy greens benefits from vitamin C in the same meal. A weekly rotation that fits your IBS subtype keeps intake steady without one big trigger meal.
Frequently asked questions
Common gastrointestinal causes include inflammatory bowel disease, celiac disease, peptic ulcer disease, colorectal cancer, angiodysplasia and other sources of hidden bleeding. Guidance recommends investigating iron deficiency anemia for gastrointestinal sources rather than putting it down to IBS alone.7
Yes, fatigue is common in IBS. Low iron is one of the causes worth ruling out, since it is easy to check with ferritin and easy to miss when every symptom is blamed on the gut.1
Oral iron can cause diarrhea in some people, and constipation, pain or bloating in others. Lower doses or every-other-day dosing can help tolerance, and IV iron is an option when tablets are not tolerated.7
No oral form has a proven advantage over the others.7 For people with IBS who react badly to tablets, a gut-first plan favors supervised IV iron, with liposomal iron kept for rare cases.
Anemia itself does not usually cause bloating. More often, the same gut problem drives both, or oral iron tablets cause the bloating. Bloating together with anemia is a reason for a proper work-up.
References
11 studies
- Bek S, Teo YN, Tan XH, Fan KHR, Siah KTH. Association between irritable bowel syndrome and micronutrients: a systematic review. J Gastroenterol Hepatol. 2022.
- Yang Q, Wei ZC, Liu N, et al. Predictive value of alarm symptoms in Rome IV irritable bowel syndrome: a multicenter cross-sectional study. World J Clin Cases. 2022.
- Hurrell RF, Reddy M, Cook JD. Inhibition of non-haem iron absorption in man by polyphenolic-containing beverages. Br J Nutr. 1999.
- Hallberg L, Brune M, Erlandsson M, Sandberg AS, Rossander-Hultén L. Calcium: effect of different amounts on nonheme- and heme-iron absorption in humans. Am J Clin Nutr. 1991.
- Lam JR, Schneider JL, Quesenberry CP, Corley DA. Proton pump inhibitor and histamine-2 receptor antagonist use and iron deficiency. Gastroenterology. 2017.
- Finlayson-Trick E, Nearing J, Fischer JA, et al. The effect of oral iron supplementation on gut microbial composition: a secondary analysis of a double-blind, randomized controlled trial among Cambodian women of reproductive age. Microbiol Spectr. 2023.
- DeLoughery TG, Jackson CS, Ko CW, Rockey DC. AGA clinical practice update on management of iron deficiency anemia: expert review. Clin Gastroenterol Hepatol. 2024.
- McColl KE. Effect of proton pump inhibitors on vitamins and iron. Am J Gastroenterol. 2009.
- Eswaran S, Dolan RD, Ball SC, Jackson K, Chey W. The impact of a 4-week low-FODMAP and mNICE diet on nutrient intake in a sample of US adults with irritable bowel syndrome with diarrhea. J Acad Nutr Diet. 2020.
- Rusu IG, Suharoschi R, Vodnar DC, et al. Iron supplementation influence on the gut microbiota and probiotic intake effect in iron deficiency, a literature-based review. Nutrients. 2020.
- Cuisiniere T, Calvé A, Fragoso G, et al. Oral iron supplementation after antibiotic exposure induces a deleterious recovery of the gut microbiota. BMC Microbiol. 2021.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2025, September 27). Irritable bowel syndrome and anemia. Gut Pathways. https://gutpathways.com/articles/irritable-bowel-syndrome-anemia/