Testosterone therapy can keep the stomach feeling full
Anestis developed testosterone bloating, a heaviness after meals, alongside testosterone therapy and clomiphene. His case shows why sex hormone receptors in the gut wall control motility and pain sensitivity.
 Anestis's casecase study
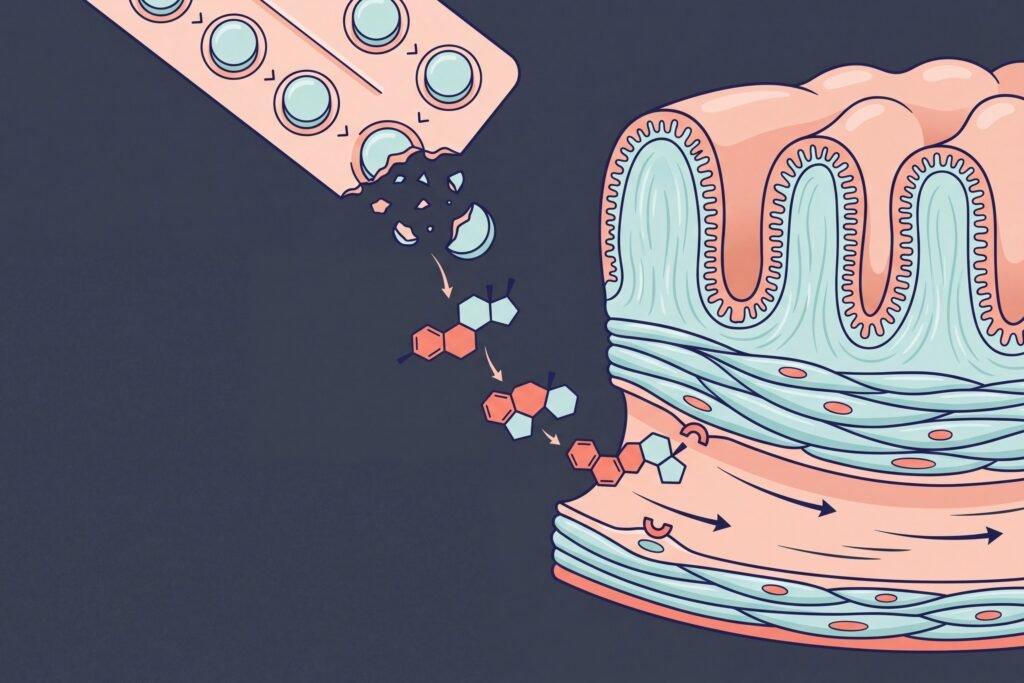
TRT and bowel problems share a mechanism in the hormone receptors of the gut wall. There, androgen and estrogen receptors control gut motility and pain sensitivity. Testosterone therapy and clomiphene change the hormone levels that reach those receptors, so both act on the gut.
Anestis, 48, starts both in January 2026, and within weeks he has daily bloating, heaviness after meals and almost no appetite. Yet his digestive symptoms stay even after the testosterone stops. Anyone who ends every day stuffed after normal meals will recognize this pattern.
Who is Anestis and what happened to his digestion before he came to us?
Anestis, 48, trained with weights five days a week
Anestis was 48 years old, 1.81 m tall and weighed 82 kg, with a BMI of 25, when he came to the practice where I work as a scientific collaborator. He lifted weights five times a week, often shortly after lunch. For about a year and a half he had eaten a ketogenic-style diet. It consisted of meat, eggs, feta, yellow cheese and a daily salad of kale, zucchini and green vegetables. He ate very fast and also drank about three liters of water a day with electrolytes.
He took no regular medication, but he used nimesulide or diclofenac a few times a year. For fifteen years he had smoked, but he had quit. In 1998 a neck injury fractured C4 and C5, and a cervical fusion then left eight titanium screws. He still had tingling in the left fingers, a left foot problem and spasticity in strong cold. On the family side, his father and paternal grandmother had Parkinson disease.
Bloating that grew through the day and almost no appetite
The symptoms started in mid-January 2026, in the same weeks as the two new drugs. He took testosterone for three to four weeks and stopped in mid-February, but the symptoms stayed. He linked the start of the symptoms to clomiphene, although those weeks were very stressful as well.
The distension was daily and intense, and it grew through the day. His hunger faded almost completely, while his stomach felt heavy and he felt the food staying there for hours. By contrast, he had no heartburn, acid reflux, nausea or vomiting. His bowel habits were stable, with almost daily formed stools and no constipation or diarrhea. In addition, he had frequent mouth ulcers. He tried probiotics for four weeks, but nothing changed.
Scopes and scans that found little
A gastroscopy found one very small gastric erosion, but his gastroenterologist considered it too minor to explain his symptoms. A colonoscopy then removed a polyp with negative histology, and an abdominal ultrasound on 9 April 2026 was normal. The ultrasound showed no findings in the liver, pancreas, spleen, kidneys, bladder or prostate, and no gallbladder stones.
A lactulose breath test was the only positive result, with a mild rise in methane just above the cut-off. His gastroenterologist discussed a course of rifaximin and neomycin, with twelve weeks of probiotics first. After four weeks, however, the distension, heaviness and low appetite were unchanged. A relative, an internist, then suggested an MRI of the abdomen.
Which mechanisms link TRT and bowel problems in his history, and which tests do we propose?
Both drugs change hormones that have receptors in the gut wall, and his symptoms began within weeks of starting testosterone and clomiphene. Bloating has several well-known causes, but in this case the hormonal cause comes first. Stress also acts on the same nerves, while diet, eating speed and training timing decide how much work the stomach does.
Which hormones do clomiphene and testosterone therapy change?
Clomiphene blocks estrogen receptors in the hypothalamus and pituitary.2 The brain then detects a low estrogen signal and raises its output, so the hypothalamus releases more GnRH (gonadotropin-releasing hormone). In response, the pituitary releases more LH (luteinizing hormone) and FSH (follicle-stimulating hormone), and LH in turn stimulates the testes to make testosterone.
- Estrogen receptors blocked
Clomiphene blocks estrogen receptors in the hypothalamus and pituitary.
- GnRH, LH and FSH rise
The brain reads a low estrogen signal and raises its output.
- More testosterone
LH stimulates the testes to make more testosterone.
- Estradiol and DHT
Aromatase turns part of it into estradiol, and 5-alpha reductase turns another part into DHT.
- Receptors in the gut wall
Androgen and estrogen receptors on gut nerves and muscle receive the changed signal.
Each step changes the hormone signal that finally reaches the gut.
The body converts testosterone, a steroid hormone, in two ways. First, the enzyme aromatase turns part of it into estradiol, the main estrogen. Second, the enzyme 5-alpha reductase turns another part into DHT (dihydrotestosterone), a stronger androgen. In the blood, SHBG (sex hormone-binding globulin) carries most of the testosterone, and as a result SHBG limits how much testosterone stays free.
TRT treats low testosterone by supplying testosterone from outside. The added testosterone lowers LH and FSH through negative feedback, so the testes make less of their own. Clomiphene, however, raises the same two hormones, and Anestis takes both, so opposing signals reach the pituitary and the testes at once. The resulting imbalance is systemic, because the blood carries the changes to every organ, including the gut.
All of these hormones travel to the digestive tract in the blood, and they find receptors waiting there. Enteric neurons (the nerve cells inside the gut wall) carry androgen receptors, while the colon carries estrogen receptors. The gastrointestinal tract makes hormones of its own as well, and several of them steer appetite. Ghrelin from the stomach raises hunger before meals, but once food arrives, CCK (cholecystokinin) and GLP-1 (glucagon-like peptide 1) rise.
These two signal fullness and slow the emptying of the stomach, so food stays there longer. Gut cells also release serotonin, which triggers motility reflexes and nausea. Because a stomach that stays full keeps sending fullness signals, hunger stays low. That cycle matters for Anestis, who has almost no appetite.
Why can testosterone treatment change how the gut moves and feels?
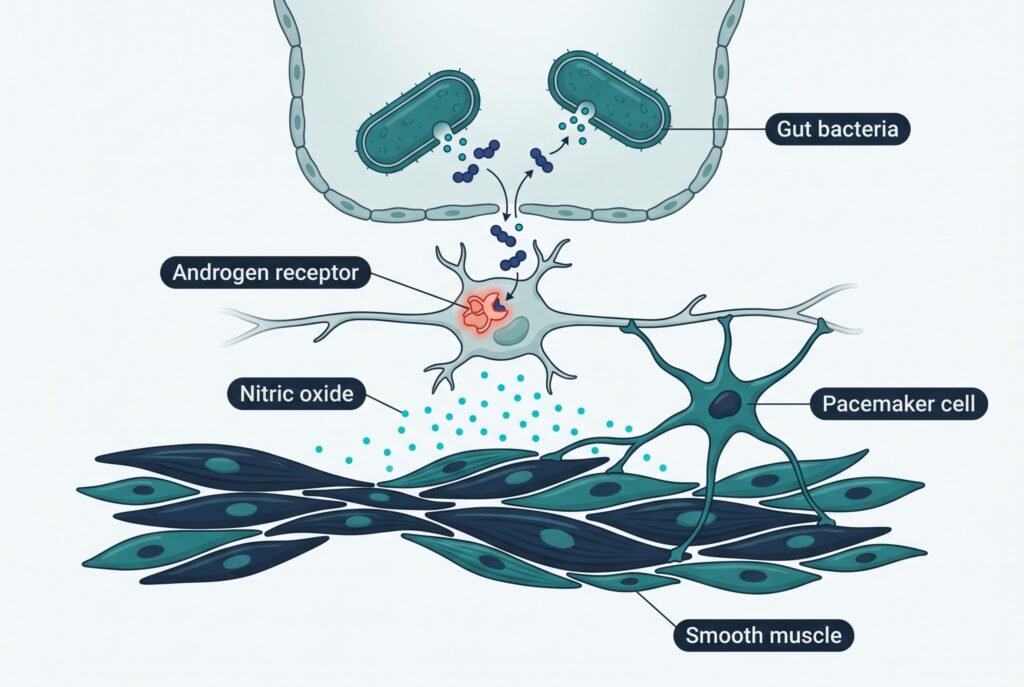
Receptors for androgens on Nos1 enteric neurons control the speed of colonic transit.1, 4 These Nos1 neurons release nitric oxide, a signal that relaxes gut muscle and lowers muscle tone. A large subset of enteric neurons also becomes androgen-responsive at puberty.1 The same signaling reaches Scn10a sensory neurons, the spinal afferents that carry gut signals to the spinal cord.4 In adult mice, both routes are required for normal gut transit.
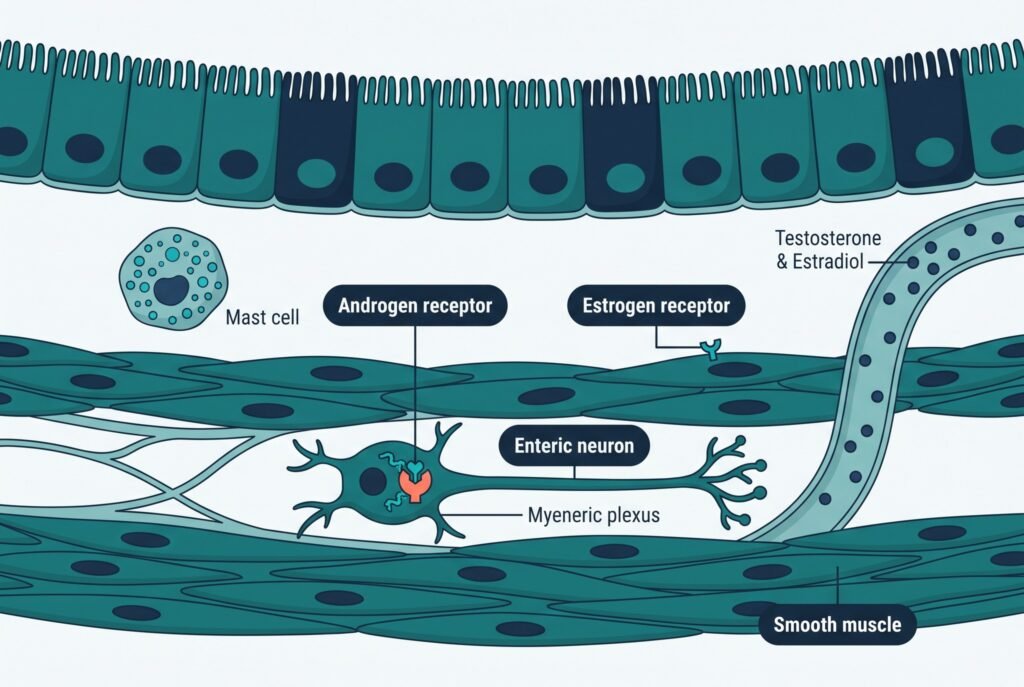
Removing androgens shows what these receptors do, because adult male mice had 40% slower gut transit four weeks after orchiectomy (removal of the testes).1 Their one-hour fecal output was 60% lower, and the pellets were 25% larger and drier. However, DHT supplementation restored normal transit time within three weeks.
“Supplemental DHT ... completely normalized the GI transit deficit in [orchiectomized] mice within 3 weeks.” Rastelli and colleagues, J Clin Invest, 2022
Human data show a similar link. Adults with IBS, a common functional gut disorder, have lower free testosterone than healthy controls, and lower levels also correlate with more severe symptoms.1 We cover that link in IBS and low testosterone.
In Anestis, both drugs change his testosterone levels, together with DHT and estradiol, within weeks. Slower motility keeps food in the stomach longer, while altered gut sensation makes a normal meal feel heavy. Anestis describes both, with food staying in his stomach for hours and heaviness after normal meals.
What do estrogen receptors do in the colon?
Estrogen receptors in the colon wall respond to estradiol, and aromatase makes estradiol from testosterone. Extra testosterone therefore raises the estrogen signal as well. GPER (G protein-coupled estrogen receptor) is present in the human colon.5 When tested in human and mouse colon, estradiol and the GPER agonist G-1 (a synthetic compound that activates GPER) reduced muscle contractility. In mice, both slowed bead expulsion (the time a small bead needs to leave the colon) and reduced pain behaviors.5
| Where the signal acts | What changes in the gut |
|---|---|
| Receptors for androgens on Nos1 enteric neurons | Transit speed. Lower androgen signaling slows transit in mice, and DHT restores it.1 |
| Receptors for androgens on Scn10a spinal afferents | Sensory nerve fibers that carry gut signals to the spinal cord. Their androgen signaling is also required for normal transit in mice.4 |
| GPER in the human colon | Muscle contractility falls, bead expulsion slows and pain behaviors drop in mice.5 |
| Aromatase, the enzyme that makes estradiol | Turns part of the testosterone into estradiol, so androgen and estrogen receptors both receive a changed signal. |
In these experiments, more estrogen signaling meant weaker muscle contractions and less pain behavior. Both treatments change the estrogen signal, so they alter gut function. TRT acts through aromatase, while clomiphene acts through the pituitary.
How does clomiphene reach the gut?
Clomiphene is absorbed readily from the GI tract and leaves the body mainly in the feces.2 Within five days about half of an oral radiolabeled dose is excreted, roughly 42% in the feces and 8% in the urine.2 So the drug passes the gut wall on the way in and again on the way out.
Adverse events with clomiphene in the label studies (% of patients)
Bloating stands for abdominal-pelvic discomfort, distention or bloating, and nausea includes vomiting. FDA label for clomiphene citrate, Table 2 (n = 8,029, studies in women). Ovarian enlargement (13.6%) and abnormal uterine bleeding (1.3%) are left out because they occur only in women.2
Among the events that occur in both sexes, this digestive event ranks second after hot flushes, followed by nausea and vomiting at 2.2%.2
Why do symptoms outlast the testosterone?
Zuclomiphene clears far more slowly than enclomiphene, its isomer (one of two forms of the same molecule with a different shape).2 As a result, zuclomiphene stays detectable for more than a month after dosing, and radiolabeled drug is still found in feces six weeks after administration.
- Day 0DoseClomiphene is absorbed readily from the GI tract.
- Day 5About 50%About half of a radiolabeled dose has left, 8% in urine and 42% in feces.
- Month 1Still thereZuclomiphene has a longer half-life than enclomiphene and stays detectable for more than a month.
- Week 6TracesRadiolabeled drug is still found in feces six weeks after administration.
Anestis stopped testosterone in mid-February, but the isomers of clomiphene clear over a longer period. At the same time, sensitized nerves prolong the symptoms further. A stretched gut wall excites them, so they respond more strongly to the next stretch.
How does the gut wall turn a normal stretch into pain?
Mast cells (immune cells that store histamine and tryptase) release their contents next to sensory nerve endings, so the nerves then fire at lower stretch. In nerve recordings, mediators released in IBS raised firing to 14.7 impulses per second, against 2.8 with control mediators.3 Blocking histamine H1 receptors cut the response by 51.7%, and inactivating serine proteases, the family that includes tryptase, cut it even further, by 74.5%.
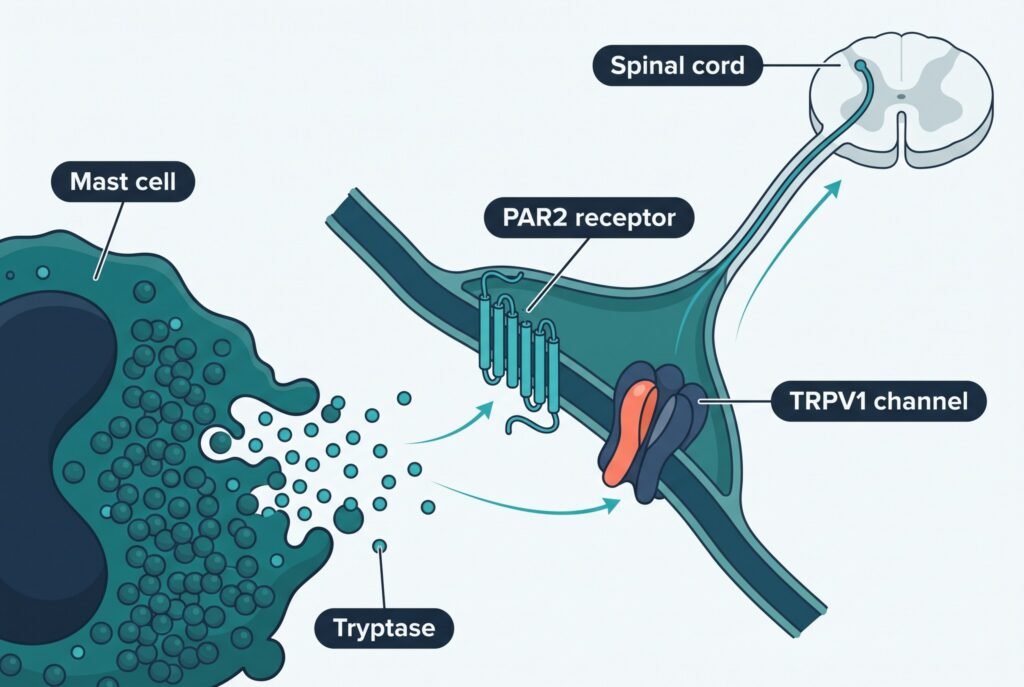
Tryptase activates PAR2 receptors on the nerve ending, and PAR2 signaling sensitizes the TRPV1 channel. A sensitized TRPV1 channel then opens at lower stretch. The result is visceral hypersensitivity, a lowered pain threshold in the gut that occurs in many people with IBS. So normal stretch produces abdominal pain or heaviness.
Stress acts on this pathway too, because CRF (corticotropin-releasing factor), a stress messenger of the brain, activates mast cells in the gut wall. Stress also limits gastric accommodation, the relaxation of the upper stomach that lets it receive a meal without a pressure spike. Anestis went through a very stressful period exactly when both treatments started. As a result, a normal meal feels heavy and bloated, even when the stomach empties on time.
What do a ketogenic diet and a daily salad do in the gut?
A very low carbohydrate diet removes most of the fermentable carbohydrate that gut microbes feed on, so fecal chemistry changes. An eight-week trial gave 91 overweight or obese adults energy-restricted diets.6 Fecal butyrate fell by 3.9 mmol/l on the very low carbohydrate diet but by only 0.5 mmol/l on the high-carbohydrate diet. Butyrate is the short-chain fatty acid that feeds the cells of the colon and supports gut health. Total short-chain fatty acids fell by 15.8 mmol/l on the low carbohydrate diet, whereas they rose by 1.4 mmol/l on the high-carbohydrate diet.
Daily fecal weight rose by 21 g on the high-carbohydrate diet, while it fell by 61 g on the very low carbohydrate diet.6 The two diets, however, produced the same rate of digestive discomfort in that trial. Still, Anestis had no digestive issues on his diet before January 2026.
His daily salad contains insoluble fiber and fermentable sugars such as raffinose, and gut microbes ferment these sugars into gas. Fast eating also swallows air, and a slow-emptying stomach then keeps air and food in place longer. As a result, sensitized nerves make the extra volume feel like distension. So the diet is an added load, but because hormones and stress changed the system first, we treat it as a secondary factor.
Can gut bacteria change how much androgen the gut receives?
The gut microbiota makes beta-glucuronidase, an enzyme that removes the sugar tag the liver adds to steroid hormones.4 This releases the active form again. Enteric Nos1 neurons raise their sensitivity to androgens at puberty, in parallel with shifts in bacterial beta-glucuronidase. In addition, a bacterial enzyme that processes androgen glucuronides restored neuronal signaling in antibiotic-treated mice.
Antibiotics disrupt gut microbes that reactivate androgens. In mice, seven days were enough to remove the receptors for androgens from enteric neurons, and serum testosterone fell while gut transit slowed markedly.4 Anestis has a mild rise in methane on his breath test, a sign of microbial activity in his gut. A fecal test therefore measures the gut microbiome composition directly.
Which tests separate these mechanisms?
Each test targets one of the mechanisms above, from gut microbes to the nerve supply, and we propose four groups. First, a blood and urine panel covers micronutrients, thyroid and pituitary markers, serum tryptase, blood count and urinalysis. Second, a fecal DNA test identifies the gut microbes, and fecal calprotectin replaces it when PCR is unavailable. Third, an MRI of the abdomen and a four-hour gastric emptying scan assess structure and stomach motility. Finally, an MRI of the cervical spine and spinal cord checks the nerve pathways that regulate the gut.
What are the potential side effects of TRT, including those related to the digestive system?
In the TRAVERSE trial, 5,246 men with low testosterone (hypogonadism) received testosterone gel or placebo.7 Major cardiovascular events occurred in 7.0% and 7.3% of the men, respectively. However, atrial fibrillation, acute kidney injury and pulmonary embolism occurred more often with testosterone replacement therapy. The gut is also a hormone-responsive organ. Androgen receptors on enteric neurons control gut motility in mice, and adults with IBS have lower free testosterone in proportion to symptom severity.1 Both findings therefore link androgen signaling to gut transit and to gut problems.
Infographic
Hormones reach the gut wall
Testosterone therapy and clomiphene change hormone levels that reach androgen and estrogen receptors in the gut wall.
Androgens and gut speed
In mice, androgen receptors on enteric neurons control the speed of colonic transit.
The estrogen signal rises
Aromatase turns part of the testosterone into estradiol, so extra testosterone raises the estrogen signal as well.
Clomiphene lingers
Zuclomiphene stays detectable for more than a month after dosing, which is one reason symptoms can outlast the testosterone.
Nerves turn stretch into heaviness
Sensitized gut nerves fire at lower stretch, so a normal meal can feel heavy even when the stomach empties on time.
Sources: Rastelli et al. 2022, FDA clomiphene label, Barbara et al. 2007.
gutpathways.com
 Save this infographicImage 4:5, with sources, from gutpathways.com
What do we expect the new tests to show about his gut motility and gut microbiome?
Three mechanisms can produce his symptoms, so each has its own test. They are slow emptying of the stomach, changed gut bacteria and a nerve or spinal cause.
His gastroenterologist considers the erosion too minor to explain the extent of his symptoms. Still, NSAIDs and past smoking both irritate the gastric lining.
The histology of the polyp is negative.
The liver, the gallbladder without stones, the pancreas, spleen, kidneys, bladder and prostate look normal, and the gallbladder wall is also normal.
Methane is just above the cut-off, and this is the only positive result so far. Methane also slows transit in the small intestine.
The panel lists homocysteine, zinc, ALP, 25(OH)D3, amylase, albumin, B12, folate and prolactin. It also includes serum tryptase, TSH, fT4, Lp(a), iron, transferrin saturation, TIBC, D-dimers, a complete blood count and urinalysis. These markers cover micronutrients, thyroid and pituitary function and mast cell activity.
A DNA test of the feces that shows which microbes dominate. Fecal calprotectin replaces it when PCR is unavailable and marks inflammation of the gut lining.
Checks the structure of the gut wall and the surrounding organs in more detail than the ultrasound.
Measures how much of a standard solid meal remains in the stomach over four hours.
Checks the level of the old injury, the fusion and the spinal cord.
What could the gastric emptying scan show?
The stomach empties a solid meal at a pace controlled by nerves, hormones and meal composition. A four-hour scan follows a labeled meal and measures how much remains at fixed times. Delayed emptying confirms a motility problem of the stomach, while a normal result makes sensation the main candidate. Sensation here means visceral hypersensitivity and the way the upper stomach relaxes to receive food.
Delayed emptying raises pressure against the lower esophageal sphincter, the valve at the top of the stomach. But Anestis has no heartburn, and his symptoms are fullness and heaviness.
The stomach depends on the vagus nerve and on sympathetic nerves. Descending pathways that regulate the sympathetic nerves of the gut run through the cervical spinal cord. Anestis has a cervical fusion, residual spasticity, tingling in the left fingers and a left foot problem, so the cervical MRI checks that region directly.
What could the stool and blood tests show?
Gut microbes leave a DNA signature in the feces, and stool PCR detects it. The test shows which microbes dominate and whether a pathogen is present. Fecal calprotectin, a protein released by white blood cells, further marks inflammation of the gut lining.
The breath test of Anestis shows a mild methane rise. In dogs, methane slowed gut transit by 59%, and in guinea pig ileum it raised contractile activity. In people with IBS, methane producers had a higher motility index.8 As a result, a slower small intestine holds gas and food longer, which produces distension even with regular stools. In mice, gut microbes regulate the receptors for androgens on enteric neurons.4 Stool PCR therefore covers part of the hormonal mechanism too.
Because he has frequent mouth ulcers, micronutrients come first. Low zinc, vitamin B12, folate or iron change the mucosa, and homocysteine rises when B12 or folate is low. Serum tryptase marks mast cell activity, which links to the visceral hypersensitivity described above. TSH and fT4 check the thyroid, whose hormones influence gut transit speed, while prolactin reflects pituitary function.
What could the MRI scans show?
MRI produces images of soft tissue from magnetic signals and uses no radiation. An MRI of the abdomen images the gut wall, the mesentery and the organs around the stomach. It also shows more structural detail than the ultrasound does.
The cervical MRI images the old fracture level and the spinal cord itself. It can show an old area of myelopathy or myelomalacia, meaning damage or softening of the cord. It can also show new narrowing and disease at the level next to the fusion. The scan further shows syringomyelia (a fluid cavity in the cord), tethering and the state of the fusion. Finally, the implant material is checked before the scan.
What do we recommend and how do we think it will help?
Each recommendation targets one mechanism behind his symptoms, from mechanical load to the autonomic state.
Why do we ask him to chew until the food becomes a smooth paste?
The stomach grinds solid food in its lower part, and only small particles pass the pylorus, the exit valve. Well-chewed food arrives already fragmented, so the stomach has less to grind. In 12 volunteers, 50 chewing cycles per bite shortened the lag phase of gastric emptying to 25.9 minutes, from 36.4 minutes with 25 cycles.9
Fast eating swallows air, which increases volume and causes belching. Since Anestis eats very fast and takes large bites, his stomach works harder at every meal. So we ask him to take small bites and to chew until the food becomes a soft, even paste. Chewing also starts the cephalic phase of digestion.
Why do we add seasonal vegetables and cook them first?
Each vegetable brings different fermentable carbohydrates such as pectin, inulin and hemicellulose, and each one favors different microbes. The very low carbohydrate diet in the trial above lowered fecal butyrate and total short-chain fatty acids.6 So a menu of meat, eggs, cheese and one salad gives the microbiome few substrates.
We start after the microbiome and blood tests are back, because they show his starting microbes and inflammation markers. In week one he eats 150 to 200 g of cooked vegetables a day, such as zucchini or carrot. He boils, steams or bakes them until soft.
From week two he adds one new vegetable every second day, up to ten different vegetables a week. Raw salads return once he tolerates the cooked vegetables. The increase stays gradual because a sudden jump in fiber raises gas, and his breath test already shows methane.
Why do we move weight training two to three hours after a meal?
Hard exercise redistributes blood from the gut to the muscles, so the gut wall receives less oxygen. In healthy men, one hour of cycling at 70% of maximum workload doubled I-FABP.10 This marker of injury to the cells lining the gut rose from 309 to 615 pg/ml. Small intestinal permeability also rose, meaning the gut wall let more substances through.
Anestis trains five days a week, often shortly after lunch. Eating raises blood flow to the gut, but lifting redirects blood toward the muscles. Occasional nimesulide and diclofenac irritate the stomach further, since both are NSAIDs (non-steroidal anti-inflammatory drugs) that block the prostaglandins protecting the gastric lining.
Next, we keep his five training days and lower the load. He works at an effort where he can speak in full sentences, about 5 to 6 out of 10. Each set stops with at least three repetitions in reserve. He trains at least two to three hours after a main meal and skips both NSAIDs on training days.
Can performance enhancement drugs affect gut functions?
Performance enhancement drugs reach the gut through hormone signaling. For example, anabolic-androgenic steroids act on receptors for androgens, and enteric neurons carry those receptors. In mice, androgen signaling controls the speed of colonic transit.1 Clomiphene also raises testosterone, and its label lists abdominal-pelvic distention in 5.5% of patients and nausea and vomiting in 2.2%.2 Hard training also affects the gut mechanically, since one hour of cycling raised a marker of gut cell injury in healthy men.10 Gut problems in athletes can therefore have hormonal, pharmacological and mechanical causes.
Why do we ask for three hours between dinner and sleep?
Gastric emptying follows a daily rhythm, so the same meal leaves the stomach more slowly in the evening. Anestis finishes dinner between 19:30 and 20:30 and sleeps at 22:00, so as little as 90 minutes pass. Between meals the gut runs a cleaning wave, the migrating motor complex (MMC), which stops each time food arrives. An earlier dinner therefore leaves a longer fasting window for the MMC.
We ask him to finish dinner by 19:00, which gives three hours before 22:00. Dinner becomes 120 to 150 g of fish or chicken with well-cooked vegetables and less added fat. Dense combinations of eggs, cheese and avocado move to lunch. After 19:00 he skips banana, cheese, nuts, calorie drinks and snacks, because new food restarts the postprandial (after-meal) phase. An easy 10 to 15 minute walk follows dinner.
Why do we ask for slow breathing before meals?
Slow diaphragmatic breathing raises parasympathetic activity, the branch of the autonomic nervous system that drives digestion. Stress or training, by contrast, raises sympathetic activity and reduces gastric accommodation. Anestis often comes to the table fast and tense, so three quiet minutes before the first bite give the stomach time to adapt.
First, he sits with his back supported and one hand low on the abdomen. He inhales through the nose for four seconds and exhales for six, about six breaths a minute. After three minutes of this, he waits about ten seconds and starts the meal with a small bite.
Ready
Press start and follow the circle for about three minutes, roughly 18 breaths, then wait ten seconds and start with a small bite.
Every case is different, so Anestis's plan describes his care and is not a plan for anyone else. Any change to a medicine or to testosterone treatment is always decided by his doctors.
Why do we think these steps will help his digestive symptoms?
The five steps target four mechanisms, namely the mechanical work of the stomach, the bacterial load, the autonomic state and the hormone signal. Chewing, moderate training timed away from meals and an early dinner reduce the mechanical work. As a result, smaller particles, steadier blood flow after meals and a longer fasting window mean less distension.
Cooked vegetables in rotation give gut microbes more substrates, and the microbiome test shows where to start. The gradual increase also keeps gas production low. Slow breathing before meals shifts the autonomic balance toward the parasympathetic state. With the earlier dinner, it further reduces the stretch that hypersensitive nerves turn into heaviness.
Testosterone treatment stopped in mid-February, and zuclomiphene clears over weeks after the last dose. The hormone signal at the gut receptors therefore steadies as the drugs clear. Finally, we review the test results and his response to these steps at the next visit.
Frequently asked questions
Added testosterone changes the hormone levels that reach gut neurons. In adult male mice, for example, androgen removal slowed gut transit by 40%, and DHT restored it.1 In this case, symptoms also began in the same weeks as the start of both drugs. Those hormone changes therefore act on gut motility and sensitivity through receptors on enteric and sensory neurons.
Androgen signaling sets the speed of colonic transit in mice, so a change in testosterone levels can change how fast the bowel moves.1, 4 Anestis, however, kept almost daily formed stools, and his symptoms sat higher, as fullness and heaviness after meals. A stool diary next to the treatment timeline shows which part of the gut is affected.
The clomiphene label lists abdominal-pelvic discomfort or distention in 5.5% of patients and nausea and vomiting in 2.2%.2 Clomiphene raises LH and FSH, so testosterone and estradiol rise, and these hormones in turn act on receptors in the gut wall. Zuclomiphene also stays detectable for more than a month after dosing.2
Visceral hypersensitivity means that gut nerves fire at lower stretch, so normal gas and food volumes feel heavy or painful. Mast cell mediators raised nerve firing to 14.7 impulses per second, against 2.8 with control mediators.3 Hormones change pain signals in animal models, and estradiol and the GPER agonist G-1, for example, reduced pain behaviors in mice.5 Androgen signaling to sensory neurons is also required for normal transit in mice.4
Zuclomiphene stays detectable for more than a month, and radiolabeled drug is found in feces six weeks after administration.2 Sensitized nerves prolong symptoms as well, because they keep firing at lower stretch.3 Finally, in mice, seven days of antibiotics removed receptors for androgens from enteric neurons and slowed transit.4
References
10 studies
- Rastelli D, Robinson A, Lagomarsino VN, et al. Diminished androgen levels are linked to irritable bowel syndrome and cause bowel dysfunction in mice. J Clin Invest. 2022.
- U.S. Food and Drug Administration. Clomiphene citrate tablets, prescribing information. DailyMed, National Library of Medicine.
- Barbara G, Wang B, Stanghellini V, et al. Mast cell-dependent excitation of visceral-nociceptive sensory neurons in irritable bowel syndrome. Gastroenterology. 2007.
- Lagomarsino VN, Robinson A, Mitchell PE, et al. Microbial reactivation of host androgens directs enteric neuronal regulation of gut motility. Nat Neurosci. 2026.
- Zielińska M, Fichna J, Bashashati M, et al. G protein-coupled estrogen receptor and estrogen receptor ligands regulate colonic motility and visceral pain. Neurogastroenterol Motil. 2017.
- Brinkworth GD, Noakes M, Clifton PM, Bird AR. Comparative effects of very low-carbohydrate, high-fat and high-carbohydrate, low-fat weight-loss diets on bowel habit and faecal short-chain fatty acids and bacterial populations. Br J Nutr. 2009.
- Lincoff AM, Bhasin S, Flevaris P, et al. Cardiovascular safety of testosterone-replacement therapy. N Engl J Med. 2023.
- Pimentel M, Lin HC, Enayati P, et al. Methane, a gas produced by enteric bacteria, slows intestinal transit and augments small intestinal contractile activity. Am J Physiol Gastrointest Liver Physiol. 2006.
- Pera P, Bucca C, Borro P, et al. Influence of mastication on gastric emptying. J Dent Res. 2002.
- van Wijck K, Lenaerts K, van Loon LJC, et al. Exercise-induced splanchnic hypoperfusion results in gut dysfunction in healthy men. PLoS One. 2011.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 20). Testosterone therapy can keep the stomach feeling full. Gut Pathways. https://gutpathways.com/case-studies/trt-and-bowel-problems/