A weak migrating motor complex sets the stage for SIBO
Roughly every one and a half to two hours between meals, the migrating motor complex, a quiet housekeeping wave, sweeps bacteria and leftover food out of the small intestine. When it weakens, SIBO often follows close behind.

What is the migrating motor complex, and why does your gut need it?
The migrating motor complex, or MMC, is the small intestine's own housekeeping wave: a recurring cycle of muscle contractions that clears leftover food, debris and bacteria from the stomach and small intestine once digestion has finished. It runs on a loop during fasting, between meals and overnight, and switches off when you eat again.6
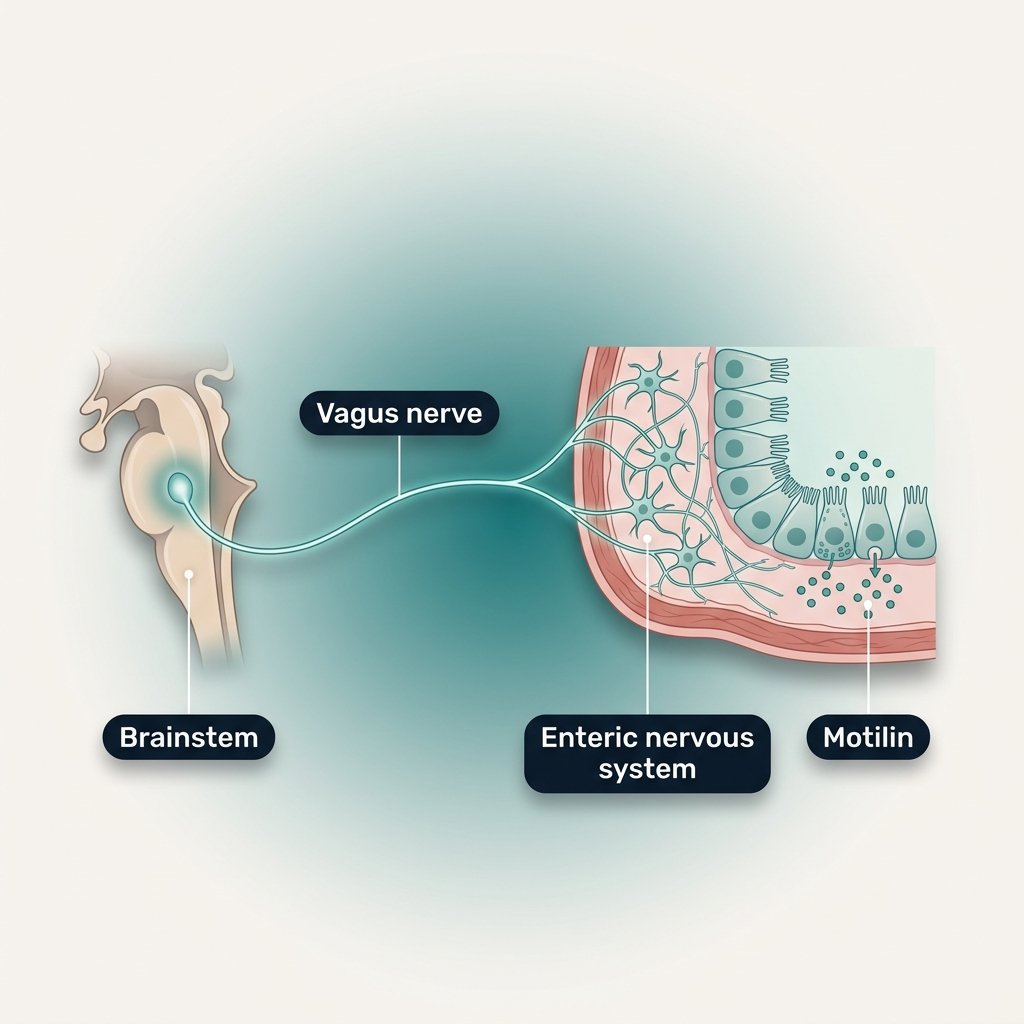
Several signals keep the clock running. Pulses of the hormone motilin, released from cells in the upper small intestine, start the strongest sweeps from the stomach, and the gut's own nervous system, the enteric nervous system, carries the wave along the small intestine.6, 8 The vagus nerve plays its main part in the stomach. After vagotomy, the stomach part of the cycle disappears, while the periodic activity of the small intestine continues.6
How does one migrating motor complex cycle unfold?
A single MMC cycle moves through four phases, each with its own job, before the pattern resets. The timing varies a lot from person to person and even within one person. In 30 healthy adults recorded for many hours, a phase III sweep appeared about 0.5 times an hour during fasting, roughly once every two hours.9
The trigger: brain, vagus and motilin start the cycle
Signals from the brain, the vagus nerve and motilin prime the stomach and small intestine for the next sweep, while the gut's own nerves keep the rhythm going further down.6

Phase I: a quiet resting phase
For roughly 40 minutes, contractions in the small intestine almost stop, and the gut rests before the next active phase.

Phase II: irregular contractions build up
Random, low-amplitude contractions appear and grow more frequent over about 50 minutes, building toward the strongest push of the cycle.

Phase III: the sweeping wave
For about 5 to 10 minutes, strong, regular contractions travel down the small intestine at peak strength, pushing leftover food, debris and bacteria ahead of them. This is the phase researchers count when they measure the MMC.6
Phase IV: a short taper back to rest
Contractions fade quickly, often too briefly to record, before the pattern resets and phase I begins again.

The reset: a meal switches off the cycle
Eating ends the fasting rhythm and switches the gut into the fed pattern, pausing the MMC until digestion finishes and the next cycle can start.6
How long does one complete cycle take?
A full cycle from phase I through phase IV usually takes about one and a half to two hours, with the sweep itself lasting only a small part of that time. The first detailed human study recorded a mean interval of 137 minutes between sweeps, and an infusion of motilin shortened it to 46 minutes.8
| Phase | Typical duration |
|---|---|
| Phase I, quiet rest | About 40 minutes |
| Phase II, contractions build | About 50 minutes |
| Phase III, the sweep | 5 to 10 minutes |
| Phase IV, quick taper | Brief, often too short to record |
| Full cycle, phase I to IV | About 1.5 to 2 hours, with wide variation |
In 14 healthy fasting adults, sweeps came at a mean interval of 137 minutes and followed a peak in motilin. An infusion of motilin brought on a sweep in 12 of 16 volunteers and shortened the interval to 46 minutes.8
How is the MMC different from peristalsis?
Peristalsis is the wave-like squeezing that moves a meal along the gut while you digest, which is the fed pattern. The MMC is the fasting pattern: a cleaning cycle that runs only when the stomach and small intestine are empty.6 Both use the same muscles, but they answer different needs.
Why does a stalled migrating motor complex lead to SIBO and IBS?
A weak or stalled MMC is one of the most consistent motility findings behind small intestinal bacterial overgrowth. Without regular sweeps, food residue and bacteria settle in the small intestine, right where they cause the most trouble. The first human description of the pattern already found an absent or badly disordered cycle in five patients with bacterial overgrowth, decades before SIBO became a familiar diagnosis.1
Phase III sweeps occurred 0.7 times per 4-hour recording in people with IBS and an abnormal lactulose breath test, against 2.2 times in healthy controls, and each sweep was shorter. People whose overgrowth had been cleared had more sweeps than those whose SIBO was still present.2
This lines up with what shows up in practice: people whose SIBO keeps returning after treatment often have a motility problem behind it. Clearing the bacteria without restoring the sweep tends to bring only temporary relief.
How do everyday habits retrain your migrating motor complex to fail?
Few people learn that their gut runs on a clock, so few learn to protect it. Like a muscle that needs regular use, the MMC needs real, uninterrupted fasting gaps to complete its four phases, and several everyday habits cut those gaps short. The table reflects practical observation built on the physiology above.
| Habit | How it interrupts the cycle |
|---|---|
| Eating too fast | Swallowed air and poorly chewed food add digestive work and can stretch the fed period before the next sweep. |
| Eating in front of a screen | Distracted eating tends to stretch meals out and blur snack and meal, so the gut rarely gets a clean start to its clock. |
| Grazing through the day | Frequent small snacks keep restarting the fed pattern, so a full cycle rarely gets the chance to finish. More in is snacking bad for digestion. |
| Eating late at night | A late dinner shortens the overnight fast, the longest natural window the MMC has to run several cycles. |
| Sipping sweet drinks or milky coffee between meals | Drinks with calories can interrupt a cycle in progress before phase III arrives. |
Which medical conditions and medications disable the migrating motor complex?
Beyond daily habits, several medical conditions and common medicines slow or disturb the MMC, and each one can raise the risk of SIBO through the same basic route: fewer or weaker sweeps, more time for bacteria to build up.
Hypothyroidism
In 50 people with a history of overt hypothyroidism, 54% tested positive for SIBO on a glucose breath test, against 5% of controls.3 A newer study found more than double the 10-year risk of SIBO, and the risk was lower in people taking levothyroxine.10 More in hypothyroidism and SIBO.
Gallbladder removal
After cholecystectomy, contractions within phase III were slower, the duodenal sweep travelled at about half its normal speed and phase III became shorter.4 See also SIBO after gallbladder removal.
Anticholinergic drugs
In a randomized trial of 26 healthy volunteers, atropine, which blocks muscarinic receptors, lengthened phase II of the MMC.5 Opioids and other drugs that slow the gut are also worth reviewing with a doctor.
How much does removing the gallbladder slow the sweep?
The duodenal part of phase III normally travels at about 16.2 centimeters per minute. After cholecystectomy, that speed drops to about 8.4 centimeters per minute, close to half its usual pace, and phase III also becomes shorter.4
Duodenal phase III propagation speed (cm per minute)
Perdikis 1994, converted from 0.27 and 0.14 cm per second.
After cholecystectomy, antral phase III contractions fell from 3.2 to 2.5 per minute, duodenal propagation slowed from 0.27 to 0.14 centimeters per second, and phase III shortened from 5.9 to 4.3 minutes.4
What helps you rebuild a healthy migrating motor complex?
Rebuilding a healthy MMC starts with giving it what it needs by design: real, uninterrupted gaps between meals. Four to five hours between daytime meals and a full overnight fast give the cycle room to complete several sweeps in a row. Plain water carries no calories and is generally not thought to switch on the fed pattern, while drinks with calories can.
Slower, undistracted meals let the fed pattern end on schedule, and cutting back on grazing and between-meal drinks gives phase III the space it needs. Herbal antimicrobial protocols can help clear an existing overgrowth,11 and pairing that work with motility support is what keeps the numbers down afterward. Fixing the underlying dysbiosis usually calls for a structured, sequenced approach over several weeks.
Give the migrating motor complex the fasting windows it was built to run, and much of its housekeeping work takes care of itself.
Frequently asked questions
Plain water has no calories and is generally not thought to stop the cycle. Drinks with sugar, milk or other calories can switch the gut into the fed pattern.7
It may work both ways. In one study, people whose overgrowth had been cleared had more phase III sweeps than those whose SIBO was still present, which suggests some recovery of motility after treatment.2
MMC dysfunction on its own causes few specific symptoms, but its effects show up clearly: bloating, gas, abdominal discomfort and changed bowel habits are common once bacterial overgrowth or gastroparesis develop.6 A doctor usually looks for the underlying condition with breath tests or motility studies, since the MMC itself is rarely measured outside research.
References
11 studies
- Vantrappen G, Janssens J, Hellemans J, et al. The interdigestive motor complex of normal subjects and patients with bacterial overgrowth of the small intestine. J Clin Invest. 1977.
- Pimentel M, Soffer EE, Chow EJ, et al. Lower frequency of MMC is found in IBS subjects with abnormal lactulose breath test, suggesting bacterial overgrowth. Dig Dis Sci. 2002.
- Lauritano EC, Bilotta AL, Gabrielli M, et al. Association between hypothyroidism and small intestinal bacterial overgrowth. J Clin Endocrinol Metab. 2007.
- Perdikis G, Wilson P, Hinder R, et al. Altered antroduodenal motility after cholecystectomy. Am J Surg. 1994.
- Halim MA, Gillberg L, Boghus S, et al. Nitric oxide regulation of migrating motor complex: randomized trial of N(G)-monomethyl-L-arginine effects in relation to muscarinic and serotonergic receptor blockade. Acta Physiol (Oxf). 2015.
- Deloose E, Janssen P, Depoortere I, et al. The migrating motor complex: control mechanisms and its role in health and disease. Nat Rev Gastroenterol Hepatol. 2012.
- Ouyang A, Sunshine AG, Reynolds JC. Caloric content of a meal affects duration but not contractile pattern of duodenal motility in man. Dig Dis Sci. 1989.
- Vantrappen G, Janssens J, Peeters TL, et al. Motilin and the interdigestive migrating motor complex in man. Dig Dis Sci. 1979.
- Soffer EE, Thongsawat S, Ellerbroek S. Prolonged ambulatory duodeno-jejunal manometry in humans: normal values and gender effect. Am J Gastroenterol. 1998.
- Wei M, Mehravar S, Leite G, et al. Relationship Between Hypothyroidism, Risk of Small Intestinal Bacterial Overgrowth, and Duodenal Microbiome Alterations. J Clin Endocrinol Metab. 2026.
- Chedid V, Dhalla S, Clarke JO, et al. Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Glob Adv Health Med. 2014.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, August 6). A weak migrating motor complex sets the stage for SIBO. Gut Pathways. https://gutpathways.com/articles/migrating-motor-complex-sibo/