Sleeping late brings stomach pain at night
Rondo's 9 p.m. dinner, his 12:30 a.m. bedtime, weaker oesophageal clearance when lying down and food triggers sustain stomach pain at night and in the morning, even after the stomach lining has healed.
 Rondo's casecase study
A delayed sleep schedule shifts gastric work into the biological night, when solid food empties more slowly and recumbency removes gravity from oesophageal clearance. The connection between sleeping late and stomach pain becomes stronger when late-night eating, disturbed digestion and lack of sleep occur together.
For Rondo, stomach pain at night or the following morning tracks a 9 p.m. meal and a 12:30 a.m. bedtime, while coffee, fried onion and large cocoa portions repeatedly worsen the same pattern.
How did Rondo's stomach pain become a recurring pattern?
Rondo, 41 years old
Rondo is 41, weighs 75 kg and has a BMI of 21.9 kg/m², and he came to the practice where I work as a scientific collaborator. His upper digestive symptoms began in 2015 during a period of intense stress and frequent nighttime eating. Reflux came first. Over time, the pattern expanded into epigastric pain, indigestion, post-meal fullness and early satiety.
Dinner at 9 p.m. and sleep at 12:30 a.m.
His final meal commonly includes bread, cheese and chicken at 9 p.m., followed by sleep around 12:30 a.m. Symptoms can appear after the meal or the next morning. Fast eating, daily sweets, pastries and dairy products add more gastric load to the same evening window.
Coffee, fried onion and cocoa reproduce the discomfort
Coffee, fried onion and a large amount of cocoa repeatedly precede pain, burning or a heavy stomach. Milk, alcohol and oversized meals also worsen symptoms. The pattern follows both food composition and quantity, which points toward reflux physiology, gastric retention and heightened sensitivity working together.
Clearance weakens when he lies down
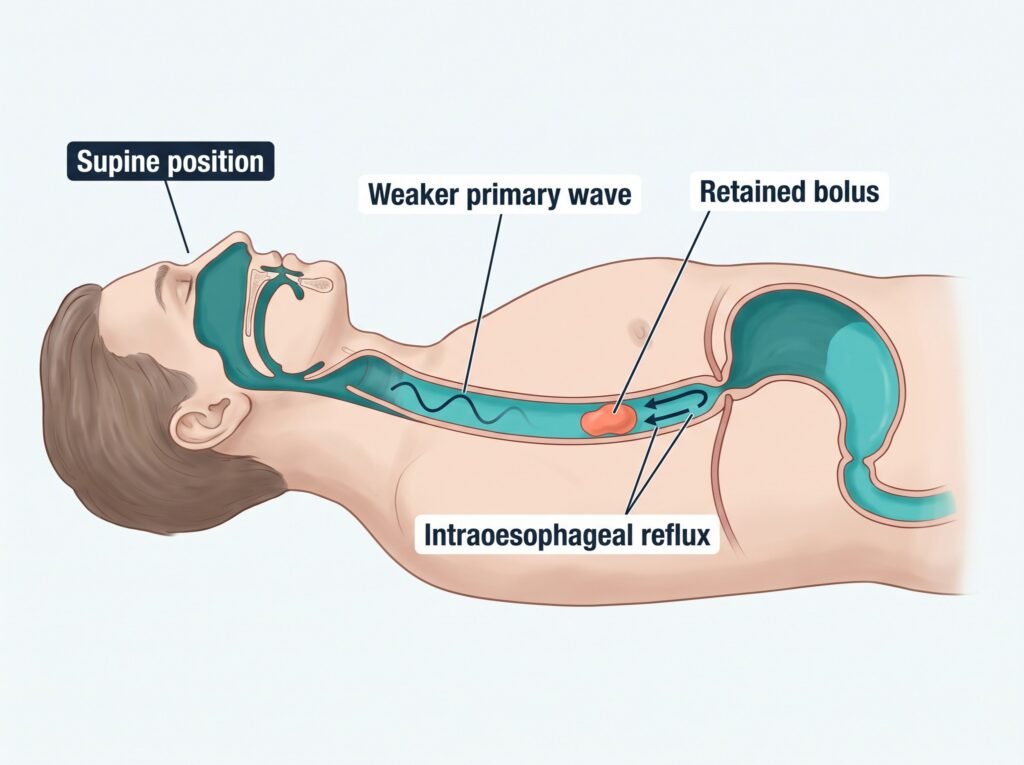
Videofluoroscopy found normal oesophageal motility while seated and in the oblique prone position. In the supine position, the primary peristaltic wave became weaker, part of the bolus remained inside the oesophagus and intraoesophageal reflux appeared. Residue was also recorded after yoghurt boluses.
The tissue improved while the symptoms continued
In 2022, endoscopy showed mild lower oesophageal sphincter insufficiency, grade 1 oesophagitis, excess gastric fluid, antral microerosions and an inflamed pyloric region. By January 2026, the oesophagus, stomach and duodenum looked normal. Yet dyspepsia, epigastric heaviness, early satiety and recurrent reflux symptoms continued with only partial relief from omeprazole.
- Clearance when lying down The primary wave weakens in the supine position and part of the bolus stays behind.
- Burning Reflux came first in 2015 and still returns after trigger foods.
- Heaviness and epigastric pain A late solid dinner stays in the stomach into the night, and the pain appears after the meal or the next morning.
Each point links one symptom with the part of the upper gut that produces it.
Why can sleeping late and stomach pain become linked?
Gastric emptying, acid secretion, gut hormones and mucosal cell renewal follow daily rhythms. In a human study, an identical solid meal took 53.6% longer to empty at 8 p.m. than at 8 a.m.1 Therefore, the same dinner creates a different mechanical burden when it moves toward the biological night.
Emptying time of the same solid meal (index, 8 a.m. = 100)
Goo 1987, 16 healthy men. Evening emptying took 53.6% longer.1
What changes after the meal moves into the night?
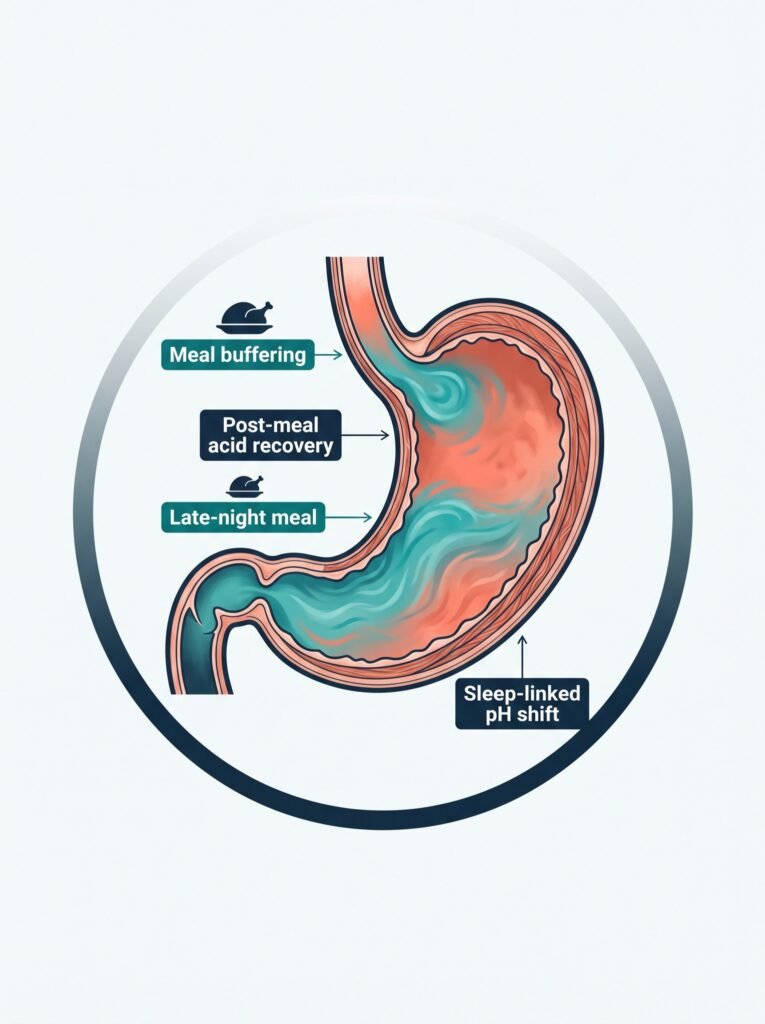
Food initially buffers stomach acid and raises luminal pH. Acid secretion then lowers the pH again while the stomach processes the meal. A late solid meal repeats this sequence close to sleep, so gastric volume and acid activity continue while Rondo is lying down. Meanwhile, his weaker supine primary wave clears retained material less efficiently.
Which hormonal signals shift with repeated late timing?
Its circadian rise coordinates sleep with gastrointestinal motility, secretion and mucosal protection. Late light exposure and delayed sleep move that signal later, while a late meal keeps the stomach active during the same window.
Its daily low point and morning rise become less aligned with behaviour. Repeated misalignment increases autonomic arousal and visceral sensitivity, so normal gastric distension feels more painful.
The largest pulse follows the first period of deep sleep. A delayed bedtime moves this tissue-repair signal later, and short sleep reduces the deep-sleep opportunity that supports epithelial renewal.
Its sleep-linked rise also moves with delayed sleep onset. Repeated delay shifts the repair and immune-regulation window across the night, while midnight itself carries no unique biological switch.
These opposing signals regulate acid output. Late meals stimulate the gastrin side of the system, while chronic PPI use raises gastrin through feedback from sustained acid suppression.
They help coordinate hunger, fasting contractions and the migrating motor complex. Repeated late eating shortens the overnight fasting interval and delays the clearance cycles that normally occur between meals.
What did the supine study add to the explanation?
The fluoroscopic finding supplies the mechanical link. Primary peristalsis normally clears swallowed material and refluxed contents. Rondo's primary wave weakened only when he lay down, precisely when gravity also stopped assisting clearance. A late meal therefore reaches the position in which his oesophagus performs less effectively.
Does a lifetime habit prove that the schedule fits?
"I've always slept late, and that's what suits me."
Fair enough. The stomach, inconveniently, follows circadian biology without consulting personal tradition. A familiar schedule can feel comfortable while the natural circadian rhythm, evening gastric emptying, sleep-linked hormones and Rondo's supine clearance finding still register the physiological cost.
Why does my stomach hurt after sleeping late or poorly? I can wake with epigastric pain even when I felt little discomfort at bedtime.
Late or disrupted sleep changes several processes that determine how strongly the upper digestive tract responds to a meal. Evening solids empty more slowly, recumbency reduces gravitational clearance, and circadian misalignment changes autonomic tone, acid regulation and visceral sensitivity. Consequently, gastric distension or a short reflux episode can produce more pain, fullness or nausea. Sleep deprivation also lowers pain thresholds. Therefore, the same mechanical stimulus can generate a stronger conscious sensation after waking, especially when the lack of sleep follows late-night eating.
How closely are sleep disturbance and functional dyspepsia linked?
In a study of 201 people with functional dyspepsia and 325 healthy controls, sleep disorders were more than twice as common with chronic dyspeptic symptoms.3
Why did we recommend only one new diagnostic test?
Rondo has already had the structural questions examined from several directions. Videofluoroscopy assessed bolus transit. Endoscopy and biopsies assessed the oesophagus, stomach and duodenum. Colonoscopy, ileal biopsies and magnetic resonance enterography examined the lower digestive tract. The normal 2026 endoscopy also confirmed that active erosive disease no longer explains the continuing symptoms.
- Faecal calprotectin, September 2025High
289.3 μg/g. This is the remaining objective inflammatory signal, and it sits outside the upper-GI behavioural pattern.
- Vitamin B12In range
540 pg/mL, within the laboratory reference range.
The dot shows where each result sits. A repeat faecal calprotectin is recommended, because it is the one value that still needs an answer.
Normal seated and oblique-prone motility. Supine testing produced a weaker primary wave, partial bolus retention and intraoesophageal reflux.
Grade 1 oesophagitis, mild lower sphincter insufficiency, excess gastric fluid, antral microerosions and mild chronic inactive gastritis without Helicobacter pylori, atrophy or intestinal metaplasia.
Normal transit and bowel-wall appearance, without thickening, pathological enhancement, obstruction or imaging evidence of inflammatory bowel disease.
No erosive oesophagitis, Barrett's oesophagus, hiatal hernia or pathological gastric and duodenal mucosal lesions. The examination described much of the symptom burden as functional.
Why does the current pattern look behavior-driven?
Persistent symptoms now track sleep timing, meal timing, speed of eating and named food triggers more closely than visible tissue injury. We often see this split after mucosal healing, because the camera looks reassuring while motility and sensory signalling still reproduce the person's symptoms. That is why the active upper-GI problem is best described as a behavior-maintained functional pattern.
How much does dinner-to-bed timing matter?
A matched study found that an interval under three hours carried 7.45 times the odds of GERD compared with an interval of at least four hours.2 Rondo's usual interval is about three and a half hours, yet his dinner is solid and calorie-dense, and his supine clearance is already weaker. The combined pattern matters more than the clock time alone.
Which changes address the mechanism behind the stomach pain?
- DinnerBread, cheese and chickenFinished by 19:00
- BedtimeAround 12:30 a.m.Near 11 p.m., every day
The final solid meal moves earlier on four or five days a week, and bedtime moves toward 11 p.m.
Finish the final meal earlier
The final solid meal moves to 7 p.m. on four or five days each week. This creates a longer upright interval for gastric emptying and oesophageal clearance. On later days, a smaller meal reduces distension and the volume available for nighttime reflux.
Stabilize sleep near 11 p.m.
Bedtime moves toward 11 p.m. with a similar schedule across weekdays and weekends. The target supplies a repeatable relationship between food intake, darkness and sleep onset. Midnight itself carries no special switch. Consistency gives central and digestive clocks the same timing signal each day.
Remove the three repeatable food triggers
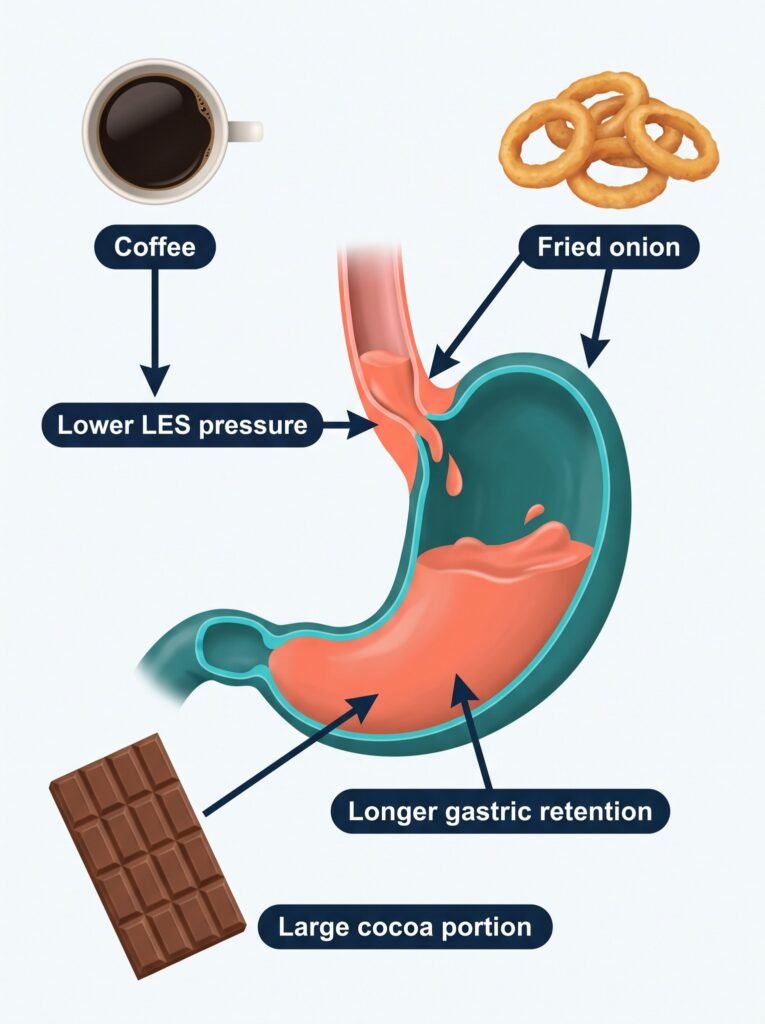
Coffee, fried onion and large cocoa portions leave the diet during the initial observation period. Coffee and chocolate reduce lower oesophageal sphincter pressure in controlled human studies.4, 5 Onion increased reflux measurements in reflux-prone participants, while frying adds a fat load that prolongs gastric retention.6 Together, they form a mechanism-matched personal trigger set.
Chew until each solid mouthful is easy to swallow
Slower chewing reduces particle size and produces a cohesive, saliva-mixed bolus. This directly answers the partial bolus retention seen when Rondo lay down. It also slows the meal itself, which reduces rapid gastric distension and the post-meal pressure that promotes reflux.
Use three minutes of diaphragmatic breathing before meals
Slow abdominal breathing shifts autonomic activity toward the parasympathetic state that supports gastric accommodation. It also recruits the diaphragmatic crura around the lower oesophageal sphincter. For a symptom pattern that began during intense stress and still worsens with fast eating, this changes the mechanical setting before the first bite.
Ready
Press start and follow the circle for three minutes before the meal. Slow breaths shift the nervous system toward digestion.
Spread hydration and movement across the day
Water increases gradually from two glasses toward six to eight, distributed between meals. Daily moderate walking adds a regular motility signal without placing intense exercise beside a large meal. Together, these changes support gastric and bowel transit while reducing the tendency to concentrate food and fluid late in the day.
Review chronic omeprazole use without an abrupt stop
Omeprazole has produced only partial relief, while the 2026 endoscopy shows no erosive oesophagitis, Barrett's oesophagus or active gastric injury. That combination calls for a fresh indication review with his doctor. Chronic acid suppression also raises gastrin through feedback, which helps explain rebound acid symptoms after withdrawal. Current guidance bases deprescribing on the continuing indication and recognizes transient rebound symptoms after long-term treatment.7 A structured step-down, decided by the doctor, keeps rebound distinct from recurrent tissue damage.
What does the current vitamin B12 result mean?
His vitamin B12 is currently 540 pg/mL, within the laboratory reference range. The present priority is medication fit. The longer-term nutrient mechanism is explained separately in PPIs and vitamin B12 deficiency. The wider role of normal gastric acidity is covered in why the gut is acidic and should stay acidic.
Can stress or eating late at night cause stomach pain? Sometimes the discomfort appears that night, while on other days it is strongest the next morning.
Stress and late eating can produce the same symptom through different routes. Stress increases sympathetic activity and visceral sensitivity, which changes gastric accommodation and makes distension more painful. A late meal adds volume during a period of slower solid-food emptying and places refluxable contents close to recumbency. The effects persist into the morning when gastric clearance remains incomplete or sleep fragmentation lowers the pain threshold. Together, these mechanisms explain why symptoms can appear immediately or after waking.
Every case is different, so Rondo's plan describes his care and is not a plan for anyone else. Any change to omeprazole is always decided by his doctor.
Why is this mainly a behavior-maintained digestive problem?
The active upper-digestive pattern follows repeated behaviours more closely than progressive tissue injury. Symptoms track a late solid dinner, delayed sleep, fast eating and specific foods. Meanwhile, the latest endoscopy shows healed mucosa, and omeprazole has changed the symptoms only partly. This combination places motility, reflux clearance and visceral sensitivity at the centre of the current problem.
Why does the calprotectin result remain separate?
Faecal calprotectin of 289.3 μg/g is the one objective result that still needs resolution. A repeat measurement answers that question without reopening every structural investigation. If it stays high, the lower digestive tract requires renewed attention. If it normalizes, the extensive prior imaging, biopsies and normal 2026 endoscopy support the behavior-first plan even more strongly.
What changes the pattern in practice?
In our experience with similar symptom patterns, progress comes when the relevant behaviours change together and remain stable long enough for the digestive rhythm to follow. Earlier food intake reduces the nighttime mechanical load. Consistent sleep restores a repeatable circadian signal. Trigger removal reduces reflux-provoking exposures, while structured medication review prevents acid suppression from becoming the only response to every flare.
Where reflux fits into the wider pattern
The same distinction between reflux injury and persistent symptoms is explored in acid reflux without heartburn. Rondo's case adds one unusually useful detail, since the oesophagus itself showed how position changed clearance, so the daily schedule is part of the measured physiology.
Frequently asked questions
The first step is finding what drives it with your doctor, because reflux, delayed emptying, ulcers and other conditions can all cause it. When timing is part of the pattern, an earlier and smaller last meal, a regular bedtime and a few hours upright after dinner reduce the load that reaches the night. In a matched study, less than three hours from dinner to bed carried 7.45 times the odds of GERD.2
At night the stomach empties solids more slowly, and lying down removes gravity from oesophageal clearance.1 Acid that stays in contact with the oesophagus, or a stomach that is still full, can then reach awareness during lighter sleep. Pain that wakes you regularly always needs a medical assessment.
A bedtime after midnight becomes relevant when it accompanies late food intake, circadian delay or an inconsistent schedule. Evening solids empty more slowly, and lying down removes gravitational assistance from oesophageal clearance. The clock time therefore marks a cluster of physiological conditions. Midnight itself is simply one point on the biological night.
Endoscopy shows visible tissue structure. Functional dyspepsia can persist through altered gastric accommodation, delayed emptying, reflux clearance, visceral hypersensitivity and autonomic signalling even after erosions or inflammation have healed. A normal-looking lining and continuing symptoms describe different parts of digestive function.
Yes. Coffee and chocolate can reduce lower oesophageal sphincter pressure. Onion increased measured reflux in people with reflux symptoms, while frying adds fat that can extend gastric retention.4, 5, 6 These separate actions converge on reflux exposure, post-meal fullness and epigastric discomfort.
Long-term acid suppression raises gastrin through feedback. When the drug is withdrawn, acid output can temporarily exceed the previous level and produce heartburn, regurgitation or dyspepsia.7 This rebound can feel like recurrence of the original disease even when the underlying tissue remains healed.
References
7 studies
- Goo RH, Moore JG, Greenberg E, Alazraki NP. Circadian variation in gastric emptying of meals in humans. Gastroenterology. 1987.
- Fujiwara Y, Machida A, Watanabe Y, et al. Association between dinner-to-bed time and gastro-esophageal reflux disease. Am J Gastroenterol. 2005.
- Park JK, Huh KC, Kwon JG, et al. Sleep disorders in patients with functional dyspepsia: a multicenter study from the Korean Society of Neurogastroenterology and Motility. J Gastroenterol Hepatol. 2021.
- Pehl C, Wendl B, Pfeiffer A, Schmidt T, Kaess H. The effect of decaffeination of coffee on gastro-oesophageal reflux in patients with reflux disease. Aliment Pharmacol Ther. 1997.
- Wright LE, Castell DO. The adverse effect of chocolate on lower esophageal sphincter pressure. Am J Dig Dis. 1975.
- Allen ML, Mellow MH, Robinson MG, Orr WC. The effect of raw onions on acid reflux and reflux symptoms. Am J Gastroenterol. 1990.
- Targownik LE, Fisher DA, Saini SD. AGA Clinical Practice Update on De-Prescribing of Proton Pump Inhibitors. Gastroenterology. 2022.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 20). Sleeping late brings stomach pain at night. Gut Pathways. https://gutpathways.com/case-studies/sleeping-late-and-stomach-pain/