Acid reflux without heartburn lands in the throat
Acid reflux without heartburn usually means the reflux reaches the throat, a pattern called silent reflux. Pepsin can rest on the throat lining and switch on again the next time acid reaches it, with no burning chest to warn you.

Could I have acid reflux without heartburn?
Yes. Acid reflux without heartburn is a well recognized pattern. Stomach contents can travel high enough to reach the throat and voice box while barely touching the esophagus, so the burning chest never appears. Doctors call this laryngopharyngeal reflux, or LPR. Because it behaves differently from classic gastroesophageal reflux disease (GERD), it often goes unnoticed for months.
The confusion is understandable. A chronic cough, a hoarse voice or the feeling of a lump in the throat points to the ear, nose and throat clinic long before anyone thinks of the stomach. As a result, many people go through allergy tests, chest imaging and voice rest first. The one symptom everyone expects, heartburn, is missing.
Even so, the reflux is real. It shows up on laryngoscopy and in symptom scores built for this exact pattern, and it follows a clear mechanism once someone looks at the throat and voice box.
What is silent reflux (LPR)?
Silent reflux, or laryngopharyngeal reflux, happens when stomach contents pass the upper esophageal sphincter and reach the throat, the voice box and the back of the nose. In other words, the reflux goes well beyond the esophagus and its lower sphincter. That single difference in location changes how the condition feels and how it is managed.
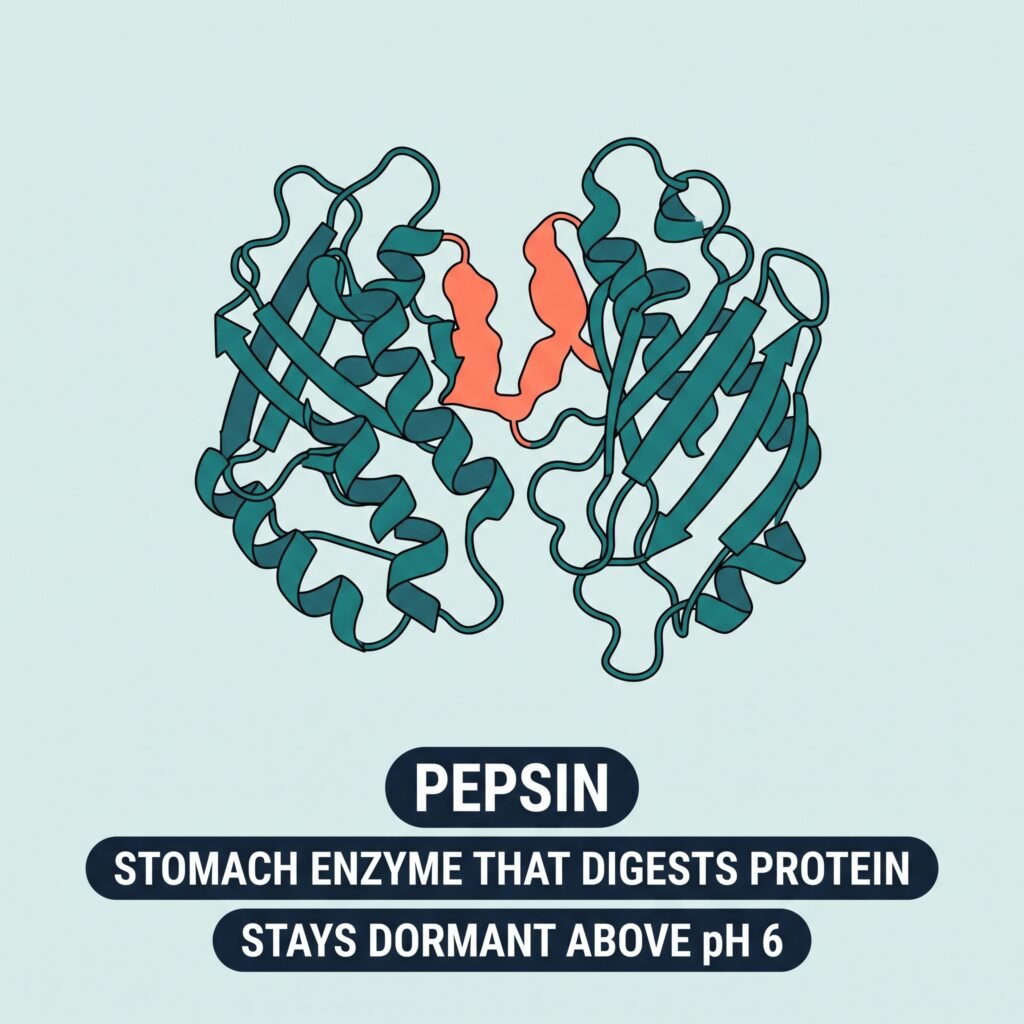
Acid plays a part, but pepsin, the stomach enzyme that digests protein, is the more persistent problem. Pepsin is stable up to pH 7, so it can stick to throat tissue in an inactive state. Then, when a later and even mildly acidic reflux event lowers the local pH, it becomes active again.1
Pepsin is stable up to pH 7 and regains its activity when the tissue is acidified again. It sticks to laryngeal cells, depletes their defenses and causes further damage after the cells take it in.1
How LPR differs from classic GERD
Classic GERD is mainly a problem of the lower esophageal sphincter. Acid pools in the esophagus, which has real defenses: a mucus layer, bicarbonate and fast clearance by its muscle waves. For this reason, the esophagus can take a fair amount of acid before it complains, usually with heartburn.
The larynx has far less protection. In biopsies from people with LPR, the protective enzyme carbonic anhydrase III was mostly missing and the cell junction protein E-cadherin was reduced, while pepsin was found inside the cells. None of this was seen in the controls.8 This means a short and weak reflux event that the esophagus would barely notice may still irritate the throat. That explains why silent reflux can cause voice and airway symptoms that seem out of proportion to how little reflux takes place.
What are the symptoms of silent reflux?
The symptoms of silent reflux center on the throat, the voice and the airway, because that is where the reflux lands. Most people notice a group of these symptoms building slowly, which is part of why the pattern is missed.
- A hoarse or strained voice, often worse in the morning
- Frequent throat clearing that turns into a habit
- A chronic cough with no clear chest cause
- The feeling of a lump in the throat between meals
- Post-nasal drip that does not respond to allergy treatment
- Mild difficulty swallowing some foods
- A raw, irritated throat by the evening
Throat and voice symptoms
Hoarseness and frequent throat clearing are usually the first symptoms people notice. Singers and teachers, who rely on their voice, often catch the pattern earliest. The irritation tends to build through the day and peaks by the evening or after a long stretch of talking. That timing may fit repeated, low-grade pepsin exposure that adds up over the day. An acid reflux sore throat that never comes with heartburn belongs to the same picture.
Digestive and airway symptoms
Acid reflux cough, post-nasal drip and a mild catch when swallowing complete the picture. Doctors often treat them as allergy or sinus problems first. Chest burning is uncommon in this pattern, so its absence is a clue in its own right and points toward LPR.
How is silent reflux diagnosed?
Silent reflux is diagnosed mainly with a symptom score and a direct look at the throat. The endoscopy and pH tests built for classic GERD focus on a different part of the anatomy and often miss it. A gastroenterologist or an ENT specialist usually starts with a short questionnaire and then examines the throat with a laryngoscope.
| Method | What it shows and where it falls short |
|---|---|
| Reflux Symptom Index, a nine-item questionnaire | Captures throat and voice complaints quickly. A score above 13 was considered abnormal in its validation study, so it works as a screening signal.2 |
| Laryngoscopy with the Reflux Finding Score | Shows visible irritation of the throat and voice box. Mild changes can also come from allergies, smoking or voice strain.3 |
| Dual-probe or pharyngeal pH monitoring | Can catch reflux events that reach the throat. Events are often brief, so results are read together with symptoms and laryngoscopy.1 |
| A supervised trial of acid suppression | Used as a practical diagnostic step. The response adds to the overall clinical picture.9 |
That is why the condition has a reputation for being hard to diagnose. No single test is a full gold standard, so most doctors combine the questionnaire, the laryngoscopy and the response to a treatment trial into one picture. A gastroenterologist usually leads the work-up when gut symptoms sit next to the throat complaints. An ENT specialist is often the first stop when hoarseness or a chronic cough dominates. In practice, the two specialties often work together.
How do you heal or treat silent reflux?
Treatment usually starts with lowering acid production, most often with a proton pump inhibitor (PPI), together with the habits that make reflux less frequent. PPIs help many people, and they are a reasonable first step because they are simple to start and to monitor. Guidance for GERD with symptoms outside the esophagus also allows a PPI trial.9
The limits of PPIs on their own
PPIs raise stomach pH, which helps. However, pepsin bound to throat tissue can still irritate once it is reactivated, and the reflux events keep happening even when the fluid is less acidic. A review on pepsin in reflux noted that PPIs do not help the majority of people with reflux outside the esophagus, while specially formulated alginates, which trap pepsin, gave benefit.1
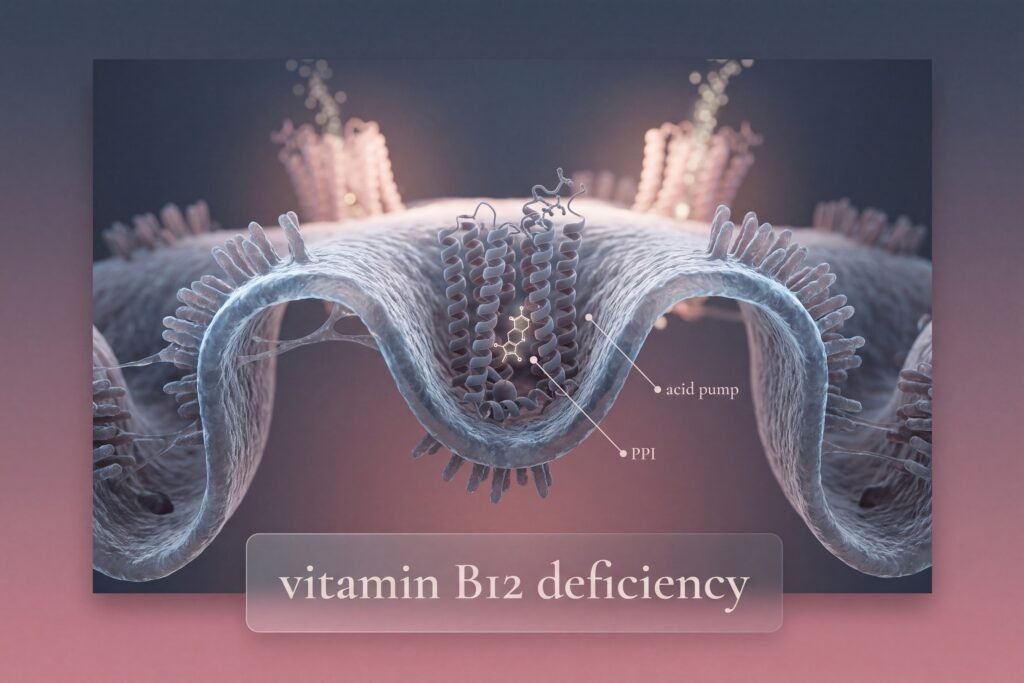
In the practice where I work as a scientific collaborator, the gut side of this story tends to grow the longer PPI use continues. After about six weeks on a PPI, changes in the gut bacteria tend to add up, because stomach acid is also the body's first checkpoint against swallowed microbes. Long-term use also affects nutrients, as explained in PPIs and vitamin B12 deficiency.
Across 29 studies, PPI users had about twice the odds of small intestinal bacterial overgrowth (OR 2.14). Each extra month of PPI therapy went with a rise of about 4.3 percentage points in SIBO prevalence.10
The longer acid suppression continues, the more deliberate the rebuilding work needs to be: stomach acid function, gut motility and a stable gut community, restored in order. It takes more work the longer the problem has been left alone, but it remains workable with the right sequence. The approach is described in oregano oil for SIBO, and a real example is George's PPI case.
From acid suppression to IBS-like symptoms
A case from IBSyncrasy, told in three steps.
- The trigger
A person on long-term PPI therapy for reflux developed bloating, changing bowel habits and IBS-like symptoms that seemed unrelated to the original prescription.
- The tests
Testing linked the bowel symptoms to low stomach acid, a weaker microbial barrier and small intestinal bacterial overgrowth, all traceable to the same root cause.
- The outcome
Correcting the picture meant restoring digestive function step by step, a sequence documented in the book.
One case cannot prove a rule. It does show why long-term acid suppression deserves a look at the whole gut.
What lifestyle changes help with silent reflux?
Sleep and meal timing change reflux risk directly, whatever medicine you take. Both affect how much stomach content is available to move upward and how easily gravity can keep it down. On top of that, a few specific changes make a measurable difference.
Sleep position and quality
Lying flat removes the help of gravity, so reflux events tend to cluster in the first part of the night, while the stomach is still working on dinner. In a study of nighttime pH monitoring, lying on the right side went with more acid exposure and slower acid clearance than the left side, back or front, and the authors recommended the left side.4 A review of lifestyle measures reached the same conclusion for the left side and for raising the head of the bed.6
Move your last meal earlier
Lying down with a full stomach is one of the most reliable triggers of nighttime reflux, since digestion has barely started and pressure in the abdomen stays high. In a Japanese study, people who went to bed less than three hours after dinner had 7.45 times the odds of GERD compared with those who waited four hours or more.5 Finishing the last meal at least three hours before bed gives the stomach time to empty.
More targeted changes
Each of these lowers the pressure on the lower sphincter or the number of reflux events.
Raise the bed frame
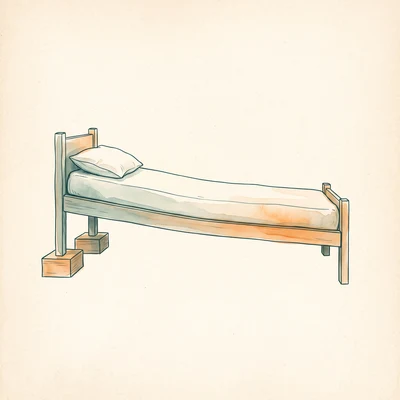
Raise the head of the bed frame itself by six to eight inches with risers under the legs, so gravity works all night in every position. Head-of-bed elevation improved esophageal acid exposure in the lifestyle review.6
Smaller, lower-fat meals
High-fat meals lower the pressure of the lower esophageal sphincter.6 Smaller portions, eaten slowly, may also mean less stretch on a full stomach.

Loose waistbands
Anything that squeezes the abdomen may push on the lower sphincter, so loosen tight belts and skip sit-ups right after meals.

Less smoking and alcohol
Both were linked to LPR in the Greek population survey.7
In 20 people whose LPR did not improve despite twice-daily PPIs, a strict low-acid diet, with all foods and drinks below pH 5 removed for at least two weeks, improved symptoms in 19 of them. Both the symptom score and the throat findings improved.11
None of these changes means giving up medicine if you and your doctor decide it belongs in the plan. Instead, they lower how often reflux reaches the throat, which is the real target. Fewer events mean less pepsin on tissue that has few defenses against it. Reflux without heartburn is easy to miss for months because the expected warning never shows up. Once the throat and voice symptoms are recognized for what they are, though, the way forward combines a clear mechanism with specific, workable steps.
Frequently asked questions
Yes. When reflux reaches the throat and voice box, the burning chest can be absent. This pattern is called silent reflux or laryngopharyngeal reflux, and cough, hoarseness and throat clearing are the more common signs.1
Laryngopharyngeal reflux happens when stomach contents pass the upper esophageal sphincter and reach the throat and voice box. Pepsin, the stomach's protein-digesting enzyme, can stay on that tissue and become active again with a later reflux event.1
Neither one is worse in general. LPR involves less reflux overall, but the throat has fewer defenses than the esophagus, so small amounts can cause lasting irritation of the voice box.8
Many people improve a lot when reflux events become less frequent. In a small study of people who did not respond to PPIs, a strict low-acid diet improved symptoms in 19 of 20.11
References
11 studies
- Bardhan KD, Strugala V, Dettmar PW. Reflux revisited: advancing the role of pepsin. Int J Otolaryngol. 2012.
- Belafsky PC, Postma GN, Koufman JA. Validity and reliability of the reflux symptom index (RSI). J Voice. 2002.
- Belafsky PC, Postma GN, Koufman JA. The validity and reliability of the reflux finding score (RFS). Laryngoscope. 2001.
- Khoury RM, Camacho-Lobato L, Katz PO, et al. Influence of spontaneous sleep positions on nighttime recumbent reflux in patients with gastroesophageal reflux disease. Am J Gastroenterol. 1999.
- Fujiwara Y, Machida A, Watanabe Y, et al. Association between dinner-to-bed time and gastro-esophageal reflux disease. Am J Gastroenterol. 2005.
- Kaltenbach T, Crockett S, Gerson LB. Are lifestyle measures effective in patients with gastroesophageal reflux disease? An evidence-based approach. Arch Intern Med. 2006.
- Spantideas N, Drosou E, Bougea A, Assimakopoulos D. Laryngopharyngeal reflux disease in the Greek general population, prevalence and risk factors. BMC Ear Nose Throat Disord. 2015.
- Gill GA, Johnston N, Buda A, et al. Laryngeal epithelial defenses against laryngopharyngeal reflux: investigations of E-cadherin, carbonic anhydrase isoenzyme III, and pepsin. Ann Otol Rhinol Laryngol. 2005.
- Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG clinical guideline for the diagnosis and management of gastroesophageal reflux disease. Am J Gastroenterol. 2022.
- Khurmatullina AR, Andreev DN, Kucheryavyy YA, et al. The duration of proton pump inhibitor therapy and the risk of small intestinal bacterial overgrowth: a systematic review and meta-analysis. J Clin Med. 2025.
- Koufman JA. Low-acid diet for recalcitrant laryngopharyngeal reflux: therapeutic benefits and their implications. Ann Otol Rhinol Laryngol. 2011.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, July 31). Why acid reflux without heartburn affects the throat. Gut Pathways. https://gutpathways.com/articles/acid-reflux-without-heartburn/