Bloating starts within one hour of eating on quetiapine
For Manos, bloating within one hour of eating, three bowel movements a week, long-term quetiapine and oily drops in the toilet pointed to gut movement and fat digestion as connected parts of the assessment.
 Manos's casecase study
Manos's bloating within one hour of eating matched a fast nerve-driven response of the gut in a bowel that emptied about three times a week. Long-term quetiapine could also slow gut movement, while visible oily drops made his pancreatic digestive function worth testing. His adenoma history supported the recommendations for structured exercise and no processed meat at all.
Manos was 64 and had lived with type 1 diabetes since the age of 30. He usually woke up feeling comfortable. After breakfast or another meal, however, bloating and gas appeared within about 60 minutes. He also described constipation, periods of diarrhea with mucus and visible fat drops in the toilet. We therefore considered the gastrocolic reflex alongside retained stool, and requested fecal pancreatic elastase and calprotectin, among other tests. His history of a tubular adenoma with low-grade dysplasia added a second aim: reducing the changeable exposures linked with colorectal adenomas. This mix of gas and constipation, changing stool form and meal-related timing needed more than a single explanation.
Who is Manos and how did his symptoms appear?
Manos, age 64
Manos came to the practice where I work as a scientific collaborator after about five years of gut symptoms. He was 1.80 m tall and weighed 90 kg, a body mass index of 27.8 kg/m². His routine was sedentary, with no structured exercise, and he drank about six glasses of water a day. He had lived with type 1 diabetes since the age of 30 and used insulin. He also reported two vascular changes in his eyes that had been attributed to diabetes.
Comfortable on waking and clearly bloated within an hour
Most mornings, he woke up feeling well. Once he ate, bloating and gas began within roughly one hour. Bread, tomatoes and legumes were the foods most often linked with a flare. That precise onset carried more information than a general report of bloating after meals.
Three bowel movements a week with periods of diarrhea
Constipation and difficulty passing stool were the main pattern, with about three bowel movements a week. He also had periods of diarrhea with mucus. This alternation can occur with uneven propulsion, retained stool and large day-to-day changes in stool consistency.
Floating stool and oily drops
Some bowel movements floated and left oily drops in the toilet. Floating stool can result from trapped gas. Visible fat drops, however, raised the possibility of incomplete fat digestion or absorption, and gave us a specific reason to request fecal pancreatic elastase.
More than ten years of quetiapine
Manos had taken quetiapine for more than ten years. He had also taken low-dose aspirin for about six years and another long-term medicine for roughly ten. The combination of dry mouth and constipation fitted the antimuscarinic action of quetiapine's active metabolite, although dose and formulation affect the size of this effect.
Tubular adenoma with low-grade dysplasia
His most recent colonoscopy had found a tubular adenoma with low-grade dysplasia. Age 64, male sex and a body mass index of 27.8 kg/m² added relevant risk context. His sedentary routine was the clearest changeable factor in the history. His processed meat intake was unknown, so removing it was framed as a preventive step. Adenoma size, location, number and completeness of removal would give further information for surveillance planning.
Frequent sweets, soft drinks and dinner close to bedtime
In a typical week, he ate sweets four to five times and baked goods five times. He drank soft drinks four to five times and juice twice. Fish appeared up to once a week. On five days each week, he ate dinner at 21:00 and went to bed at 23:00. This pattern concentrated a large food load late in a mostly inactive day.
What did bloating within one hour of eating tell us?
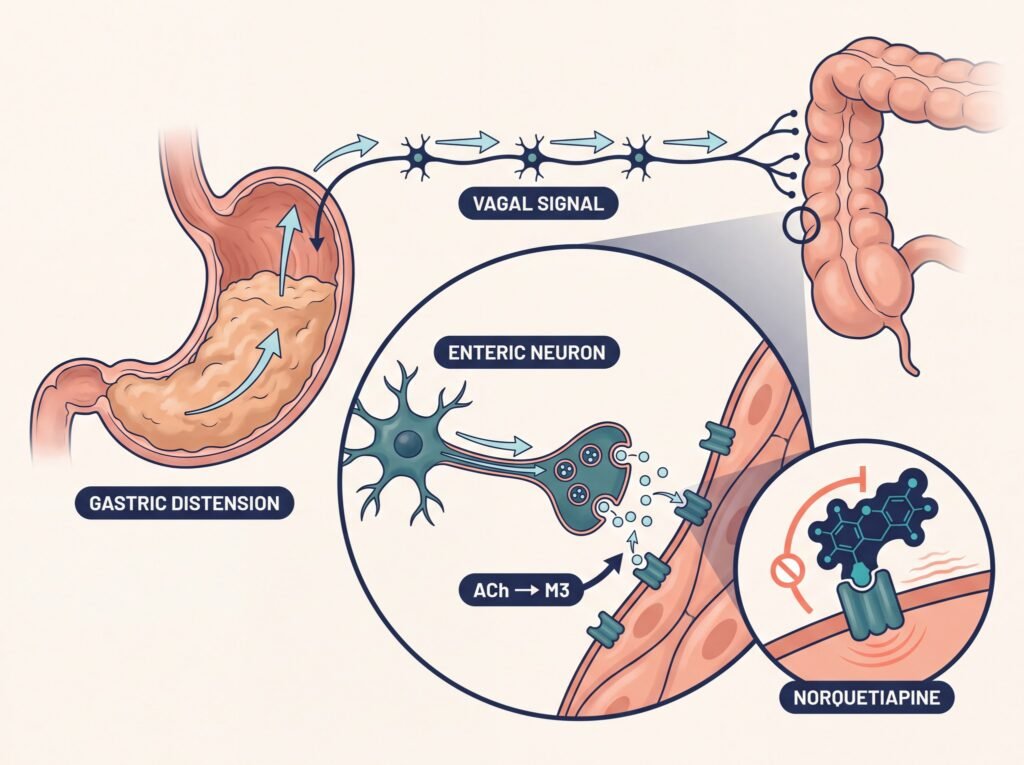
We started with the timing. When food enters and stretches the stomach, nerve pathways quickly tell the colon to move. This is the gastrocolic response, and it is driven by the vagus nerve, the gut's own nervous system and acetylcholine, the main signaling chemical that makes gut muscle contract through muscarinic receptors.1
What explains the first 60 minutes?
During the first hour, the new meal remains mostly in the stomach and the upper small intestine. Lower abdominal symptoms can arise as the gastrocolic and duodenocolic reflexes move gas and stool that are already in the colon. With about three bowel movements a week, Manos had more material waiting in his large bowel, so a normal reflex after a meal could feel much stronger, as stretching and gas. More causes are discussed in bloating and gas after eating.
- 1
The first minutes
Food stretches the stomach and switches on stretch sensors, vagus nerve signals and the gut's own nervous system.
- 2
Within the first half hour
Acetylcholine increases colon movement. At the same time, gas and stool already in the colon move into segments with a different sensitivity to stretch.
- 3
Toward the end of the hour
The early nerve response gradually settles. With slow transit, the stretch can last longer, because the bowel moves its contents on more slowly.
- 4
Later, after a fatty meal
A fatty meal can bring a second wave of gut activity, with hormones such as cholecystokinin and gastrin taking part.
How can bloating begin within one hour, before the meal has been fully digested?
In this type of presentation, symptoms can begin with the nerve signal created by food entering and stretching the stomach. Stomach stretch quickly increases colon activity and moves gas and contents that were already there. This explains bloating within one hour of eating. Fermentation of the new meal matters later, once undigested parts reach the colon.
How could type 1 diabetes contribute?
Thirty-four years of type 1 diabetes made the gut's automatic nerve control especially relevant. Long-term high blood sugar can affect nerve fibers, smooth muscle and the interstitial cells of Cajal, the pacemaker cells that coordinate the rhythm of gut contractions. Possible results include slower stomach emptying, slow transit, constipation or periods of diarrhea. Excessive sweating and dry mouth can also involve these automatic nerve pathways. In his history, dry mouth overlapped with quetiapine's action, so these signs stayed as context until the other measurements were reviewed.
How is quetiapine related to constipation?
Quetiapine is broken down to norquetiapine, an active metabolite that binds M1, M3 and M5 muscarinic receptors.2 M3 receptors sit in gut smooth muscle and in glands, so blocking them reduces contraction and secretion. Long-term use could therefore add to constipation, dry mouth and a stronger feeling of stretch after meals. Its action on histamine H1 and serotonin 5-HT2C receptors may also affect sleepiness, appetite and weight, with an indirect effect on physical activity.
Can quetiapine slow gut movement after ten years of use?
Norquetiapine's antimuscarinic action can reduce the contraction and secretion of gut smooth muscle for as long as treatment continues. The overall effect depends on dose, formulation, metabolism and other factors that shape gut movement. In a history that includes dry mouth and three bowel movements a week, the medicine has a clear biological route by which it could add to early bloating after meals.
What could oily stools and visible drops mean?
Fat digestion needs pancreatic lipase, colipase, bicarbonate, bile acids and a healthy absorbing surface in the small intestine. Cholecystokinin stimulates the release of pancreatic enzymes and the contraction of the gallbladder. Secretin increases bicarbonate, so that the duodenum reaches a suitable pH. Bile acids then form micelles, tiny structures that carry the products of fat digestion toward the cells of the gut lining. A problem at any of these steps can leave visible fat in the stool.

Lipase and colipase: breaking down fat
Pancreatic lipase breaks triglycerides into free fatty acids and monoglycerides. Colipase keeps the enzyme in contact with the fat droplet in the presence of bile salts.
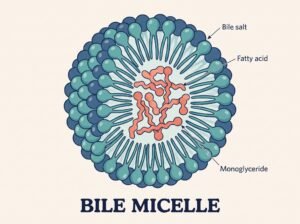
Bile salts and micelles: carrying fat through the gut
Bile salts break fat into small droplets and form micelles. These structures carry fats through the watery layer toward the surface of the gut lining cells.
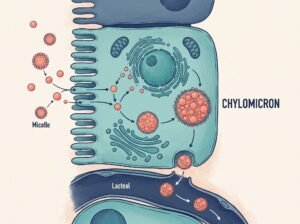
Absorption and chylomicrons: transport out of the gut
The cells of the gut lining rebuild triglycerides and package them into chylomicrons, fat-carrying particles that enter the lymphatic system.

Fecal pancreatic elastase: a marker of pancreatic output
Elastase stays relatively stable as it passes through the gut. A low concentration raises the possibility of reduced pancreatic enzyme output, although a watery stool can dilute the sample.
Why does fecal pancreatic elastase fit this history?
Fecal pancreatic elastase 1 is a non-invasive marker of the pancreas's digestive secretion and a practical way to check it. Visible fat drops, floating stool and long-standing type 1 diabetes made the test directly relevant to his history. A meta-analysis of 13 studies with 888 people found 94% sensitivity and 69% specificity at a cut-off of 200 μg/g, and 88% sensitivity and 82% specificity at 100 μg/g.3
Accuracy of fecal elastase for pancreatic insufficiency at two cut-offs (%)
de la Iglesia 2025, 13 studies with 888 people.3
In type 1 diabetes, however, a low fecal elastase does not always mean pancreatic insufficiency. In one study, low values matched a direct pancreatic test poorly, and in two thirds of people with fatty stools, the cause was outside the pancreas, probably bacterial overgrowth.4 A low value is therefore read together with stool consistency, symptoms and other pancreatic data.
How did we relate the adenoma to the rest of the history?
A tubular adenoma with low-grade dysplasia is already a change confined to the gut lining. Among Manos's changeable factors, his sedentary routine had the clearest direct link. A meta-analysis of 20 studies linked higher physical activity with a 16% lower relative risk of colon adenoma and a 30% lower relative risk of large or advanced adenoma.5
Where does processed meat fit?
His exact processed meat intake was unknown, while his red meat intake was reported as zero. Removing processed meat completely was therefore a preventive step. A meta-analysis found a relative risk of 1.29 for adenomas per 50 g of processed meat a day.6 N-nitroso compounds can damage DNA, while heme iron speeds up the oxidation of fats and the formation of reactive aldehydes. Cooking at high temperatures also produces heterocyclic amines and polycyclic aromatic hydrocarbons.
What do we expect the tests to show?
The testing plan addressed three questions. The first concerned fat digestion and the pancreas's digestive function. The second covered gut inflammation and infections behind the changing bowel pattern. The blood and urine tests covered metabolic, nutritional and blood factors that can affect gut movement, nerve function and overall heart and metabolic risk.
An indirect measure of the pancreas's digestive secretion. It fits the oily drops, floating stool and long history of type 1 diabetes. A formed sample reduces the effect of dilution.
Measures a white blood cell protein in stool and helps show whether the mucus and alternating bowel habits come with gut inflammation.
Finds genetic material from selected pathogens, in relation to the episodes of diarrhea and mucus. Calprotectin and elastase answer separate questions.
Adds information on pancreatic enzyme activity in the blood. Fecal elastase addresses the long-term digestive secretion more directly.
Show the metabolic conditions on the day of sampling. In type 1 diabetes, reading them needs an exact record of injected insulin and the timing of the latest dose.
Cover different parts of fat-related risk. Lp(a) is mostly genetic, while triglycerides respond more to recent diet and blood sugar control.
Link mineral status with muscle and nerve function. Alkaline phosphatase also gives information on the liver and bone.
Check nutrients involved in nerve function and one-carbon metabolism. Homocysteine is read together with B12, folate and kidney function.
The blood count checks for anemia, white blood cells and platelets. Fibrinogen and D-dimer add information on inflammation and clotting.
Prolactin may respond to medicines and hormones. IGF-1 gives a stable daily measure of the growth hormone axis.
Adds information on sugar, ketones, infection, blood and kidney findings in the urine, all relevant in long-standing diabetes.
How will we read fecal elastase?
A value above 200 μg/g supports normal pancreatic digestive secretion in most settings. Values from 100 to 200 μg/g fall into an intermediate range, while values below 100 μg/g raise the likelihood of substantial insufficiency. Stool consistency, type 1 diabetes and the wider pattern decide how the result is read.3, 4
What will calprotectin and the PCR panel add?
Calprotectin will show whether white blood cells are active in the gut lining, while the PCR panel will check selected infectious causes. These tests answer different questions from fecal elastase. Together, they cover the mucus, the periods of diarrhea and the possible problem with fat digestion, and each result will be matched to the mechanism its test measures. At the time of this case, the results were still pending.
What did we recommend, and how does each step relate to the history?
Why did we recommend a ten-minute gentle walk after main meals?
We recommended ten minutes of gentle walking after main meals. The timing mattered, because his bloating began in that same hour after eating. Gentle movement increases mechanical activity through the trunk, helps gas move through the bowel and shortens the time spent sitting after eating. For someone with type 1 diabetes, activity after meals also needs to fit the glucose and insulin monitoring routine already in use.
Why did we recommend structured exercise twice a week?
His sedentary routine related to two parts of his history. Regular movement supports gut movement and reduces the long stretches of inactivity that can worsen constipation. Higher physical activity has also been linked with a lower risk of colon adenomas, especially large or advanced ones.5 Two structured sessions a week gave a specific starting point from a sedentary baseline.
Why did we recommend removing processed meat?
This step related directly to the adenoma history. Nitrite curing, heme and high-temperature cooking can increase the gut lining's exposure to N-nitroso compounds, fat oxidation products and compounds that damage DNA. The published link concerns the amount eaten and relative risk, while Manos's exact weekly intake was unknown.6 His new diet plan therefore set processed meat at zero.
Every case is different, so Manos's plan describes his care and is not a plan for anyone else. Any change to his medicines or insulin stays with his doctors.
Why do we think these steps can help?
The three steps work over two time frames. The ten-minute walk sits inside the same hour in which Manos felt bloated. Structured exercise and removing processed meat have longer-term aims, related to constipation, a sedentary routine and the changeable factors linked with colorectal adenomas.6, 5
How do the tests relate to the steps?
Elastase, calprotectin and the PCR panel will show how much pancreatic secretion, gut inflammation and pathogens contribute to the changing bowel pattern. Walking and structured exercise have a clear timing and frequency, while removing processed meat has a clear measure of adherence. In our experience, specific steps work better when each one matches a documented part of the history.
What do we take from this case?
The exact timing pointed to a fast nerve and muscle response. Three bowel movements a week showed a low-frequency pattern that fits slower transit. Quetiapine added a medication route through norquetiapine and the M3 receptor. The oily drops justified testing the pancreas's digestive function, while the adenoma linked exercise and removing processed meat to a clear preventive aim. Related cases include Michael's IBS and diabetes case and the mechanisms considered in IBS after cholecystectomy.
Frequently asked questions
Stomach stretch quickly switches on the vagus nerve and the gut's own nerve circuits.1 The colon increases its activity and moves gas and contents that were already there. With slow transit, this movement can cause strong bloating.
Bloating after small meals can come from a sensitive gut, slow stomach emptying, constipation or the gut's reflex to eating, rather than the amount of food. Ongoing bloating is worth checking with a doctor.
Norquetiapine, an active metabolite of quetiapine, blocks muscarinic receptors.2 Blocking M3 receptors can reduce gut muscle contraction and secretion, a plausible route to constipation and dry mouth. Medicine changes are always made by the prescribing doctor.
Part of the fat in food may not have been digested or absorbed. Possible causes involve pancreatic enzymes, bile acids, absorption in the small intestine or a high fat intake. Fecal pancreatic elastase checks one specific part of that process.
A low value raises the possibility of reduced pancreatic digestive function. In type 1 diabetes, however, it can be low without it, and in one study most fatty stools had causes outside the pancreas.4 The value is read together with stool consistency, symptoms, nutrition and other pancreatic data.
References
6 studies
- Snape WJ Jr, Wright SH, Battle WM, Cohen S. The gastrocolic response: evidence for a neural mechanism. Gastroenterology. 1979.
- Almeida F, Albuquerque E, Murta I. Delirium induced by quetiapine and the potential role of norquetiapine. Front Neurosci. 2019.
- de la Iglesia D, Agudo-Castillo B, Galego-Fernández M, et al. Diagnostic accuracy of fecal elastase-1 test for pancreatic exocrine insufficiency: a systematic review and meta-analysis. United European Gastroenterol J. 2025.
- Hahn JU, Kerner W, Maisonneuve P, et al. Low fecal elastase 1 levels do not indicate exocrine pancreatic insufficiency in type-1 diabetes mellitus. Pancreas. 2008.
- Wolin KY, Yan Y, Colditz GA. Physical activity and risk of colon adenoma: a meta-analysis. Br J Cancer. 2011.
- Aune D, Chan DS, Vieira AR, et al. Red and processed meat intake and risk of colorectal adenomas: a systematic review and meta-analysis of epidemiological studies. Cancer Causes Control. 2013.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 9). Bloating starts within one hour of eating on quetiapine. Gut Pathways. https://gutpathways.com/case-studies/bloating-within-one-hour-of-eating/