Childhood antibiotics set the stage for C. diff at 19
Eliot's case of C. diff after antibiotics describes the relationship between recurrent ear infections, repeated antibiotic courses, the developing gut microbiome and what a molecular stool test found at 19.
 Eliot's casecase study
The relationship between antibiotics, the developing gut microbiome and Clostridioides difficile (C. diff) often appears in histories where treatment starts early and bowel symptoms persist. Eliot had diarrhea from birth. During his first year, he developed frequent infections, mainly ear infections, and received repeated antibiotic courses. At 19, he had 3 to 9 bowel movements a day, usually after meals, along with frequent belching.
During his assessment, we examined early-life antibiotic exposure, the childhood gut microbiome, the imbalance that can follow antibiotics and antibiotic-associated diarrhea. Molecular stool testing found genetic material from Clostridioides difficile, the toxin A gene (tcdA) and a broad absence of bacteria that produce butyrate. Colonization resistance and the tcdA and tcdB toxin genes gave further information about his persistent symptom.
Who is Eliot, and when did the diarrhea begin?
Nineteen years old with a low-normal body weight
Eliot came to the practice where I work as a scientific collaborator at 19. He was 1.78 m tall and weighed 63 kg, a body mass index of 19.9 kg/m². He exercised three times a week and drank about three glasses of water a day.
Frequent ear infections and several antibiotic courses
Soon after his birth, his mother developed mastitis and continued breastfeeding while taking an antibiotic. Eliot was breastfed for almost two years. During his first year, he had frequent infections, mainly ear infections, and received several antibiotic courses.
Diarrhea from birth
At 19, he had 3 to 9 bowel movements a day. Most were loose and often came right after eating. High-fat meals made the symptoms worse, while vegetables were better tolerated.
Frequent belching and difficult flights
Belching recurred throughout the day. Air travel came with severe nausea and exhaustion that lasted 3 to 5 days after a flight.
Daily dairy, sweets and wheat
His daily diet included dairy, sweets, wheat and coffee. Fish appeared up to once a week. Eliot ate throughout the day and often had his last snack around midnight.
How do childhood antibiotics relate to the molecular findings?
We started with how long the symptom had lasted. The diarrhea began at birth and was still there at 19. His first year included two separate exposures: his mother's antibiotic during breastfeeding and the repeated courses he received for infections and ear infections. We considered these exposures separately and focused on his own antibiotic treatment as the clearer factor linked with disruption of the microbiome.
Why we examined the childhood ear infections
In a study of children aged 1 to 5 years, antibiotic use in the previous 12 weeks was recorded in 54.4% of children with Clostridioides difficile infection and 19.4% of controls. Contact with a household member who had diarrhea and having a chronic condition were also more common among the children with infection.1 This finding explains why we asked for a detailed antibiotic history and included C. difficile in the molecular assessment.
Exposures in young children with and without C. difficile infection (%)
Weng 2019, 68 matched pairs of children aged 1 to 5 years.1
The timeline we wanted to examine
- BirthDiarrheaLoose stools from the start of life.
- First yearAntibioticsFrequent ear infections and several antibiotic courses.
- ChildhoodDiarrheaLoose stools continue through the years.
- Age 193 to 9 a dayMolecular testing finds C. difficile and the toxin A gene.
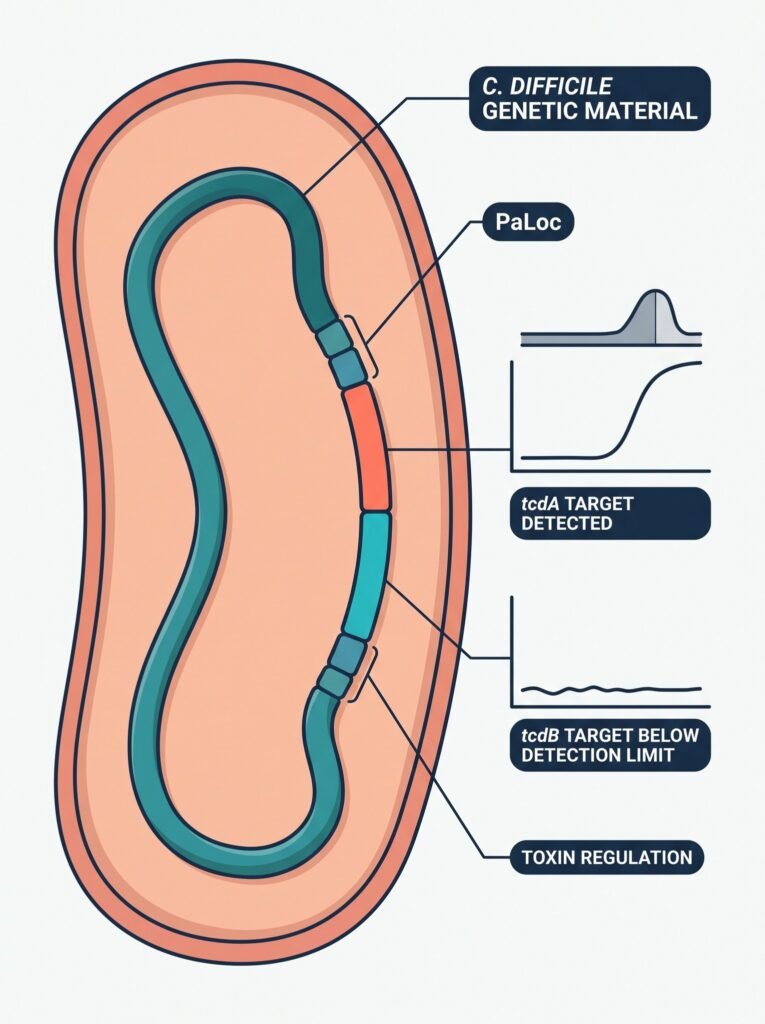
The toxin genes of Clostridioides difficile
What may persist after early-life exposure
In a randomized trial of 147 newborns, antibiotics shifted both the make-up of the gut bacteria and their antibiotic resistance genes (the resistome) right after treatment. Researchers recorded fewer Bifidobacterium and more Klebsiella and Enterococcus, and the differences were much smaller at 12 months.2 The study examined antibiotics given to newborns. Eliot had a single, later measurement at 19, so we used the study to explain a plausible biological mechanism. The effects of antibiotics on adults' guts are covered in IBS after antibiotics.
Which changes did we start before the results?
The first changes addressed meal timing, low water intake and foods that appeared every day. We also arranged a molecular stool test, so that the next steps could be chosen from measured findings.
Last meal before 7 pm
We recommended finishing all food before 7 pm on at least five days each week. This change addressed his snacks around midnight and lengthened the gap between his last meal and sleep.
Less dairy, wheat and sugar
We reduced dairy and sugar, removed fruit juice and chose two days each week with much less wheat. These foods appeared every day, so the change gave a practical way to see how his gut responded after meals.
Eight glasses of water, spaced away from meals
We raised the daily target from three to eight glasses of water. Drinks were placed between meals, about 60 minutes after eating, because of his frequent belching and his bowel movements after meals.
Specific preparation for flights
For the severe nausea and exhaustion that came with air travel, we recommended lighter food, good hydration and a small, low-fat meal before the flight.
Molecular stool testing
We requested quantitative molecular testing for Clostridioides difficile, the toxin A and B genes, Clostridium perfringens, Clostridium sporogenes, protective bacteria, opportunistic species and markers of digestion and gut defense.
What did the molecular test find, and how did we organize the plan?
The test gave three groups of findings. It found Clostridioides difficile and the toxin A gene, very few of the main butyrate producers and more Gram-negative and opportunistic bacteria.
Bacterial genetic material was found at a low level. We read it together with his 3 to 9 loose bowel movements a day.
PCR detected the gene linked with toxin A.
The two main toxin genes gave different molecular results.
Both additional Clostridium targets were below the detection limit of the method.
Akkermansia muciniphila, Bifidobacterium, Eubacterium rectale, Faecalibacterium prausnitzii, Roseburia hominis and Subdoligranulum variabile were all below the detection limit.
Anaerostipes caccae (7.6), Lactobacillus (6.5) and Ruminococcus bromii (4.8).
Bacteroides, Escherichia coli, Hafnia alvei, Veillonella and Ruminococcus gnavus were raised.
The value supported normal pancreatic digestive function.
The value was within the test's reference range.
How the findings relate to frequent bowel movements

What changes when colonization resistance falls?
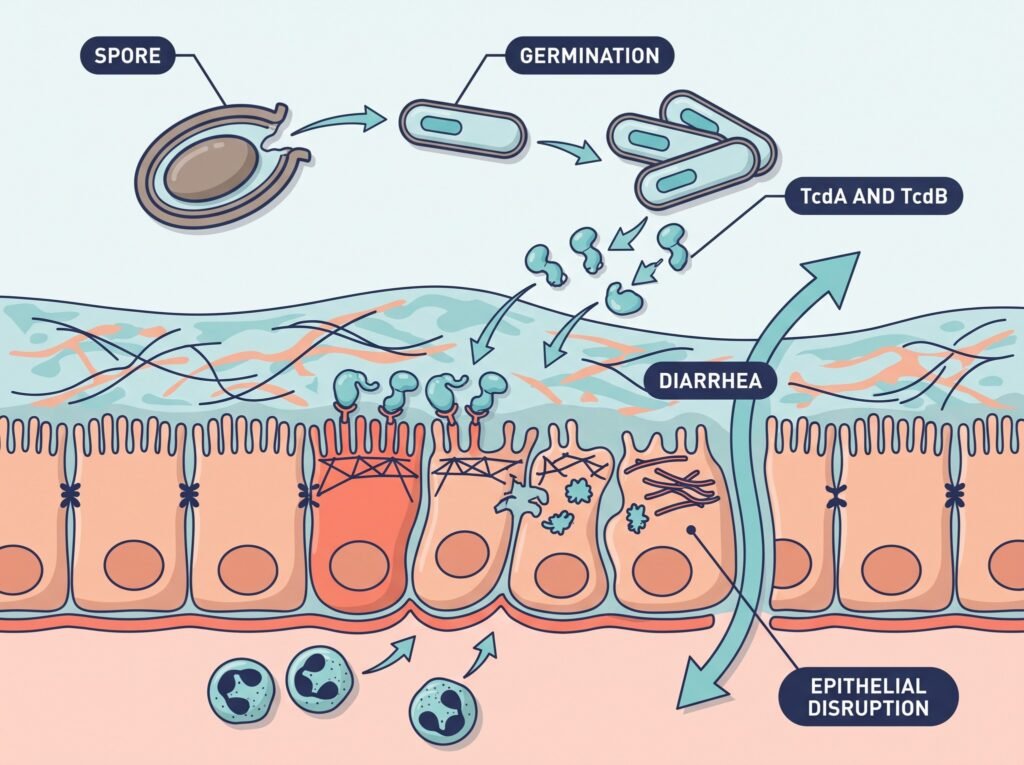
A diverse microbiome uses up nutrients, changes bile acids and makes compounds that hold back the germination and growth of Clostridioides difficile. When this community is disrupted, that protection, called colonization resistance, weakens and spore germination becomes easier.3 Many butyrate producers were below the detection limit, so we increased fermentable fiber gradually and added butyrate.
The main actions of Clostridioides difficile
Why we need the class and timing of each antibiotic
A review of 25 studies in children found that previous antibiotic use was linked with C. difficile infection (odds ratio 1.93), and so were acid-suppressing medicines (odds ratio 1.96).4 The risk is not the same for every antibiotic, and the active substances Eliot received in his first year were unknown. That is why we ask for the active substance and timing of every antibiotic in a child's medication history.
The active substances and why we chose them
| Intervention | Finding and reason |
|---|---|
| Rifaximin, a short course decided by his doctor | For C. difficile, the toxin A gene and the raised opportunistic bacteria. An antimicrobial that acts inside the gut, with very little absorption into the body. |
| A probiotic with twelve strains | For the Bifidobacterium below detection and the low Lactobacillus. The strains included Lactobacillus rhamnosus, acidophilus, casei, plantarum, salivarius, paracasei and bulgaricus, Bifidobacterium bifidum, longum, lactis and breve, and Streptococcus thermophilus. |
| L-glutamine and a blend that supports the gut lining | For the chronic diarrhea after meals and the wide imbalance. The blend combined L-glutamine with N-acetyl-glucosamine, citrus pectin, deglycyrrhizinated licorice, aloe, slippery elm, mucin, marshmallow, chamomile, okra, cat's claw, MSM, quercetin, prune, zinc and L-carnosine. |
| Sodium and potassium butyrate | For the many butyrate producers below detection. Butyrate is a short-chain fatty acid and a main source of energy for colon cells. |
| Vitamin C, magnesium and vitamin B6 | Linked in his plan with his raised lipoprotein(a) and raised iron, with iron rechecked after a month. |
| L-lysine with zinc and plant extracts | Linked in his plan with his raised lipoprotein(a) and his diarrhea. |
| Methylcobalamin and methylfolate | For his homocysteine of 13.1 µmol/L and his beta-thalassemia minor. Both vitamins take part in homocysteine metabolism. |
Diet for two months
We removed dairy, sugar, sweets, fruit juice and sugar-sweetened soft drinks for two months, and reduced wheat substantially. The last meal ended at least four hours before sleep, and drinks came 45 minutes after meals. After the first week of the antimicrobial, we added a small daily amount of cucumber and carrot. We then increased sources of soluble fiber step by step, including oats, barley, legumes, strawberries and apple.
Exercise with a controlled duration
The weekly plan included walking or running at least 4 km four times a week. We added strength training two to three times a week, with a five-minute warm-up, two sets of 10 to 12 repetitions for the main muscle groups and 2 to 3 minutes of rest between sets. We also added yoga twice a week. Aerobic sessions stayed moderate in length because of his frequent bowel movements.
Sleep before midnight
The target was at least 7.5 hours of sleep with bedtime before midnight. We chose two to three days each week with an earlier bedtime and less artificial light in the evening, and the last meal ended at least four hours before sleep.
Every case is different, so Eliot's plan describes his care and is not a plan for anyone else. Antibiotics for C. difficile are always decided by the treating doctor.
When does C. difficile testing make sense in a child with persistent diarrhea and repeated antibiotics?
From the age of 2, prolonged or worsening diarrhea together with recent antibiotics makes testing for Clostridioides difficile more useful. Carrying it without symptoms is very common in infants, so age changes how a result is read. Testing is most useful on an unformed stool sample, read together with bowel frequency, toxin genes and other possible causes.5
What does it mean when PCR finds C. difficile and the toxin A gene, but the toxin B gene is below the detection limit?
The result describes a specific molecular profile. PCR finds genes and shows the potential to make toxin. Active effects in the gut are judged together with bowel movements, stool consistency and the rest of the microbiome test. The toxin genes tcdA and tcdB sit in a region called the PaLoc, together with regulatory genes, and variants with different gene patterns have been described.6
What did we know before and after molecular testing?
The comparison shows what we knew beforehand and what molecular testing added. We organized the plan after receiving these findings.
What does Eliot's case show?
Eliot's diarrhea began at birth, and repeated antibiotic courses started during his first year. At 19, molecular testing found Clostridioides difficile, the toxin A gene and a broad lack of protective bacteria. These findings guided our choice of an antimicrobial, butyrate, probiotic strains and a gradual increase in fiber.
Age determines when testing has value
In the first 12 months of life, carrying C. difficile without symptoms is common, so testing is less specific. From the age of 2, prolonged diarrhea together with antibiotic exposure is a clearer reason to test.5 In Eliot's case, diarrhea that lasted through childhood supported an earlier investigation. At 19, we read the measurement together with his history, the toxin genes and his microbiome profile.
Frequently asked questions
From the age of 2, testing has more diagnostic value when prolonged or worsening diarrhea comes with a relevant exposure, such as recent antibiotic use. Carrying it without symptoms is common in the first 12 months, so age changes how a result is read.5
The tcdA and tcdB targets are the genes for the two main toxins of Clostridioides difficile. Finding them shows the genetic capacity to make toxin. The molecular result is read together with diarrhea, stool consistency and the other findings.6
Antibiotics can reduce diversity and change the balance of protective and opportunistic bacteria. In a randomized trial of 147 newborns, researchers recorded immediate changes in the make-up of the gut bacteria and their resistance genes, with smaller differences at 12 months.2
Using antibiotics only when they are needed is the most important step, together with good hand hygiene. A diverse diet with enough fiber supports the gut bacteria that protect against C. diff.3 Any new diarrhea during or after antibiotics should be reported to a doctor.
References
6 studies
- Weng MK, Adkins SH, Bamberg W, et al. Risk factors for community-associated Clostridioides difficile infection in young children. Epidemiol Infect. 2019.
- Reyman M, van Houten MA, Watson RL, et al. Effects of early-life antibiotics on the developing infant gut microbiome and resistome: a randomized trial. Nat Commun. 2022.
- Seekatz AM, Young VB. Clostridium difficile and the microbiota. J Clin Invest. 2014.
- Dong N, Li ZR, Qin P, et al. Risk factors for Clostridioides difficile infection in children: a systematic review and meta-analysis. J Hosp Infect. 2022.
- McDonald LC, Gerding DN, Johnson S, et al. Clinical practice guidelines for Clostridium difficile infection in adults and children: 2017 update by IDSA and SHEA. Clin Infect Dis. 2018.
- Monot M, Eckert C, Lemire A, et al. Clostridium difficile: new insights into the evolution of the pathogenicity locus. Sci Rep. 2015.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 3). Childhood antibiotics set the stage for C. diff at 19. Gut Pathways. https://gutpathways.com/case-studies/childhood-antibiotics-chronic-diarrhea-clostridioides-difficile/