SIBO can look exactly like celiac disease on a biopsy
A 26-year-old man had a biopsy that pointed to celiac disease and little relief from a gluten-free diet. His case shows how SIBO and celiac disease can look alike, because bacterial overgrowth in the small intestine can produce the same picture in the gut lining.
 Nick's casecase study
The hallmark of celiac disease is the infiltration of lymphocytes into the lining of the small intestine. This leads to villous atrophy, which can be seen and measured with an endoscopy and biopsy. The symptoms of celiac disease come from this exact infiltration. Nevertheless, the same lymphocyte infiltration can appear for other reasons, most notably chronic infections and bacterial overgrowth. In fact, even an overgrowth of the gut's own bacteria can break immune tolerance and copy the mechanism that celiac disease uses to cause symptoms.
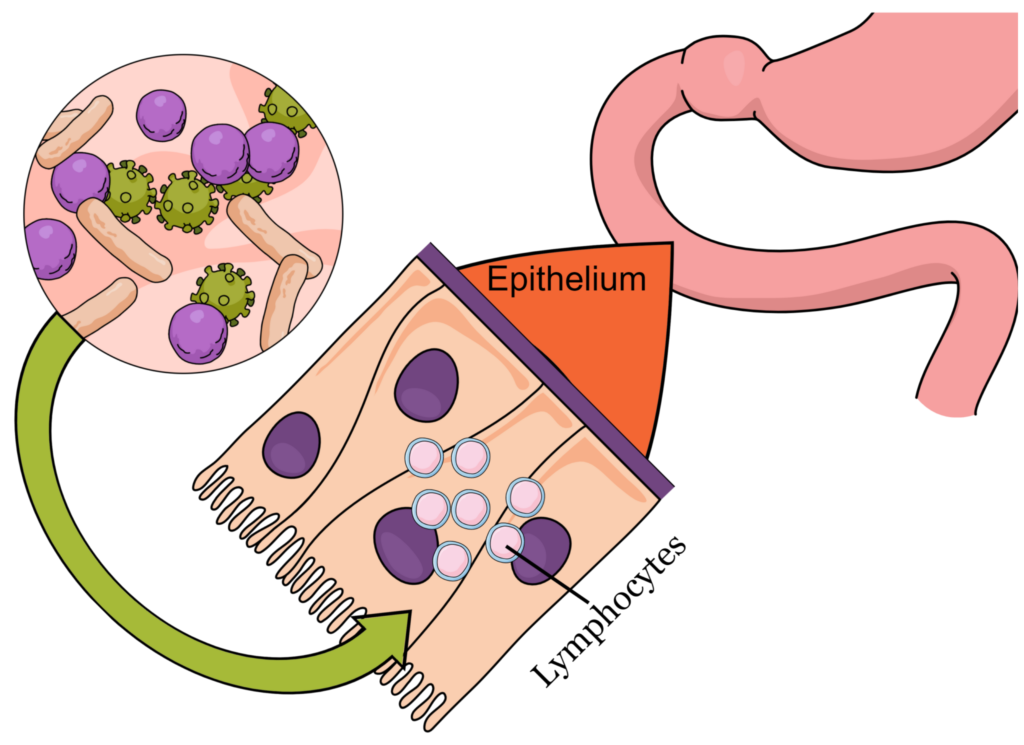
In a study of duodenal biopsies, the total share of intraepithelial lymphocytes was similar in celiac disease and SIBO. More importantly, one specific group, the gamma delta lymphocytes, was raised as much in SIBO as in celiac disease.1 An increase of these cells is therefore typical of celiac disease, but not specific to it.
Intraepithelial lymphocytes in duodenal biopsies (%)
Remes-Troche 2007, 12 people with celiac disease, 8 with SIBO and 10 with IBS with diarrhea.1
Who is Nick, and why did a gluten-free diet help so little?
Surgeries, infections and antibiotics from childhood
Nick is a 26-year-old marketing adviser who came to the practice where I work as a scientific collaborator. He was born by caesarean section, like his younger brother. At the age of five, he had his appendix and his tonsils removed within seven months. His mother reports that since then he had at least one severe infection every year, either gastroenteritis or bronchitis, and he needed at least one antibiotic course a year.
A seafood meal, then diarrhea and weight loss
Three years earlier, his gut symptoms appeared after a large seafood meal. The next morning he woke up with a very upset stomach, which only settled after he vomited five times. From then on, he had at least one episode of diarrhea a week and could not tolerate foods with wheat. Six months later he had lost 11 kg, and bloating and gas were a daily problem.
He had seen several specialists and had two colonoscopies and two gastroscopies. His blood tests and duodenal biopsies pointed to celiac disease, so he had followed a strict gluten-free diet for two and a half years. Nevertheless, he improved only slightly, the diarrhea did not stop, and he had gained back only 2 kg. Two years earlier he was also diagnosed with Hashimoto's thyroiditis. The only period he felt better was two months after a course of rifaximin.
- Age 5Two surgeriesAppendix and tonsils removed within seven months.
- Every yearInfectionsGastroenteritis or bronchitis, with at least one antibiotic course.
- 3 years agoSeafood mealVomiting, then weekly diarrhea and poor tolerance of wheat.
- 6 months later−11 kgDaily bloating and gas.
- 2.5 yearsGluten-freeOnly slight improvement and 2 kg regained.
- TriggerTonsillectomy and appendectomyEffect
Lower production of secretory IgA.
- TriggerEating all dayEffect
The cleaning wave of the small intestine is blocked.
- TriggerAntibioticsEffect
The diversity of the gut flora falls.
- TriggerExtreme SIBOEffect
Lymphocytes infiltrate the gut lining.
Each trigger removes one defence of the small intestine.
Which clues pointed away from celiac disease?
Main data mined
- Episodes of diarrhea
Diarrhea can come from long-standing bacterial overgrowth in the small intestine.
- Weight loss
Overgrown bacteria disturb how food is prepared in the gut, so undigested particles cannot be absorbed properly.
- Frequent infections
Bacterial overgrowth changes the environment of the gut and makes it easier for harmful bacteria to settle and cause infections.
- Bloating and gas
Too much gas comes from strong fermentation of starch and fibre early in digestion.
Useful data mined
Main clues shape the tests, and useful clues help us read the results.
What did his tests show?
Nick had the highest SIBO breath test values I had seen. Secretory IgA deficiency was clear, probably made worse by the early removal of his appendix and tonsils. In addition, his habit of eating all day kept feeding the bacteria of his small intestine and never left time for the migrating motor complex, the cleaning wave of the gut, to clear the area. Low IgA in the blood could also explain the repeated infections and the many antibiotics he had taken.
Pseudomonas aeruginosa was also found. Bacteria of this kind, taken from the small intestine of people with celiac disease, showed elastase activity and broke gluten down into peptides that passed the gut barrier more easily. These peptides activated gluten-reactive immune cells from people with celiac disease.2 The proteases of such bacteria can also switch on inflammation in the gut by themselves, without gluten.3
Pseudomonas aeruginosa
A bacterium of the upper small intestine with elastase activity that breaks down gluten.

Low secretory IgA
A strong tendency to infections and weaker immune defence of the gut lining.
SIBO
Extreme fermentation of sugars and starch, poorer absorption and a leakier gut.

No beneficial bacteria
There was no sign of Lactobacilli or Bifidobacteria in the stool, after many antibiotics.
My biopsy shows raised intraepithelial lymphocytes, but I don't feel better on a gluten-free diet. Could it be something else?
It could. Raised intraepithelial lymphocytes are typical of celiac disease, but they also appear in bacterial overgrowth, infections and with some medicines such as NSAIDs.1 Celiac genetics (HLA DQ2 and DQ8), antibody levels and a breath test for SIBO help separate the causes. Your gastroenterologist decides which tests fit.
How was Nick treated?
The remission Nick had after rifaximin was not accidental. His SIBO values were very high, and in such cases one course is usually not enough, so his plan included repeated courses over three months, decided by his doctor. At the same time, the plan aimed to raise secretory IgA, with butyrate, Saccharomyces boulardii and beta-glucans, and to rebuild certain helpful groups such as Lactobacilli. Common probiotics usually do not help, and in fact they may make symptoms worse by adding to the overgrowth. Changes in diet and daily habits matter a lot, because they allow faster recovery.
A strict 90-day plan
Nick's plan lasted 90 days and was extremely strict, but he managed to follow it. Sticking to the diet and the daily routine is very important, because this kind of IBS starts high in the small intestine, and symptoms can come back very easily. Every case is different, so Nick's plan describes his care and is not a plan for anyone else.
What does Nick's case show about SIBO and celiac disease?
Frequently asked questions
Yes. SIBO can raise intraepithelial lymphocytes, including the gamma delta group that is typical of celiac disease, and cause mild villous atrophy.1 The symptoms overlap too, with diarrhea, bloating and weight loss.
They are immune cells inside the lining of the small intestine. A raised count is typical of celiac disease, but it also appears in SIBO, infections and with some medicines, so it needs to be read with genetics, antibodies and other tests.1
Yes. SIBO is a common reason why some people with celiac disease keep having symptoms on a gluten-free diet. Separating the two needs both celiac tests and a SIBO breath test.
In laboratory and mouse studies, Pseudomonas aeruginosa from people with celiac disease broke gluten into peptides that crossed the gut barrier more easily and activated gluten-reactive immune cells.2
References
3 studies
- Remes-Troche JM, Adames K, Castillo-Rodal AI, et al. Intraepithelial gammadelta+ lymphocytes: a comparative study between celiac disease, small intestinal bacterial overgrowth, and irritable bowel syndrome. J Clin Gastroenterol. 2007.
- Caminero A, Galipeau HJ, McCarville JL, et al. Duodenal bacteria from patients with celiac disease and healthy subjects distinctly affect gluten breakdown and immunogenicity. Gastroenterology. 2016.
- Caminero A, McCarville JL, Galipeau HJ, et al. Duodenal bacterial proteolytic activity determines sensitivity to dietary antigen through protease-activated receptor-2. Nat Commun. 2019.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2022, September 22). SIBO can look exactly like celiac disease on a biopsy. Gut Pathways. https://gutpathways.com/case-studies/celiac-mimicking-sibo/