Why did bloating stay after two rounds of antibiotics?
Two antibiotic courses later, his stomach still looked pregnant by dinner. Marios's case of bloating that won't go away shows what a molecular stool panel found after two clean scopes, and how his plan followed those findings.
 Marios's casecase study
Who is Marios, and what had he already tried?
Marios, 28
Marios is 28 and works a desk job in Athens, the kind where lunch happens in ten minutes at the keyboard. Bread and cheese most days, a coffee to get through the afternoon, and a vape he reaches for between meetings. His bloating and constipation started about a year and a half before he came to the practice where I work as a scientific collaborator, and by then he had already been through two rounds of a standard gastroenterology workup.
Two antibiotic rounds, same bloating
A gastroenterologist put him on two probiotic and fiber products, which helped for a while and then stopped working the moment he came off them. A breath test came back positive for small intestinal bacterial overgrowth (SIBO), so he did a course of amoxicillin and metronidazole with a probiotic. When the bloating returned, he repeated a similar antibiotic and probiotic combination a second time. Both rounds eased things for a while, and both times the bloating that won't go away came right back. Along the way, he also mentioned frequent migraines and cold sores that flared whenever he was under pressure at work.
Clean scopes, one exception
A gastroscopy in June 2018 found nothing beyond Helicobacter pylori, and a colonoscopy that September came back completely clean. Every visit ended the same way, with the same sentence: your tests are clean, it's probably stress.
Why did we decide to look deeper?
- 1
About 18 months before
Bloating and constipation begin and slowly get worse.
- 2
Soon after
Two probiotic and fiber products help, then symptoms return after stopping.
- 3
A few months later
A gastroscopy shows Helicobacter pylori only, and a SIBO breath test is positive.
- 4
Right after that
Amoxicillin and metronidazole with a probiotic. Symptoms ease, but the bloating persists.
- 5
After the relapse
A different probiotic with a repeat antibiotic combination, and the same pattern.
- 6
Around the same time
A colonoscopy comes back completely clean.
- 7
First visit with us
A full history, then a molecular stool panel and immune and metabolic markers.
The pattern is what caught our attention, more than any single symptom. Marios had already done exactly what a standard workup asks for, twice, and the bloating kept coming back on schedule.
What the standard workup left open
A clean gastroscopy and a clean colonoscopy rule out ulcers, visible inflammation and structural disease. They say nothing, however, about bacterial balance, enzyme activity or immune markers of the gut lining, such as secretory IgA.2 In our experience, a third round of the same antibiotics rarely changes a pattern like this, since it only resets the clock on the same relapse.
Relapse after treatment is common. In one study, people with SIBO who were successfully treated with antibiotics tested positive again in 12.6% of cases after three months, 27.5% after six months and 43.7% after nine months. Older age, a past appendectomy and long-term PPI use made a relapse more likely.1
How SIBO comes back after one course of antibiotics
Lauritano 2008, 80 people with a negative breath test after treatment, retested over nine months.1
What we decided to check instead
After two rounds of antibiotics gave the same result, we ordered a molecular stool panel to see which species were overgrown, along with secretory IgA, complement C3, homocysteine, folate and fecal beta-glucuronidase. Every one of these markers was new territory, absent from his previous workup.
What finally explained the bloating that won't go away?
The results came back a few weeks later and pointed, for the first time, to specific, measurable targets.
- Enterococcus faecium (stool molecular panel)High
Overgrown. This species has been linked with gut infections, prostatitis and septic arthritis, although certain strains also have a normal role in nutrient absorption. It had never been measured in the earlier workup.
- Secretory IgAVery low
Secretory IgA is the first line of antibody defense on every mucosal surface, in the gut, the airways and beyond.2 A low reading points to weaker mucosal defense and a higher risk of infections, both in the gut and elsewhere.
- Bacillus species (stool molecular panel)High
Overgrown. These strains are sensitive to plant tannins, such as those in green tea, and to berberine. They can reduce nitrates to nitrites, so processed meats with sodium nitrite tend to feed this overgrowth.
- Fecal beta-glucuronidaseHigh
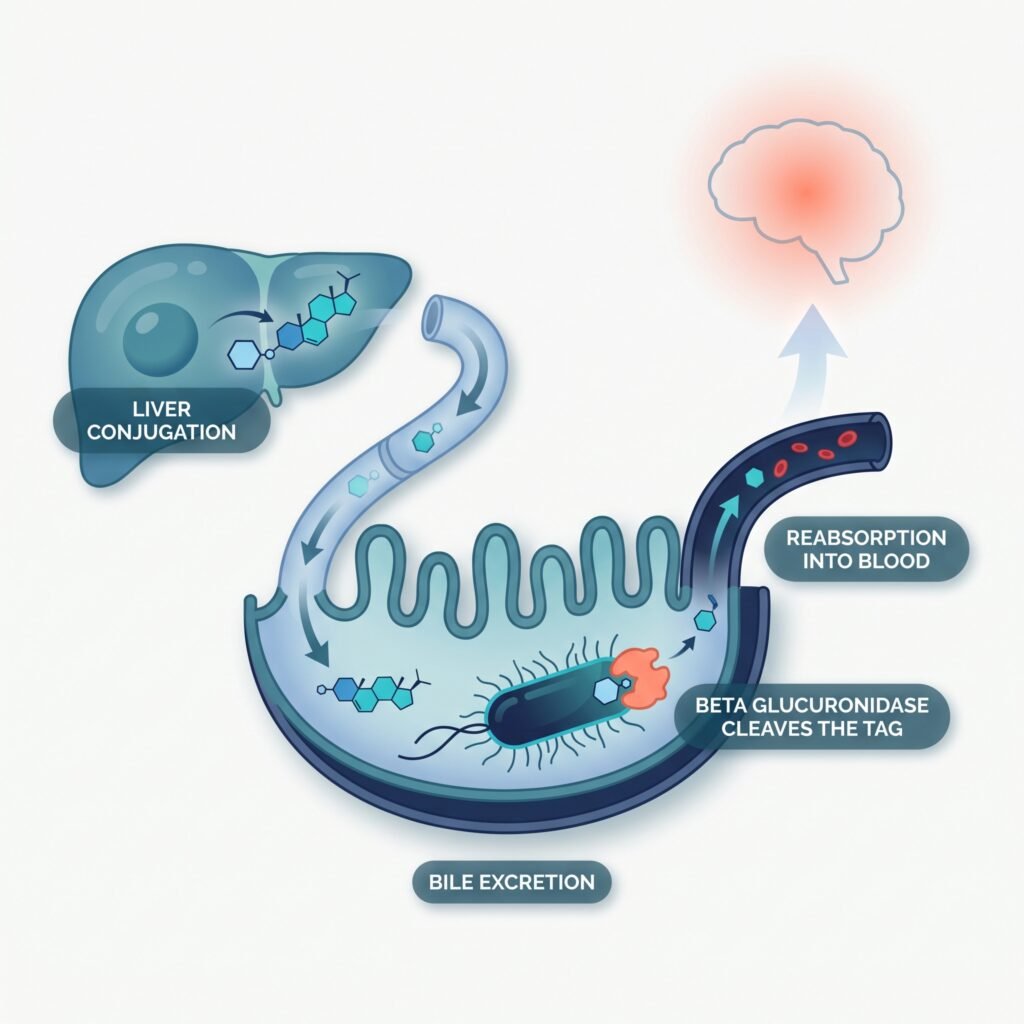
This enzyme frees hormones and other compounds that the liver had already tagged for removal, so they return to circulation. It had never been measured before.
- HomocysteineHigh
An independent cardiovascular risk marker, flagged for the treating physician to monitor alongside folate replacement.
- FolateVery low
Low folate goes with the high homocysteine and needs replacing directly.
- Complement C3Low
C3 supports the immune response to infections and toxins, and low levels can leave the door open to more frequent infections.
- Repeat gastroscopy for H. pyloriNot yet measured
Recommended as a next step, given the original positive result and its link with migraine.3
The dot shows where each result fell against the lab's reference range. The repeat gastroscopy had not been done yet.
If my colonoscopy and gastroscopy were clean, how can something still be wrong in my gut?
Colonoscopy and gastroscopy are built to find structural problems: ulcers, polyps, visible inflammation and tumors. Bacterial balance, enzyme activity and immune markers such as secretory IgA show up on a stool or blood panel instead, and a gut can look completely normal on camera while carrying exactly that kind of imbalance. That gap is why a molecular stool panel made sense here even after two clean scopes, and it is worth asking about whenever the same clean result keeps repeating without an explanation for the symptoms.
The intervention plan
The plan builds directly on these findings. It aims to bring down the overgrown species, replace the missing folate while the treating physician tracks homocysteine, normalize the probiotic culture and lower beta-glucuronidase activity, since this enzyme is central to how hormones and toxins recirculate through the body. In one study, gut bacteria and beta-glucuronidase activity were linked with the levels of estrogens in stool and urine.4
The treatment
| Intervention | For which finding, and why |
|---|---|
| Berberine | For the Bacillus overgrowth. This genus is sensitive to berberine, which helps bring the population back down. |
| A probiotic formula | For the very low secretory IgA and the wider imbalance. It aims to normalize the probiotic culture and support mucosal defense, the same defense that matters for his frequent cold sores. |
| Methyl B12 and methylfolate | For the low folate and high homocysteine, replacing what is missing while the treating physician monitors the homocysteine trend. |
| Calcium D-glucarate | For the high fecal beta-glucuronidase, to reduce the enzyme's activity so that fewer tagged compounds return to circulation. |
| 5-HTP | Supports the serotonin pathway, one of the goals alongside the antimicrobial and immune work. |
| Gut lining support | General support for the intestinal lining while the rest of the protocol takes effect. |
We explained the results to Marios in the order they mattered to him: first the overgrowth driving the bloating, then the weak mucosal defense that may play into how often his cold sores flare, and then the beta-glucuronidase finding as a possible piece of the migraine picture that deserves watching over time. Stress is a well-known trigger for cold sore flares in its own right, and in laboratory studies stress hormones reactivated herpes viruses in nerve cells.5 For that reason, supporting mucosal immunity works alongside stress management as one part of the picture.
Every case is different, so Marios's plan describes his care and is not a plan for anyone else. Supplements, antibiotics and any repeat treatment are decided with the treating physician.
What changed the picture?
Why is this approach likely to work?
This case is moving in the right direction so far, because the plan follows the findings of the stool and immune panel. Overgrowth, weak mucosal defense and an overactive enzyme are three separate, addressable targets that together explain the pattern.
What this means in practice
A clean result on two scopes is reassuring, but it answers a different question. When bloating keeps returning after antibiotics, probiotics and clean scans, tests of gut bacteria, enzymes and gut immunity can show what the scopes cannot. Ways to rebuild the gut's defense are discussed in how to increase secretory IgA naturally, and the common causes in abdominal bloating causes.
Frequently asked questions
Antibiotics bring down the bacterial overgrowth itself. What let it build up in the first place, whether that is gut movement, diet or an unmeasured immune or enzyme factor, usually needs its own look to hold the improvement. In one study, 43.7% of people tested positive again within nine months of a successful course.1 The treating physician decides whether repeat antibiotics, a different regimen or further testing fits a given case.
Yes, this is common. Colonoscopy and gastroscopy are designed to detect structural problems, such as ulcers or visible inflammation. Bacterial composition, enzyme activity and immune markers need their own tests, so a clean result on both still leaves room for a testable functional cause of bloating.
Common causes include bacterial overgrowth, an imbalance of gut bacteria, slow gut movement, food intolerances and constipation. Ongoing bloating with weight loss, bleeding or a swollen abdomen needs prompt medical review. More causes are covered in bloating and gas after eating.
Research links gut bacteria and infections such as Helicobacter pylori with migraine, likely through inflammatory pathways. A large review found H. pylori infection more often in people with migraine (odds ratio 2.80).3 This remains an active area of research, and any migraine treatment decision stays with the treating physician.
References
5 studies
- Lauritano EC, Gabrielli M, Scarpellini E, et al. Small intestinal bacterial overgrowth recurrence after antibiotic therapy. Am J Gastroenterol. 2008.
- Mantis NJ, Rol N, Corthésy B. Secretory IgA's complex roles in immunity and mucosal homeostasis in the gut. Mucosal Immunol. 2011.
- Bawand R, Ghiasian M, Samadyan M, Qaderi S. Association of Helicobacter pylori with migraine headaches and the effects of this infection and its eradication on the migraine characteristics in adults: a comprehensive systematic review and meta-analysis. Helicobacter. 2023.
- Flores R, Shi J, Fuhrman B, et al. Fecal microbial determinants of fecal and systemic estrogens and estrogen metabolites: a cross-sectional study. J Transl Med. 2012.
- Goswami P, Ives AM, Abbott ARN, Bertke AS. Stress hormones epinephrine and corticosterone selectively reactivate HSV-1 and HSV-2 in sympathetic and sensory neurons. Viruses. 2022.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, August 27). Why did bloating stay after two rounds of antibiotics?. Gut Pathways. https://gutpathways.com/case-studies/bloating-that-wont-go-away/