Blastocystis settled in the gut after a trip to Thailand
Blastocystis hominis after travel, in a gut used to only a few foods. Andreas's case shows how the organism settled into a gut with little variety, and how diet and targeted treatment brought him relief.
 Andreas's casecase study
Andreas, 31, came to the practice where I work as a scientific collaborator after more than a year of episodes of abdominal cramps, burning and discomfort that persisted despite the changes he had already tried on his own. A few months earlier, he had travelled to Thailand, and the first symptoms appeared soon after he returned. His diet kept the same few foods on repeat, week after week, which meant low fiber diversity and a narrow range of food sources for his gut microbiome.
In this case, we explain how Blastocystis hominis after travel settled into a gut with poor microbiome diversity, how gut dysbiosis connected to the persistent symptoms that followed, and how a change in diet combined with targeted treatment gradually led to meaningful improvement.
Who is Andreas, and what had he been through before he came to us?
A 31-year-old with a history of frequent colds
Andreas is 31 years old, 190 cm tall and weighs 62 kg, a body mass index of 17.2, below the normal range. He had long described a tendency to catch colds easily and feel pressure in his ears, a pattern of mild immune sensitivity that existed long before any gut symptom appeared.
The trip to Thailand and the first episode
A few months after a trip to Thailand, Andreas felt intense pain in his upper abdomen during exercise. He was given esomeprazole for gastritis, with temporary relief. A stool test that followed showed Blastocystis hominis, and treatment with fluconazole and probiotics helped in part, but the cramps and discomfort persisted.
A diet with very little variety
His weekly diet kept nearly the same choices on a cycle: grains seven times a week, rice six times, chicken seven times, eggs every day, fish five times, no legumes and very little variety of vegetables. The result was a diet with low fiber diversity, a pattern linked with a poorer gut microbiome.2
Over a year of cramps, with calm stretches in between
A cycle of flares and calm periods followed for more than a year. Two endoscopies showed reactive gastropathy and reflux-type esophagitis, but the biopsies showed no sign of celiac disease or H. pylori. During the same period, patchy hair loss appeared on his scalp and beard, along with mouth ulcers and a skin rash, signs that his body was reacting in several places at once.
Blastocystis hominis after travel: why did we suspect a link with diet?
We read Andreas's history with two questions in mind. First, why did the symptoms start soon after he returned from Thailand? Second, why did a diet so consistent and seemingly healthy still leave his gut vulnerable?
- 1
May 2024
Trip to Thailand, and a few months later, the first episode of intense upper abdominal pain during exercise.
- 2
September 2024
First endoscopy with biopsies: no H. pylori, normal lining, no sign of celiac disease.
- 3
January 2025
A new flare with headaches, which improved with stricter limits on acidic and spicy foods.
- 4
July 2025
Second endoscopy: reactive gastropathy and reflux-type esophagitis, H. pylori negative again.
- 5
September 2025
The cramps return, easing after bowel movements and worsening with stress, which led to the molecular stool test.
The trip as a starting point
In our experience, people often develop persistent gut symptoms months after travel to countries in Southeast Asia, even when the first episode seems to have passed. The timing in Andreas's case matched this pattern, so we considered his trip a very likely trigger.
How quickly travellers' diarrhea appears in Thailand
Sharma 2020, 349 adult foreign travellers, cumulative share with travellers' diarrhea.3
In this study, about one in three foreign travellers to Thailand developed travellers' diarrhea within the first month of their stay.3 Symptoms can also last long after the trip. In returning travellers with persistent gut symptoms, the most common protozoan found was Blastocystis hominis, and symptoms had usually lasted about six months before people sought care.1
Protozoa found in returning travellers with persistent gut symptoms
Gefen-Halevi 2022, share of samples positive for each protozoan.1
From our experience
We often see people develop symptoms after travel to these countries, especially when they have recently taken antibiotics or already have a low-quality microbiome from diet or medication. Travel is often only the trigger that reveals a gut that was already vulnerable, alongside other contributing factors.
How three factors combined

Diet, years before
Chronically limited food variety, with low fiber intake from different sources.2
Fewer species, less defense
A gut community with few species, and acid-suppressing medication on and off, offer less resistance to a new colonizer.4

Exposure during travel
The trip to Thailand became the trigger that revealed the weakness.1
No single one of the three layers explains the full picture on its own. Together, though, they form a consistent chain, from long-term dietary monotony to the trip that became the trigger.
My stool test came back positive for Blastocystis hominis. Does that definitely mean it is causing all my symptoms, or could something else be going on?
In cases like this, the answer depends on the whole picture. Blastocystis hominis is often found in people with no symptoms at all. When it comes together with low microbiome diversity, recent use of acid-suppressing medication and a symptom pattern that lines up in time with its appearance, the chance that it plays an active role rises considerably. The result is always read together with the person's full history, step by step.
From suspicion to the decision to test
Based on this reasoning, we started two things right away: a set of first changes to diet and routine, and, at the same time, a molecular stool test that would confirm or correct our hypothesis.
Which interventions did we start before the results came back?
Before we had the test results in hand, we made changes based on Andreas's history and diet.
His usual week
- Bread every day
- Rice six days
- Chicken every day
- Eggs every day
- Fish five days

The wider plate in his plan
- Quinoa
- Buckwheat
- Potato
- Legumes
- Gluten-free oats
- Long-fermentation bread

Less rice and chicken, more variety
Rice and chicken appeared almost every day in his diet, a pattern that keeps fiber diversity low and limits the different foods the gut microbiome needs to stay rich. Rice is also one of the main dietary sources of inorganic arsenic, so eating it daily added that factor to the decision. We limited both to three days a week, with other starches such as quinoa, buckwheat and potato, and legumes in place of chicken on most days. More on fiber variety is in fibermaxxing.
Less wheat, more alternative starches
Wheat appeared every day in his diet, mainly as bread. We limited wheat to three servings a week, with gluten-free oats, buckwheat and long-fermentation bread as alternatives, to reduce the load of fermentable carbohydrates while also increasing the overall variety of his diet.
Diaphragmatic breathing before every meal
We asked Andreas to do three minutes of diaphragmatic breathing before every meal. The goal was for him to start each meal with a calmer nervous system, which supports stomach movement and lowers pain sensitivity, two points that matched the burning and cramps he felt after eating.
What did the molecular stool test finally show?
The stool test gave a far more specific picture than the two normal endoscopy biopsies.
The value far exceeds the reference limit and was the central finding of the test: dense colonization of the gut by the protozoan.
Mildly raised, with none of the tested virulence factors present, so a low-aggressiveness strain, while two earlier biopsies had been negative.
Raised enzyme activity of the microbiome, consistent with low bacterial diversity and the reactivation of compounds inside the gut.
Enterococcus faecium, Staphylococcus, Streptococcus, Pseudomonas and Citrobacter freundii, a typical overgrowth in a gut with limited microbial diversity.
Within normal limits, with no active inflammation of the gut lining, despite the intensity of his symptoms.
A low value, consistent with his limited diet in the months before testing.
What these findings explain
This pattern also fits his history of acid-suppressing medication on and off, which has been linked with lower microbial diversity in the gut.4 Together, these findings point to a gut with raised enzyme activity and low microbial diversity, where Blastocystis hominis met less resistance than it would have met in a richer microbiome.
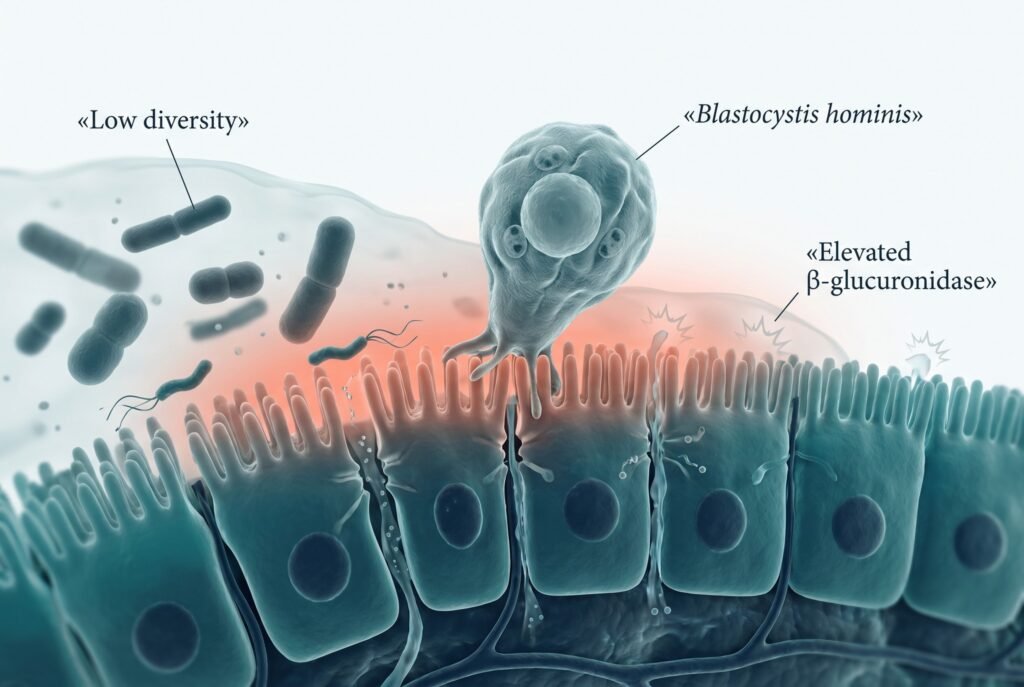
How Blastocystis hominis settles in the gut
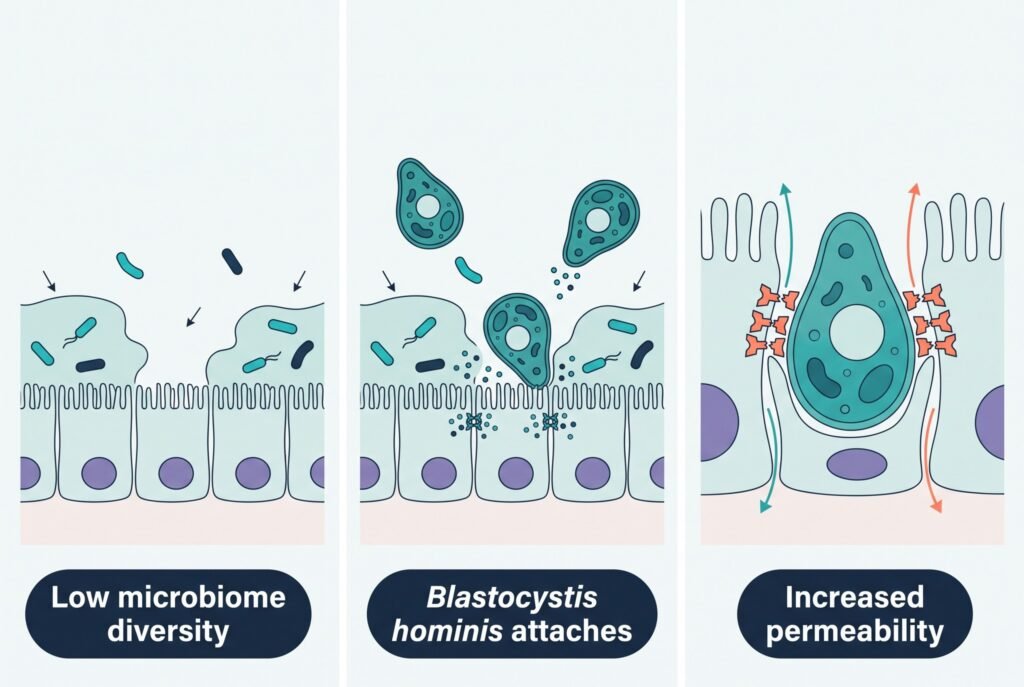
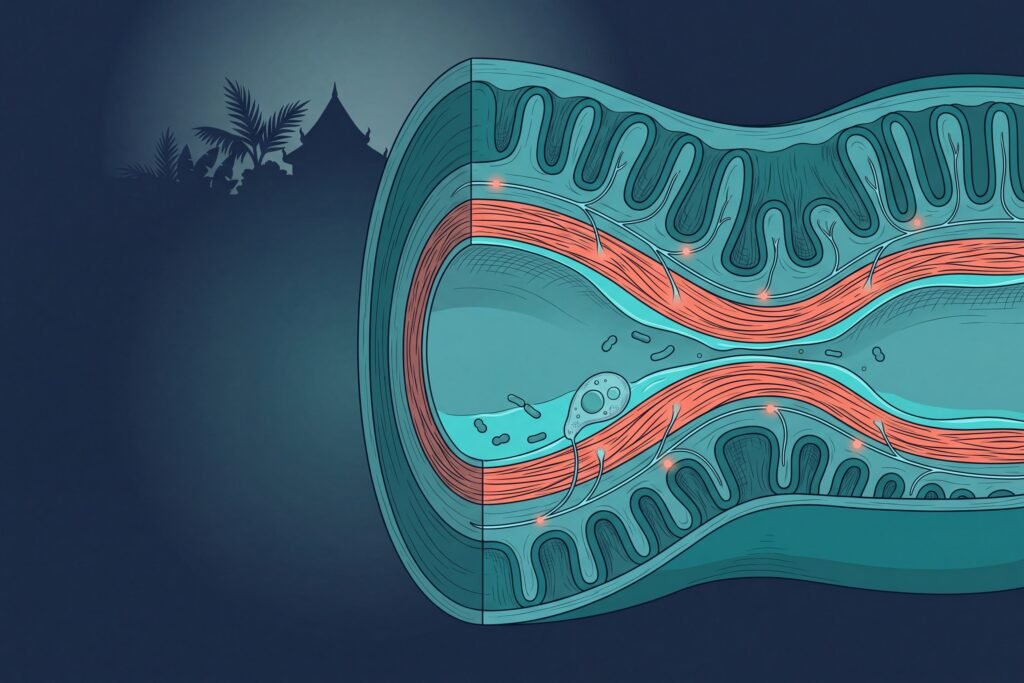
At the level of the gut lining, Blastocystis hominis attaches to gut cells and binds preferentially at the junctions between them, where it disrupts proteins such as ZO-1 and occludin and makes the barrier more permeable. The intensity of this disruption varies by strain, which helps explain why two people with the same organism can have very different symptoms.5
Why low fiber diversity favored colonization
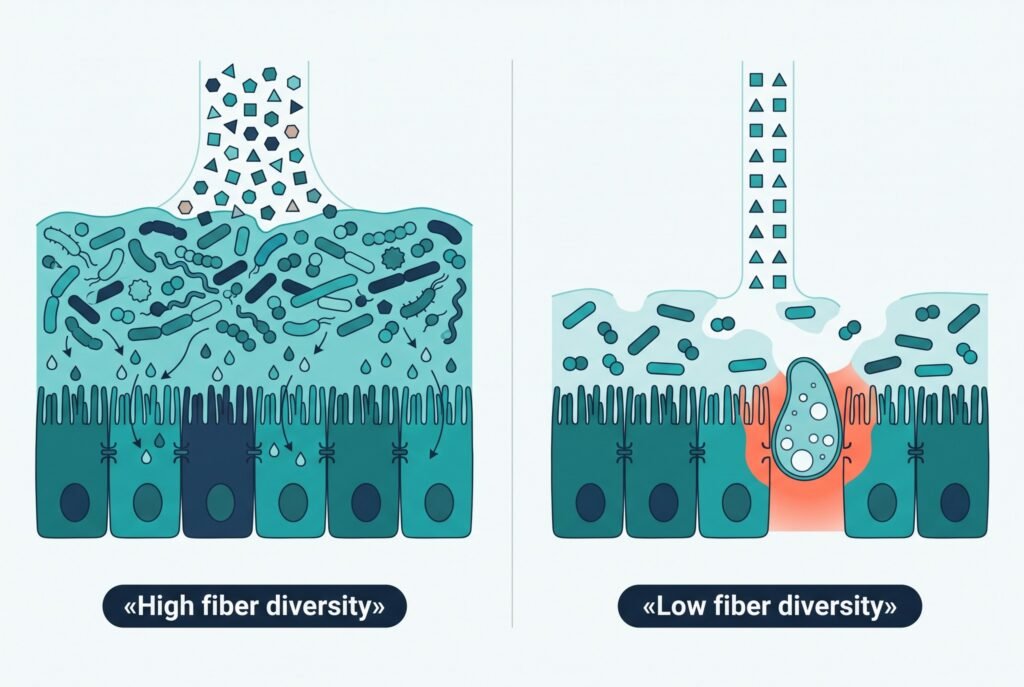
A microbiome fed by only a few fiber sources has fewer bacterial species and produces less butyrate and other short-chain fatty acids, which feed the cells of the gut lining and keep the protective mucus layer thick.2 With fewer species in the gut, a new colonizer such as Blastocystis hominis meets less resistance as it settles and persists. Blastocystis has also been linked with fewer protective gut bacteria.6
Blastocystis hominis is always harmless and never needs treatment.
In many people with a rich microbiome, it goes unnoticed. In a gut with low diversity and a history of acid-suppressing medication, as in Andreas's case, the same attachment and disruption of the junctions between cells can keep symptoms going for months.5
I was eating fairly healthily, without sugar or processed foods. Why was my microbiome still so vulnerable?
Each fiber source feeds different bacterial species in the gut. The narrower the range of foods, the fewer species find the fuel they need, and the microbiome ends up poorer and more open to new colonizers, even when the diet contains no sugar or processed food. This explains why Blastocystis hominis after travel can meet very different guts in two people, depending on how varied their diet was in the years before the trip.
The intervention plan
We built the plan around five targeted interventions, each tied to a specific finding.
| Intervention | Which finding, and why |
|---|---|
| Calcium D-glucarate, a natural compound that lowers beta-glucuronidase activity | For the raised fecal beta-glucuronidase, it reduces the reactivation of compounds inside the gut and takes pressure off the gut lining. |
| A blend of plant extracts with a broad antimicrobial profile | For the Blastocystis hominis colonization and the overgrowth of opportunistic bacteria, it targets the imbalanced microbial load without stripping the gut of beneficial species. |
| Butyric acid, a source of butyrate for the cells of the gut lining | To support the energy supply of gut cells and the integrity of the barrier, in a gut where low fiber diversity limited natural butyrate production. |
| A probiotic formula with Akkermansia muciniphila | To boost strains that support the gut lining, since Akkermansia muciniphila was at the low end of its reference range. |
| A formula that protects the stomach lining | For the reactive gastropathy and reflux-type esophagitis recorded on both endoscopies. |
The plan targeted more than Blastocystis hominis alone. It also targeted the raised beta-glucuronidase, the overgrowth of opportunistic bacteria and the gut lining, so that the gut could regain the diversity it was missing.
Every case is different, so Andreas's plan describes his care and is not a plan for anyone else. Treatment for Blastocystis is decided with the treating doctor.
What changed after treatment?
We waited before repeating the stool test. We preferred to give the plan time to work and to follow the course of his symptoms before deciding when a new check was worth it.
The improvement came gradually. It took at least four months of consistent treatment and diet changes for the difference to become clear, a reasonable timeframe for a goal as broad as restoring the diversity of a whole microbiome. In our experience, improvement in cases like this comes gradually, since the microbiome needs time to regain the diversity it has lost.
What this course shows
The most important finding went beyond the positive Blastocystis hominis result. A gut with chronically low fiber diversity needed far more time and a far more systematic plan to regain balance than one might expect from a simple antiparasitic course.
What does this case ultimately show?
Andreas's case shows something we often see in people with a consistent, seemingly healthy diet that has very little variety. The range of foods someone eats matters as much as their quality.
A pattern beyond one case
Low fiber diversity builds up gradually, years before any symptom appears. The trip and Blastocystis hominis were the trigger that revealed a weakness that already existed between diet, microbiome and the gut's ability to resist new colonizers.2 In Andreas's case, improvement came from targeted treatment together with a diet with much more variety, an approach that worked on both levels at once.
Frequently asked questions
Blastocystis hominis is a single-celled protozoan that lives in the gut and spreads mainly through contaminated water or food. It is often found in people with no symptoms at all, but in some cases it is linked with cramps, bloating and changes in bowel movements.
Possible symptoms include abdominal cramps, bloating, loose stools or changing bowel habits, fatigue and, in some people, skin symptoms. In returning travellers with persistent symptoms, fatigue, abdominal pain and loose stools were the most common complaints.1
Treatment depends on the symptoms and the whole picture, since many carriers need none. Options are decided by the treating doctor. In Andreas's case, a plant-based antimicrobial blend was combined with steps to rebuild the gut bacteria and a much more varied diet.
Travellers' diarrhea is one of the most common problems among visitors to regions such as Southeast Asia. In a study of foreign adults in Thailand, about a third developed it within the first month of their stay.3
Each fiber source feeds different bacterial species in the gut. A diet with few, repeating fiber sources leads to a poorer microbiome, with fewer species and less production of the compounds that protect the gut lining.2
References
6 studies
- Gefen-Halevi S, Biber A, Gazit Z, et al. Persistent abdominal symptoms in returning travellers: clinical and molecular findings. J Travel Med. 2022.
- Kable ME, Chin EL, Storms D, et al. Tree-based analysis of dietary diversity captures associations between fiber intake and gut microbiota composition in a healthy US adult cohort. J Nutr. 2022.
- Sharma C, Poovorawan K, Piyaphanee W, et al. Incidence of travelers' diarrhea among adult foreign travelers in Thailand: a prospective study. Am J Trop Med Hyg. 2020.
- Imhann F, Bonder MJ, Vich Vila A, et al. Proton pump inhibitors affect the gut microbiome. Gut. 2016.
- Wu Z, Mirza H, Tan KS. Intra-subtype variation in enteroadhesion accounts for differences in epithelial barrier disruption and is associated with metronidazole resistance in Blastocystis subtype-7. PLoS Negl Trop Dis. 2014.
- Nourrisson C, Scanzi J, Pereira B, et al. Blastocystis is associated with decrease of fecal microbiota protective bacteria: comparative analysis between patients with irritable bowel syndrome and control subjects. PLoS One. 2014.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 3). Blastocystis settled in the gut after a trip to Thailand. Gut Pathways. https://gutpathways.com/case-studies/blastocystis-hominis-after-travel/