The pill, dieting and quitting smoking slowed the bowel
Michelle's birth control constipation had several drivers: hormone receptor signalling, extreme dieting, smoking withdrawal and altered bile acid flow, all shaping her long history of slow bowel movements.
 Michelle's casecase study
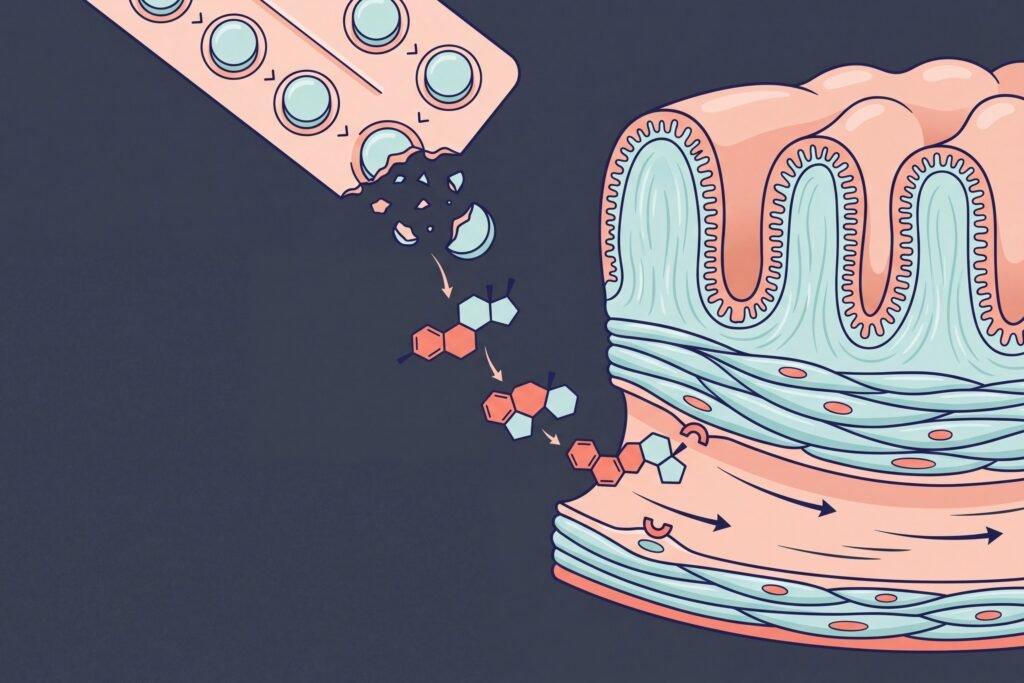
Yes, hormonal birth control can slow bowel movement because progestins relax intestinal smooth muscle and reduce propulsive contraction. For Michelle, this biological effect sits beside a severe calorie-restricted diet, low fluid intake, inactivity and the loss of nicotine's short-lived motor stimulus after smoking cessation.
The connection between oral contraceptives and constipation therefore forms one part of a wider mechanism, while her previous cholecystectomy adds a competing pro-motility bile-acid signal.
Who is Michelle and how did constipation become persistent?
A long history of IBS with constipation
Michelle is 64 and lives with constipation-predominant irritable bowel syndrome, and she came to the practice where I work as a scientific collaborator. While at university, she started oral contraception and recorded a 15 kg increase over two months. She then followed a strict hypocaloric diet and lost 34 kg in three months. The important sequence runs from hormonal exposure and alarm about weight to extreme restriction and repeated weight changes that reduced dietary consistency.
Low fluid, low movement and low stool-forming volume
At present, her pattern adds several forces in the same direction. She drinks about four glasses of water daily, has almost no planned movement and often relies on juices, pastries and other rapidly absorbed foods. In addition, a leg fracture caused prolonged immobility.
Whole foods provide physical bulk, retain water and distend the colon, while walking reinforces autonomic and mechanical signals for bowel movements. As a result, removing those inputs leaves stool in the colon longer, where more water is absorbed.
Smoking cessation and gallbladder removal pull in different directions
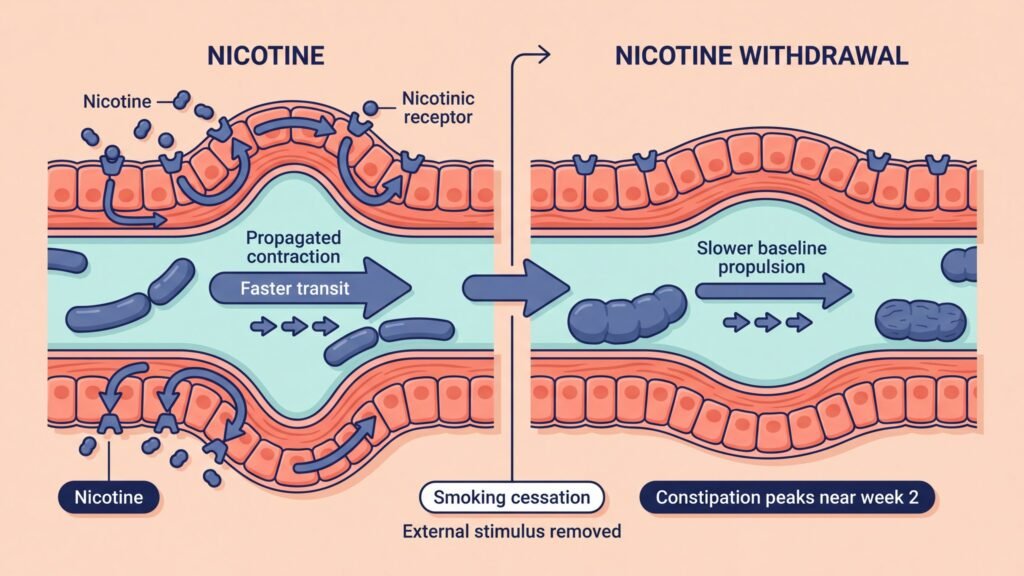
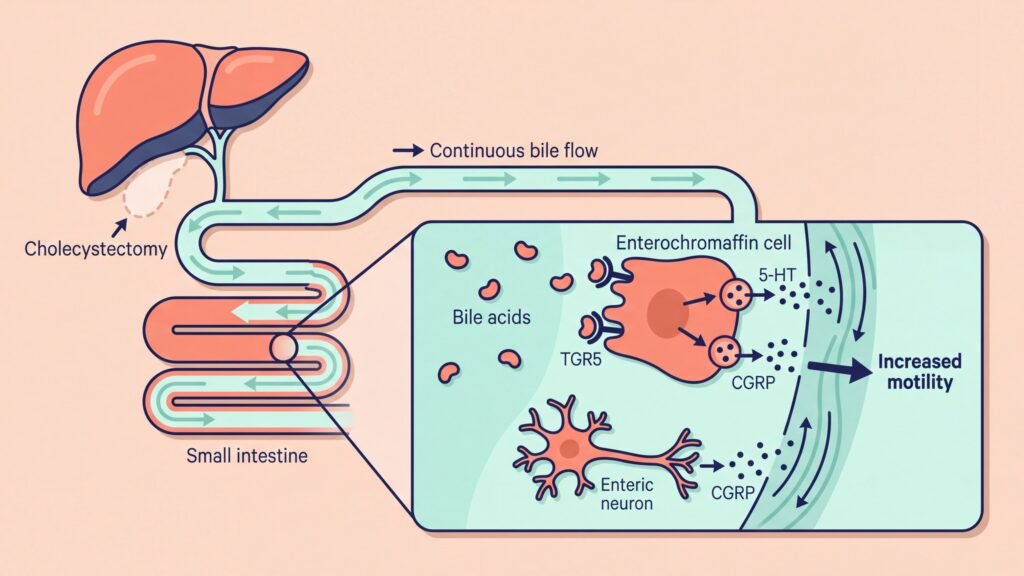
Michelle previously smoked about one pack daily for 25 years and later stopped. Nicotine can acutely shorten colonic transit, so withdrawal removes a repeated pharmacological stimulus and exposes the underlying slow bowel pattern. By contrast, cholecystectomy creates more continuous bile delivery into the intestine. Once they reach the bowel, bile acids activate pro-motility pathways, which means persistent constipation after gallbladder removal points to stronger slowing influences elsewhere in the system.
How are oral contraceptives and constipation connected through gut motility?
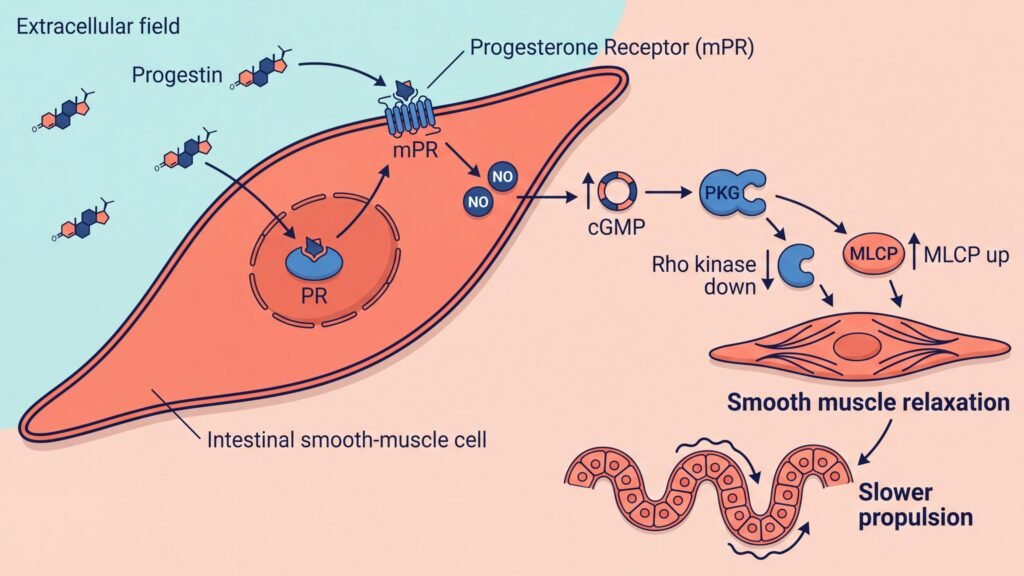
Progesterone and synthetic progestins act through nuclear progesterone receptors and membrane progesterone receptors in gastrointestinal tissue. Next, downstream signalling raises nitric oxide and cyclic GMP, activates protein kinase G, suppresses Rho kinase and activates myosin light-chain phosphatase. Consequently, actin and myosin generate less sustained force, intestinal smooth muscle relaxes and propulsive motility slows.1 Meanwhile, oestrogen signals through ERα, ERβ and GPER1, modifying enteric neurons, secretion, sensitivity and smooth-muscle behaviour.
- Progestin binds its receptors
Nuclear and membrane progesterone receptors in the gut wall receive the signal.
- Nitric oxide and cGMP rise
The signal raises nitric oxide, which generates cyclic GMP.
- PKG activity increases
Cyclic GMP activates protein kinase G.
- Rho kinase falls, MLCP rises
The contractile machinery shifts toward relaxation.
- Smooth muscle relaxes
Actin and myosin generate less sustained force.
- Propulsive transit slows
Stool stays longer in the colon, where more water is absorbed.
Each step follows the receptor pathway described in the review by Alqudah and colleagues.1
What human studies show
A prospective study of 78 healthy oral contraceptive users found significant variation in stool frequency, Bristol stool form and constipation across the pill cycle, with constipation peaking on day three of menstruation.4 In addition, a matched cohort study included 1,370,274 combined-pill users and the same number of controls. Gastroparesis occurred more often among users, with an odds ratio of 1.29, while early satiety reached an odds ratio of 2.31.2 Together, these findings place measurable human outcomes beside the established receptor pathway.
I started taking the pill and a few weeks later my bowel habits changed. Could the hormones be slowing my digestion and causing the constipation and bloating, or is the timing just a coincidence?
Birth control pills can alter digestion because progestins bind receptors in intestinal smooth muscle and shift the contractile machinery toward relaxation. Slower propulsion keeps stool in the colon for longer, increases water absorption and produces harder bowel movements, while changes in upper digestive motility can add fullness and bloating. Human studies record measurable changes in stool frequency, Bristol stool form, constipation and early satiety among oral contraceptive users.
How contraceptive methods compare
Systemic hormone exposure provides the clearest mechanistic scale for comparison. In levonorgestrel pharmacokinetic data, the hormonal IUD produced the lowest systemic exposure. The implant reached 1.7 to 2.1 times the exposure of the 20 μg/day IUD. Meanwhile, the progestin-only pill reached 1.7 times the average and 4.5 times the peak exposure, while the combined pill reached 8.6 times the average and 18 times the peak exposure.3
Systemic levonorgestrel exposure by method (× the hormonal IUD)
Hofmann 2020, levonorgestrel-specific comparison against the 20 μg/day hormonal IUD.3
- Copper IUD No systemic estrogen or progestin signalling and no direct hormonal mechanism for slowing intestinal smooth muscle.
- Barrier methods No hormonal exposure and no direct effect on intestinal hormone receptors.
- Hormonal IUD The lowest systemic levonorgestrel exposure in the comparison and therefore the lowest direct whole-gut hormonal pressure among the hormonal methods assessed.
- Implant Systemic progestin exposure 1.7 to 2.1 times the hormonal IUD.
- Progestin-only pill Systemic progestin action without estrogen, 1.7 times the average and 4.5 times the peak exposure of the hormonal IUD. Direct smooth-muscle signalling remains relevant.
- Combined oral pill Systemic estrogen and progestin exposure, 8.6 times the average and 18 times the peak. Strong receptor-level plausibility for slower propulsion.
Not on this scale
- Patch or vaginal ring They bypass intestinal absorption and retain systemic hormonal signalling, so the receptor effect remains active.
- DMPA injection Long-acting systemic progestin exposure. Michelle's recorded history identifies an oral method instead.
Methods are ordered by average levonorgestrel exposure in Hofmann 2020. The spacing shows the order, not exact distances.3
Every hormonal method seems to use a different dose and route. Is there a birth control option that is less likely to affect digestion, especially when constipation or IBS is already present?
Barrier methods and the copper IUD are hormone-free, giving them the least direct influence on intestinal hormone receptors. Among levonorgestrel methods, the hormonal IUD produces much lower systemic exposure than oral pills and implants. Patches and vaginal rings bypass intestinal absorption, while their circulating hormones continue to reach estrogen and progesterone receptors in the digestive tract. The choice of method always belongs to the conversation with your gynaecologist.
Why smoking creates a false sense of better motility
Mechanistically, nicotine stimulates autonomic nicotinic receptors and can trigger high-amplitude propagated contractions. In a controlled transdermal study, total colonic transit fell from 42.6 hours at baseline to 32.2 hours with 17.5 mg nicotine and 28.2 hours with 35 mg. Likewise, rectosigmoid transit fell from 18.6 to 9.9 and 7.6 hours.5
Total colonic transit with transdermal nicotine (hours)
Rausch 1998, healthy non-smoking volunteers.5
Smoking therefore supplies a short-lived drug stimulus while leaving the underlying cause untouched. When smoking stops, that stimulus disappears. Symptoms peak around the second week because enteric and autonomic signalling resumes without nicotine.6
Smoking helps the bowel work normally.
Nicotine temporarily stimulates motor pathways and can shorten transit. The effect masks baseline slow motility, while tobacco exposure damages cardiovascular, immune and epithelial function.
How cholecystectomy shifts transit toward acceleration
After cholecystectomy, bile enters the intestine continuously between meals alongside post-meal flow. Bile acids then bind TGR5 on enterochromaffin cells and enteric neurons, increasing 5-HT and CGRP signalling and promoting peristalsis in mice.7 Accordingly, a systematic review found post-cholecystectomy diarrhea in 462 of 3,476 patients, or 13.3%.8
The physiology also explains why digestive symptoms after gallbladder removal follow a different pattern from slow-transit constipation. Michelle's persistent symptoms reflect the stronger combined load from hormonal signalling, restriction, dehydration and inactivity.
Infographic
Progestins relax the gut
Progestins relax intestinal smooth muscle and reduce propulsive contraction, which slows transit.
Less bulk, water and movement
Little food volume, low fluid and almost no movement leave stool in the colon longer, where more water is absorbed.

The nicotine stimulus is gone
Nicotine can shorten colonic transit, so stopping smoking removes a repeated stimulus and exposes the slow bowel pattern.

A competing signal
Gallbladder removal adds a pro-motility bile-acid signal, so ongoing constipation points to stronger slowing influences elsewhere.
Sources: Alqudah et al. 2022, Rausch et al. 1998, Hajek et al. 2003, Alemi et al. 2013.
gutpathways.com
 Save this infographicImage 4:5, with sources, from gutpathways.com
What can the proposed tests clarify about digestive symptoms?
The proposed tests separate intestinal inflammation, metabolic pressure, nutrient status and systemic contributors. All values remain pending. First, fecal calprotectin measures neutrophil activity in the intestinal mucosa and distinguishes inflammatory bowel disease from a functional IBS pattern. Meanwhile, a complete blood count and urinalysis provide a broader screen for anaemia, infection and hydration-related findings.
| Test | What it clarifies |
|---|---|
| Fecal calprotectin | Separates inflammatory mucosal activity from an IBS-C symptom pattern. |
| HbA1c and glucose–insulin curve | Maps glycaemic exposure and insulin dynamics against obesity and repeated weight cycling. |
| Iron, ferritin, folate and 25-OH vitamin D | Assesses nutrient reserves affected by long periods of restrictive dieting. |
| Calcium, magnesium and zinc | Assesses minerals involved in neuromuscular function and tissue repair. |
| IgA, IgG, total IgE, C3 and C4 | Adds immune context to persistent gastrointestinal symptoms. |
| Homocysteine and prolactin | Adds metabolic and endocrine information to the wider biological picture. |
| Lp(a), fibrinogen and D-dimers | Profiles cardiovascular and coagulation pressure alongside obesity and inactivity. |
Which changes target constipation and bowel function?
Regular food volume, adequate fluid and daily movement restore the physical inputs that initiate bowel movements. The proposed plan starts with a protein-containing breakfast on at least five days each week and removes juice, jelly and creams. Therefore, energy arrives with chewing and intact food structure, reducing rapid liquid sugar delivery. In addition, one whole fruit retains water, fibre and bulk lost during juicing.
Replace extreme restriction with consistent structure
A very-low-calorie diet sharply reduces the material entering the colon. In a controlled study, bowel frequency fell from 1.9 movements a day on the habitual diet to 0.7 on a 388 kcal diet. Adding 30 g of fibre raised the rate to 1.0, while weight loss remained similar.9 The same stool-bulking mechanism explains how soluble fibre such as psyllium affects IBS. Eliminating repeated crash dieting is central to rebuilding predictable motility for Michelle. Kate's case shows the same pattern in constipation after extreme dieting.
Bowel movements per day on a very-low-calorie diet
Quaade 1990. Weight loss was similar with and without the added fibre.9
Restore water and mechanical stimulation
First, more than two litres of fluid daily supports stool hydration, while thorough chewing slows intake and strengthens cephalic and gastric signalling. In parallel, more than 8,000 steps on four days each week and planned movement on the remaining days increase abdominal wall activity and autonomic input. In addition, an earlier dinner reduces large late-night digestive loads. After cholecystectomy, regular meals with moderate fat portions distribute bile-acid exposure more evenly across the day.
How the drivers of Michelle's constipation fit together
- Food volume and water Whole foods, fibre and fluid create bulk and retain water in stool.
- Daily movement Walking and structured activity support propulsive colonic activity.
- Hormonal signalling Progestin receptor pathways reduce contractile force and slow propulsion.
- Nicotine withdrawal Stopping smoking removes nicotine-driven motor stimulation and reveals baseline slow transit.
- Persistent constipation Longer transit increases water absorption and produces harder, less frequent stool.
The outer rings are the physiological foundation and the centre is the accumulated symptom pattern. Tap a ring or a line to link them.
Every case is different, so Michelle's plan describes her care and is not a plan for anyone else. Any change of contraceptive or medicine is always decided by her doctors.
Why can these changes improve bowel movements?
Constipation persists when several braking forces converge. For Michelle, the combined oral pill is the most plausible historical contraceptive exposure, and progestin signalling provides a direct smooth-muscle mechanism. Extreme dieting then removed food volume and fibre, while low water intake, immobility and smoking cessation added further pressure. Cholecystectomy supplied a competing bile-acid signal toward faster transit, while the remaining factors dominated the final pattern.
What the combined pattern explains
A stable eating pattern corrects the problem that crash diets intensify. First, whole fruit, structured meals and adequate water increase stool mass and hydration. Meanwhile, daily walking supplies repeated mechanical and autonomic stimulation. Consequently, these changes act on different parts of the same system, so they are stronger together than an isolated supplement or another short restrictive diet. Finally, the planned tests determine whether inflammation, metabolic dysfunction or nutrient depletion adds another measurable layer.
Frequently asked questions
It can contribute. Progestins act on receptors in intestinal smooth muscle and shift it toward relaxation, so propulsion slows.1 In 78 pill users, constipation changed across the pill cycle and peaked on day three of menstruation.4 Diet, fluid, movement and other medicines usually add to the effect.
Regular meals with whole foods, enough fluid and daily walking restore the inputs that start bowel movements. Soluble fibre added gradually raises stool frequency even on very low-calorie diets.9 If constipation stays, the choice of contraceptive method is worth discussing with your gynaecologist, because methods differ in systemic hormone exposure.3
Progestins activate nuclear and membrane progesterone receptors in gastrointestinal tissue. The pathway increases nitric oxide, cyclic GMP and protein kinase G, reduces Rho kinase activity and activates myosin light-chain phosphatase.1 Intestinal smooth muscle then generates less contractile force, so propulsion slows and stool remains longer in the colon.
Yes. Nicotine can acutely stimulate colonic motor activity and shorten transit.5 When smoking stops, that repeated drug stimulus disappears, exposing the person's baseline motility. Withdrawal-related constipation commonly becomes most noticeable during the second week and then settles as autonomic and enteric signalling adapts.6
Gallbladder removal usually shifts physiology in the opposite direction. Continuous bile delivery activates the TGR5 bile-acid receptor on enterochromaffin cells and enteric neurons, increasing pro-motility signalling.7 Post-cholecystectomy diarrhea is consequently more characteristic than constipation.8
In comparative levonorgestrel pharmacokinetic data, hormonal intrauterine systems produce the lowest systemic exposure.3 Copper IUDs and barrier methods are hormone-free, giving them minimal direct influence on estrogen or progesterone receptors in the bowel.
Extreme diets sharply reduce total food volume, fibre and fermentable substrate. Less material reaches the colon, distension falls and the mechanical signal for propulsion weakens. If fluid intake also falls, the colon removes more water from a smaller stool mass and produces harder, less frequent bowel movements.9
References
9 studies
- Alqudah M, Al-Shboul O, Al Dwairi A, et al. Progesterone inhibitory role on gastrointestinal motility. Physiol Res. 2022.
- Khalil J, Hill H, Einstadter D, Fass R. Combined oral contraceptives are associated with increased risk of developing gastroparesis in pre-menopausal women. Dig Liver Dis. 2025.
- Hofmann BM, Apter D, Bitzer J, et al. Comparative pharmacokinetic analysis of levonorgestrel-releasing intrauterine systems and levonorgestrel-containing contraceptives with oral or subdermal administration route. Eur J Contracept Reprod Health Care. 2020.
- Judkins TC, Dennis-Wall JC, Sims SM, et al. Stool frequency and form and gastrointestinal symptoms differ by day of the menstrual cycle in healthy adult women taking oral contraceptives: a prospective observational study. BMC Womens Health. 2020.
- Rausch T, Beglinger C, Alam N, et al. Effect of transdermal application of nicotine on colonic transit in healthy nonsmoking volunteers. Neurogastroenterol Motil. 1998.
- Hajek P, Gillison F, McRobbie H. Stopping smoking can cause constipation. Addiction. 2003.
- Alemi F, Poole DP, Chiu J, et al. The receptor TGR5 mediates the prokinetic actions of intestinal bile acids and is required for normal defecation in mice. Gastroenterology. 2013.
- Farrugia A, Attard JA, Khan S, et al. Postcholecystectomy diarrhoea rate and predictive factors: a systematic review of the literature. BMJ Open. 2022.
- Quaade F, Vrist E, Astrup A. Dietary fiber added to a very-low-calorie diet reduces hunger and alleviates constipation. Ugeskr Laeger. 1990.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 20). The pill, dieting and quitting smoking slowed the bowel. Gut Pathways. https://gutpathways.com/case-studies/oral-contraceptives-constipation/