Fusobacterium endometriosis: what the evidence shows now
The Fusobacterium endometriosis link offers a plausible way for microbial exposure, immune signaling and tissue behavior to meet in a susceptible pelvis. The evidence now includes a detailed mechanism, an oral microbiome angle and a human study with a conflicting result, so the organism is best seen as one candidate piece of a complex disease.
What is the connection between Fusobacterium and endometriosis?
The connection is biologically plausible but clinically unsettled. Muraoka and colleagues reported in Science Translational Medicine that the bacterium was present in the womb lining of 27 of 42 women with ovarian endometriosis and in 3 of 42 controls. The controls had surgery for other conditions, such as fibroids and cervical dysplasia. The team then tested how exposure changed immune and stromal cell behavior.1
The 2023 study combined human tissue, cell experiments and a mouse model. Inoculation with the bacterium increased the number and weight of endometriosis lesions in mice, while antibiotic treatment reduced both.1
"Our data support a mechanism for the pathogenesis of endometriosis via Fusobacterium infection." Muraoka and colleagues, 2023
The 2025 replication changed the interpretation
Graciano-España and colleagues tested the womb lining of 55 women with endometriosis and 37 women without it. Quantitative PCR found no significant difference at genus level (P = .258) or for F. nucleatum (P = .738), and subgroups by disease severity were also similar.2
Differences in age, sampling, laboratory extraction, type of endometriosis and contamination control in low-biomass samples may help explain why the two studies diverged. For now, the result places the microbe among candidate modifiers with limited value as a diagnostic marker.
"Limited diagnostic or prognostic value in endometriosis." Graciano-España and colleagues, 2025
Why does retrograde menstruation lead to endometriosis in some women?
During retrograde menstruation, part of the menstrual fluid flows back through the fallopian tubes into the pelvis instead of leaving through the cervix and vagina. That fluid can carry living cells from the womb lining to the ovaries, the pelvic lining and nearby organs. The flow itself is very common: blood was found in the pelvic fluid of 90% of women with open tubes around their period.6 Persistent disease, however, affects a much smaller share of women.
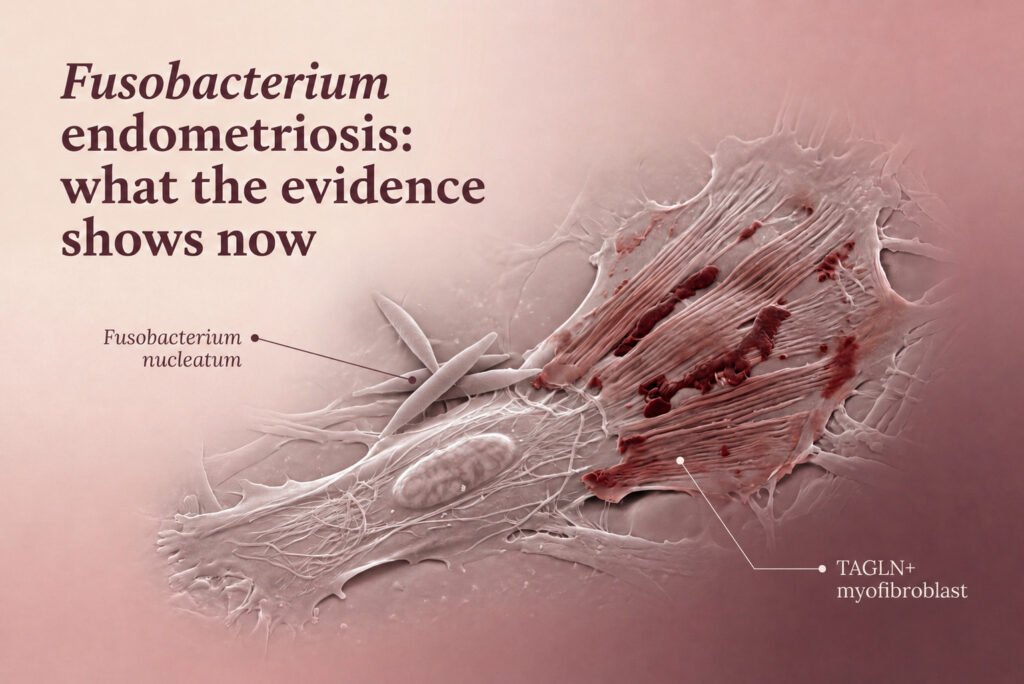
The gap between common cell transport and less common lesions is where immune surveillance, estrogen signaling, genetics, fibrosis and local microbes become relevant. A displaced cell still has to attach, get a blood supply, avoid immune clearance and respond to the hormonal cycle. The 2023 mechanism offers one possible contribution to that sequence. A growth factor released by immune cells raised the protein transgelin, and TAGLN-positive myofibroblasts proliferated, adhered and migrated more readily.1
This model gives backward menstrual flow a tissue context. The same menstrual material may meet very different immune and microbial conditions in two women. One pelvis clears the displaced cells, while another holds inflammatory, hormonal and fibrotic signals that improve their chance of staying.
How could the organism reach the womb lining and start inflammation?
Two routes are under investigation. An ascending route would start in the lower reproductive tract and move through the cervix toward the uterus. A bloodstream route would carry the organism from the mouth after gum tissue is disrupted, since F. nucleatum is known to spread from the mouth to distant sites.7 The 2023 team also reported a higher signal in vaginal swabs from affected women, which supports further study of the ascending route.1 Direction and timing remain unresolved.
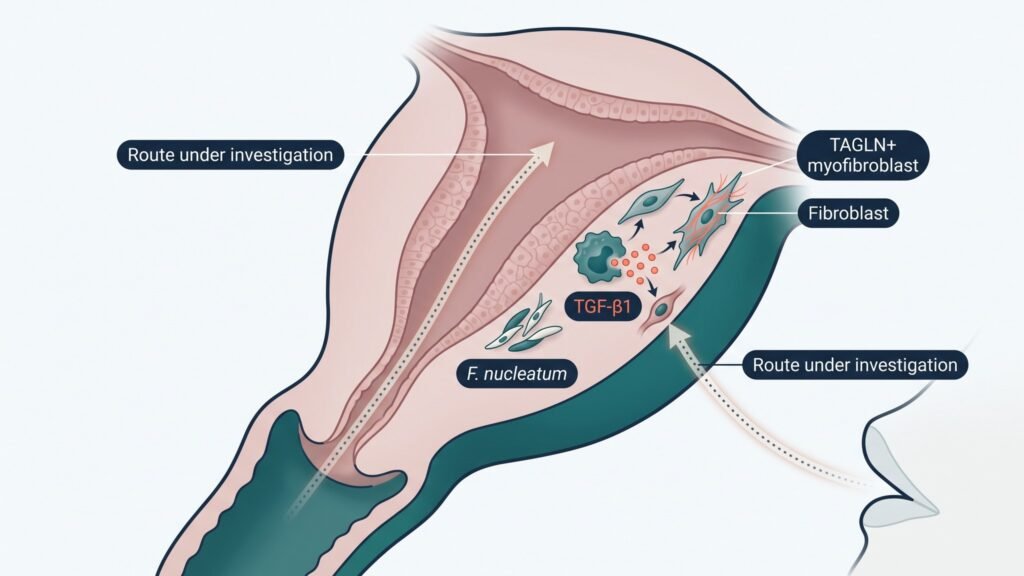
From microbial exposure to altered fibroblast behavior
Inside the tissue, the proposed sequence begins with immune recognition. F. nucleatum stimulated M2-type macrophages to release TGF-β1, even when heat-killed bacteria were used in the laboratory. This signal raised transgelin and shifted quiet fibroblasts toward contractile myofibroblasts that adhered and migrated more, properties relevant to displaced tissue settling after menstruation.1
This pathway describes a local tissue mechanism. Oral abundance, stool abundance and a tissue finding are different biological measurements, so a positive stool panel describes intestinal bacteria and leaves the pelvis unanswered.
Which endometriosis symptoms deserve a more specific investigation?
The most informative pattern is pain or organ dysfunction that follows the menstrual cycle. Severe period pain may start before bleeding and last several days. Deep pain during sex is often felt behind the vagina or low in the pelvis. Painful bowel movements can come with rectal pressure, constipation or cyclical rectal bleeding, while bladder involvement can bring pain, urgency or cyclical blood in the urine.
Pain between periods, chronic low back pain, heavy bleeding, fatigue, abdominal swelling and infertility also occur. In addition, bowel symptoms can resemble IBS, especially when bloating, diarrhea or constipation change across the cycle. Timing, exact location and the link to sex, bowel movements or urination often tell more than a general pelvic pain score. In a Dutch referral cohort, almost every woman with a cycle reported period pain.8
Symptoms in a Dutch endometriosis cohort
van Poll 2020, women seen at seven referral centers. Denominators differ by symptom because answers varied.
Which tests can find endometriosis and what can each report show?
A specialist transvaginal ultrasound is usually the most important first imaging test. It can show ovarian endometriomas, reduced organ mobility, a closed-off pouch of Douglas and many forms of deep disease. MRI adds value when the disease needs detailed mapping before surgery, especially around the bowel, bladder, ureters or pelvic sidewall. In both cases, image quality depends heavily on the operator and the protocol.3
| Test and priority | What the report may show |
|---|---|
| Specialist transvaginal ultrasound, the most important first imaging test | An ovarian cyst with uniform ground-glass echoes, ovaries stuck together, a negative sliding sign, fixed pelvic organs, deep nodules or signs of adenomyosis. A routine pelvic scan may skip this systematic mapping. |
| Pelvic MRI with an endometriosis protocol, most useful for complex or deep disease | Endometriomas with typical signal changes, fibrotic plaques, tethering, adhesions and involvement of the rectosigmoid, bladder, ureter, vagina or uterosacral ligaments. |
| Laparoscopy with targeted histology, most definitive when confirmation or surgery is needed | Superficial implants, ovarian disease, adhesions, fibrosis and deep nodules. Histology may describe endometrium-like glands and stroma, iron-laden macrophages or fibrosis. |
| Pelvic examination, supportive | Tenderness behind the cervix, nodules on the uterosacral ligaments, a fixed tilted uterus, an ovarian mass or reduced organ mobility. A normal examination is common in superficial disease. |
| CA-125 or other blood markers, low priority | CA-125 may rise in advanced disease and may stay normal at any stage. Guidelines do not use blood markers to diagnose or rule out endometriosis.3 |
| Biopsy or local sampling for the organism, research use | PCR, sequencing or tissue staining may find microbial DNA in research samples. Clinical cut-offs for diagnosis and treatment are still being developed. |
How accurate are examination and imaging for deep disease?
A meta-analysis of 30 studies with 4,565 participants compared physical examination, transvaginal ultrasound, transrectal ultrasound and MRI for deep infiltrating endometriosis.4 These numbers apply only to deep disease, because superficial implants can stay invisible on scans.
Accuracy for deep infiltrating endometriosis (%)
Zhang 2020, meta-analysis of 30 studies, 4,565 participants.
I have surgically confirmed endometriosis and a stool test showing high Fusobacterium nucleatum. Does that mean the bacterium is also in my uterus, and which test would actually check that?
A stool result describes the intestinal ecosystem and does not tell where else the same organism lives. Research protocols use cervical or vaginal swabs, a biopsy of the lining, PCR and tissue imaging, and clinical cut-offs are still being developed. A practical review starts with your operative report, histology, specialist imaging, oral health, bowel pattern and past antibiotic courses.
What makes F. nucleatum capable of reaching and attaching to distant tissues?
F. nucleatum is a Gram-negative, strictly anaerobic bacterium with a slender spindle shape and tapered ends. It lives mainly in the mouth, where its surface adhesins bind both human cells and other bacteria. This lets it link different species together inside dental plaque and contributes to gum disease. It can also enter the blood during active gum inflammation or dental work.9, 7
Outside the mouth, higher abundance or tissue presence has been associated with colorectal cancer, inflammatory bowel disease, appendicitis, adverse pregnancy outcomes and several opportunistic infections.7 These associations vary by subspecies and tissue. The step-by-step rebuilding of a disturbed gut community is covered in how to treat gut dysbiosis.
Candida may provide an additional docking partner
A 2026 Cancer Cell study found that the fungal adhesin Flo9 on Candida albicans binds the bacterial adhesin RadD of F. nucleatum. That interaction helped F. nucleatum settle on the colon lining and sped up colorectal tumor growth in experimental models.10 The study gives direct molecular evidence for fungus-bacterium docking in the colon, while its relevance to the womb lining remains a research question.
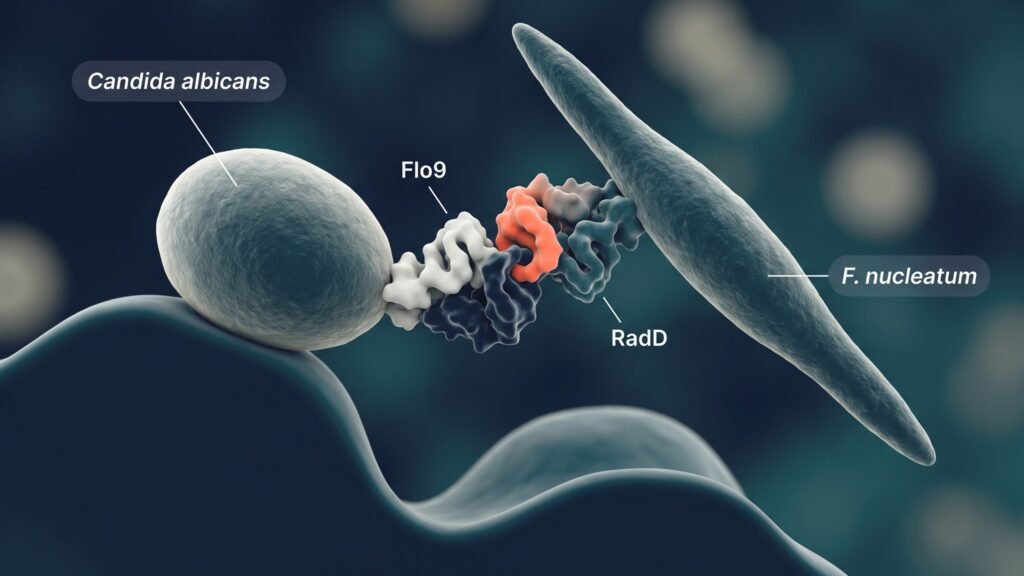
Li and colleagues identified the binding of Flo9 to RadD as the way C. albicans helps F. nucleatum localize to the colon lining. In their models, L-arginine disrupted this interaction and reduced the combined tumor-promoting effect.10
What does Fusobacterium endometriosis treatment mean in 2026?
At present, it is a research direction without a validated clinical protocol. In the original experiment, metronidazole and chloramphenicol reduced the bacterial signal, immune cell infiltration, growth-factor levels and the number and weight of established lesions in mice. Treatment was tested by vaginal and oral routes at different stages of the model.1 These findings show that the process can be reversed in a controlled mouse system.
The human antibiotic trial produced a different result
The METROFERT trial randomized 88 women after fertility-sparing endometriosis surgery to 14 days of oral metronidazole or placebo, and 72 completed the primary endpoint. At six weeks, persistent pain was reported by 84% with metronidazole and 88% with placebo (P = .74). Quality of life, sexual function and pain scores were also similar.5
Eligibility depended on the surgery, not on a positive test for the bacterium, so the trial did not measure tissue positivity or eradication. In other words, it tested an antibiotic in a general group rather than in a defined Fusobacterium-positive subgroup.
What testing and clinical trials still need to establish
The ENDS study, registered in 2024 as NCT06368596 with a planned enrollment of 845 women, is examining detection in cervical, vaginal and tissue samples. It is a diagnostic study without a drug.11 Its design reflects the main open issue, because a reproducible, tissue-defined subgroup has to exist before a targeted strategy can be tested.
A broad-spectrum antibiotic changes many bacteria besides the intended target. Clinicians therefore need a validated test, a defined positive subgroup and human outcome data before prescribing antibiotics for this mechanism. Oral hygiene and treatment of active gum disease make sense for general health and may lower the oral reservoir, while laboratory findings for plant antimicrobials remain preclinical for pelvic disease.
What changes when microbial ecology is included in a root-cause plan?
The microbial question becomes one layer of the clinical picture. The first layer identifies where the disease is and what type it is, through symptoms, specialist imaging and earlier operative findings. The second looks at what keeps it going. Treatment then follows the layer with the strongest evidence and the clearest link to the person's symptoms.
Oral inflammation
Active gum disease is the main reservoir of F. nucleatum and a possible route to the bloodstream, so dental care belongs in the plan.7
Gut dysbiosis
An unstable gut community can keep inflammation and bowel symptoms going, which matters when symptoms resemble IBS.

Immune activation
Immune signaling decides whether displaced cells are cleared or allowed to settle, as the TGF-β1 pathway shows.1
Hormones, fibrosis and the pelvic floor
Estrogen exposure, scarring, pelvic-floor tension and bowel motility all shape how long pain persists after the first trigger.
In the practice where I work as a scientific collaborator, this layered order also keeps a positive stool result from pushing aside standard gynecological care. Someone with cyclical painful bowel movements and a normal routine ultrasound may need specialist imaging before another antimicrobial course. On the other hand, someone with confirmed disease, active gum disease and digestive symptoms may benefit from a coordinated gynecological, dental and gastrointestinal assessment.
The hypothesis is most useful when it improves the questions being asked:
My pelvic pain improved for a while when I took metronidazole for another infection. Could that point to a Fusobacterium pattern, and is a targeted antibiotic worth discussing?
A temporary response is worth recording, including the dose, the duration, the cycle phase and which symptoms changed. Metronidazole acts on many anaerobes and may also change gut or vaginal bacteria, so the response is not specific to one organism. A validated test-and-treat pathway does not exist yet, so a clinician can use the response as one data point next to imaging, operative findings, oral health and the pattern of recurrence.
Frequently asked questions
Several plant compounds inhibit the organism in laboratory experiments, but human evidence for clearing it from pelvic tissue is still missing. Gum care and consistent oral hygiene address its main reservoir, and treatment decisions need local findings rather than a stool result alone.
A stool test measures intestinal abundance. Research detection in the uterus needs a locally collected sample such as a biopsy, followed by PCR, sequencing or tissue imaging, and validated clinical cut-offs are still being developed.
References
11 studies
- Muraoka A, Suzuki M, Hamaguchi T, et al. Fusobacterium infection facilitates the development of endometriosis through the phenotypic transition of endometrial fibroblasts. Sci Transl Med. 2023.
- Graciano-España MC, Barnhart K, Gonzalez-Monfort M, et al. Fusobacterium nucleatum is not significantly present in eutopic endometrium from patients with minimal-mild and moderate-severe endometriosis. Fertil Steril. 2025.
- Becker CM, Bokor A, Heikinheimo O, et al. ESHRE guideline: endometriosis. Hum Reprod Open. 2022.
- Zhang X, He T, Shen W. Comparison of physical examination, ultrasound techniques and magnetic resonance imaging for the diagnosis of deep infiltrating endometriosis: a systematic review and meta-analysis of diagnostic accuracy studies. Exp Ther Med. 2020.
- Quevedo A, Parikh S, Reinstine J, et al. The impact of metronidazole on pain persistence after fertility-sparing endometriosis surgery: METROFERT randomized study. Am J Obstet Gynecol. 2025.
- Halme J, Hammond MG, Hulka JF, Raj SG, Talbert LM. Retrograde menstruation in healthy women and in patients with endometriosis. Obstet Gynecol. 1984.
- Han YW. Fusobacterium nucleatum: a commensal-turned pathogen. Curr Opin Microbiol. 2015.
- van Poll M, van Barneveld E, Aerts L, et al. Endometriosis and sexual quality of life. Sex Med. 2020.
- Brennan CA, Garrett WS. Fusobacterium nucleatum, symbiont, opportunist and oncobacterium. Nat Rev Microbiol. 2019.
- Li J, Zhang C, Huang X, et al. Candida albicans synergizes with Fusobacterium nucleatum in colorectal cancer progression via the Flo9-RadD interaction. Cancer Cell. 2026.
- ENDS (ENDometriosis and FuSobacterium). ClinicalTrials.gov NCT06368596. IRCCS Sacro Cuore Don Calabria, 2024.
Found this useful? Share it with someone who needs it.
Cite this article
Prevedoros, T. (2026, September 1). Fusobacterium endometriosis: what the evidence shows now. Gut Pathways. https://gutpathways.com/articles/fusobacterium-endometriosis/